Cross Linking Eye Surgery: Steps, Recovery, and Candidacy
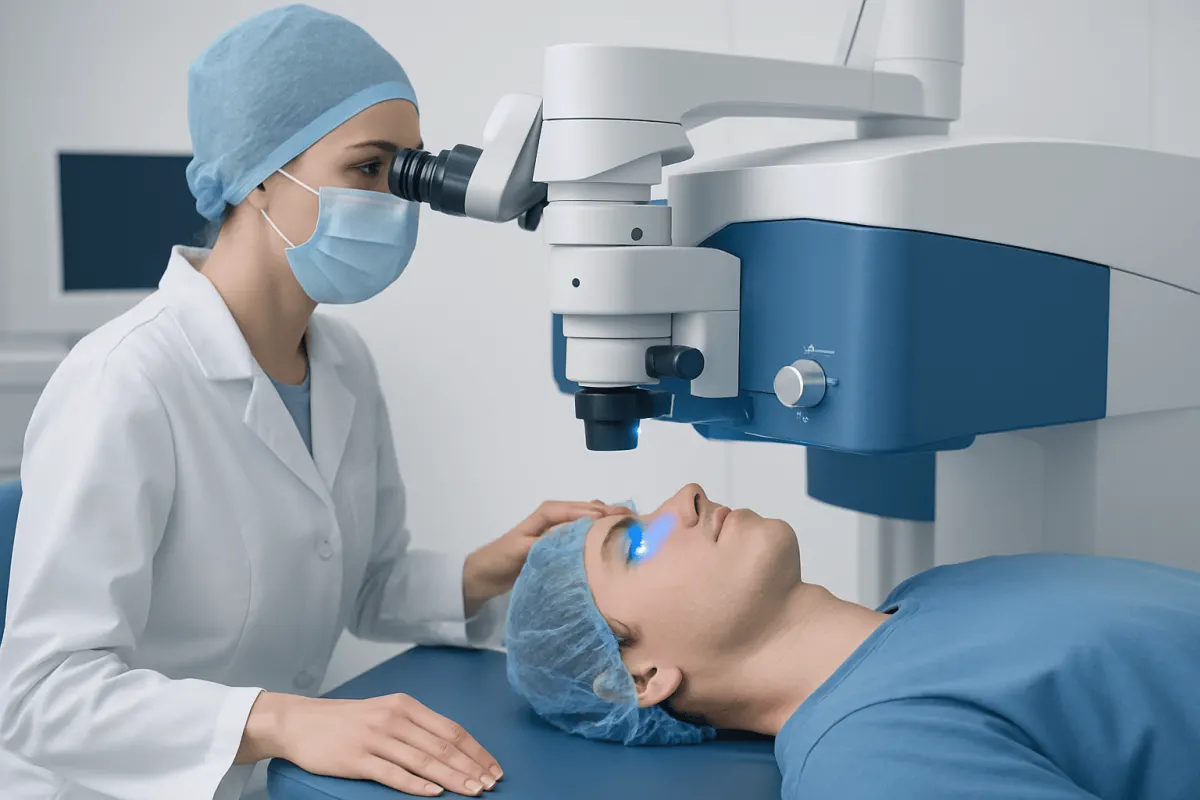
Cross linking eye surgery is an outpatient treatment that uses riboflavin eye drops and ultraviolet light to strengthen corneal tissue, most often to slow progression of keratoconus or corneal ectasia. It is designed to stabilize the cornea rather than reverse existing irregularity, so timely assessment and follow-up are important.
What is cross linking eye surgery?
Cross linking eye surgery, also called corneal collagen cross-linking, is a procedure that strengthens the clear front surface of the eye, known as the cornea. It combines riboflavin (vitamin B2) eye drops with carefully controlled ultraviolet-A light. This triggers additional links between collagen fibers in the cornea, making the tissue more resistant to further weakening.
The procedure is most often used for progressive keratoconus, a condition in which the cornea gradually thins and becomes cone-shaped, causing distorted or blurred vision. It may also be considered for progressive corneal ectasia, which can occur after certain corneal refractive procedures. Cross-linking is intended to stabilize the condition; it does not usually remove the need for glasses or contact lenses, and it may not restore vision already lost from corneal irregularity.
For people with worsening keratoconus, keratoconus treatment may include cross-linking alongside measures to improve vision, such as specialty contact lenses or other procedures when appropriate. An ophthalmologist can explain whether cross-linking is suitable based on examination findings and corneal measurements.
How cross-linking works and who may be a candidate
The cornea needs to retain a regular shape to focus light accurately on the retina. In keratoconus and ectasia, changes in the cornea’s collagen framework can reduce its biomechanical strength. During cross-linking, riboflavin absorbs ultraviolet-A light within the corneal tissue and promotes new bonds between collagen fibers. These bonds increase corneal stiffness and can help limit further shape change.
A person may be considered for treatment when testing shows that keratoconus or ectasia is progressing. Evidence of progression can include increasing corneal steepness, thinning on corneal maps, worsening irregular astigmatism, or a change in prescription or vision over time. Younger people may be monitored particularly closely because progression can be more active at younger ages, but treatment decisions are individualized.
Assessment typically includes a full eye examination, refraction, corneal topography or tomography, and pachymetry to measure corneal thickness. The specialist also reviews contact lens use, eye rubbing, allergy symptoms, prior surgery, pregnancy status, medications, and general health. A cornea that is too thin for a standard protocol, active eye infection, significant corneal scarring, or certain other eye conditions may require a different approach or may mean that cross-linking is not advisable.
Keratoconus is one of the most common reasons for the procedure. More information about the condition is available in keratoconus.
Step-by-step: what happens during the procedure

Cross-linking is usually performed as an outpatient procedure under local anesthetic eye drops. The patient remains awake but should not feel sharp pain. The eye is held open with a small lid support, and the treatment team gives clear instructions about where to look. The treated eye is carefully cleaned and prepared.
In the most widely used epithelium-off approach, the thin outer corneal layer, called the epithelium, is gently removed. Riboflavin drops are then applied repeatedly for a set period so the medication can penetrate the cornea. The ophthalmologist confirms that the cornea is suitable to proceed and exposes it to a calibrated ultraviolet-A light while additional drops are used.
Some centers may offer epithelium-on or transepithelial techniques in selected circumstances, where the surface layer remains in place. The most appropriate method depends on corneal features and the clinician’s protocol. Research and clinical practice continue to refine these approaches, and expected results may differ between techniques.
At the end of epithelium-off treatment, a soft bandage contact lens is usually placed to protect the surface while it heals. The patient receives written aftercare instructions, prescribed eye drops, and a follow-up appointment. Someone else should arrange transport home because vision is commonly blurred immediately after treatment.
Benefits, limitations, and possible risks
The main expected benefit of cross-linking is stabilization: reducing the likelihood that the cornea will continue to bulge, thin, or become more irregular. Many treated eyes remain stable over long-term follow-up, although no procedure can guarantee that progression will stop in every person. By slowing progression, cross-linking may reduce the future need for more invasive treatment, including corneal transplantation, in appropriate patients.
Cross-linking is not primarily a refractive procedure. Some people notice improved corneal shape or vision over time, but others continue to need glasses or contact lenses, and visual rehabilitation may take months. Existing corneal scars or advanced irregularity may limit the visual improvement that is possible.
Temporary discomfort, tearing, redness, light sensitivity, haze, and blurred vision are common during recovery, especially with epithelium-off treatment. Less common but important complications include infection, delayed surface healing, persistent haze or scarring, changes in vision, sterile inflammation, and rarely worsening of corneal clarity. Following the drop schedule, avoiding eye rubbing, and attending reviews help reduce risks and allow problems to be addressed promptly.
People should discuss individual benefits and risks with their cornea specialist. The decision is based on the pattern of progression, corneal thickness and shape, visual needs, and the health of both eyes.
How long does it take to recover from cross-linking eye surgery?
Recovery after cross linking eye surgery occurs in stages. With epithelium-off treatment, the corneal surface generally heals over several days, often while a bandage contact lens is in place. During this early period, discomfort, watering, light sensitivity, and blurred vision are expected. The lens is removed only when the clinician confirms that the surface has healed adequately.
Functional vision may begin to improve after the first week or two, but it can fluctuate for several weeks. The cornea may take several months to settle, and vision or corneal measurements can continue to change during that time. The exact timeline varies with the procedure technique, baseline corneal condition, healing response, and whether specialty contact lenses are used.
Follow-up appointments are an important part of recovery. The eye care team checks the epithelial healing, looks for signs of inflammation or infection, assesses corneal clarity, and later monitors corneal stability with scans. Patients should use only the drops and eye products recommended by their specialist.
In the short term, people should plan for reduced visual comfort and avoid scheduling demanding visual tasks immediately after treatment. Work or school return depends on symptoms and the nature of the activity; the ophthalmologist can provide individualized guidance.
How long after corneal cross-linking can I drive?
Driving should not be resumed on the day of corneal cross-linking. An adult companion should take the patient home because the treated eye may be blurred, sensitive to light, and affected by dilating or anesthetic drops. Sedation, if used, is another reason not to drive.
Many people need at least several days before they can consider driving, particularly after epithelium-off treatment. However, the correct time is not determined by the calendar alone. Driving should wait until vision is sufficiently clear and comfortable, glare and light sensitivity are manageable, and the person meets local visual requirements for driving.
The ophthalmologist should confirm when returning to driving is reasonable, usually after assessing healing at follow-up. People who drive professionally, drive at night, or depend heavily on precise vision may need a longer period and should ask for specific advice. If vision becomes more blurred, painful, or increasingly red, driving should be avoided and the eye clinic contacted.
What not to do after crosslinking?
During early healing, the treated eye should not be rubbed, pressed, or exposed to unclean water. Patients should avoid swimming pools, hot tubs, lakes, and the sea until their ophthalmologist says the eye surface has healed. Eye makeup, creams close to the eyelid margin, and non-prescribed eye drops should also be avoided until clearance is given.
It is important not to remove or handle a bandage contact lens unless the eye care team specifically instructs otherwise. Contact lenses should not be restarted without medical advice, even if the eye begins to feel better. Patients should use prescribed antibiotic, anti-inflammatory, lubricating, or pain-relief medicines exactly as directed and should not share eye drops with anyone else.
For the first days, it is sensible to limit dusty environments, strenuous activities that increase the chance of being hit in the eye, and tasks that worsen discomfort from bright light or prolonged screen use. Protective sunglasses can improve comfort outdoors. Routine washing and showering can usually continue carefully, while avoiding direct water or soap in the treated eye.
Longer-term, controlling eye allergies and avoiding eye rubbing are especially important for people with keratoconus. Persistent itching should be discussed with an ophthalmologist so that safe treatment options can be considered.
How painful is cross-linking eye surgery and when to seek medical care
During cross-linking, anesthetic drops generally prevent pain, although a person may feel pressure, awareness of the eyelid support, or mild irritation. After epithelium-off treatment, discomfort can range from scratchiness and burning to more noticeable pain for the first few days while the surface heals. Light sensitivity and tearing are also common. Prescribed medication and lubricating drops are used to make this period more manageable.
Severe pain is not something to simply wait out. Patients should contact their eye clinic promptly if pain is worsening rather than improving, if there is increasing redness, thick discharge, a marked decline in vision, a new white spot on the cornea, fever with eye symptoms, or if the bandage lens falls out early. These symptoms do not always indicate a serious problem, but they need timely assessment.
Scheduled follow-up remains necessary even when recovery seems smooth. Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals assess and treat corneal conditions for international patients, with care plans based on individual eye findings and follow-up needs.
Frequently asked questions
01Is cross linking eye surgery permanent?
Cross-linking creates additional bonds within corneal collagen and is intended to provide lasting strengthening. In many people, it stabilizes corneal progression for the long term, but outcomes vary and ongoing monitoring is still needed. In some cases, further treatment may be considered if progression continues.
02Will cross-linking improve vision?
The primary aim is to slow or stop worsening of keratoconus or ectasia, not to correct vision like laser refractive surgery. Some people experience improved corneal shape or vision over time, while others continue to need glasses or specialty contact lenses. The result depends on the cornea before treatment and its healing response.
03Can both eyes be treated at the same time?
Whether both eyes can be treated together depends on the specialist's assessment, the treatment protocol, and the person's practical needs during recovery. Treating one eye at a time may allow the other eye to provide more useful vision while the first eye heals. The care team can explain the safest plan for each situation.
04How long should I avoid screens after corneal cross-linking?
There is usually no fixed screen restriction, but screens can worsen dryness, light sensitivity, and discomfort during the first days. Short periods with regular breaks may be more comfortable than prolonged use. The patient should follow the treating ophthalmologist's advice and stop if screen use causes significant symptoms.
05Can I wear contact lenses after cross-linking?
Contact lens use is usually paused during initial healing, and the bandage lens used after epithelium-off treatment should only be managed by the eye care team. Regular or specialty lenses can be restarted when the corneal surface is healed and the ophthalmologist confirms it is appropriate. A new lens fitting may be needed after the cornea stabilizes.
06What happens if I rub my eyes after cross-linking?
Rubbing can irritate the healing corneal surface and may dislodge a bandage contact lens if one is in place. It is particularly important for people with keratoconus to avoid habitual eye rubbing because it may contribute to corneal stress. If itching is troublesome, the patient should ask the eye specialist about safe allergy management.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.