Vasculitis Rash on Ankles: Signs to Assess
A vasculitis rash on ankles commonly appears as red, purple, or brown spots that do not fade when pressed, sometimes with small raised bumps. It can be limited to the skin, but because it may occasionally signal inflammation affecting other organs, a new rash should be assessed by a qualified clinician.
What does a vasculitis rash on ankles look like?
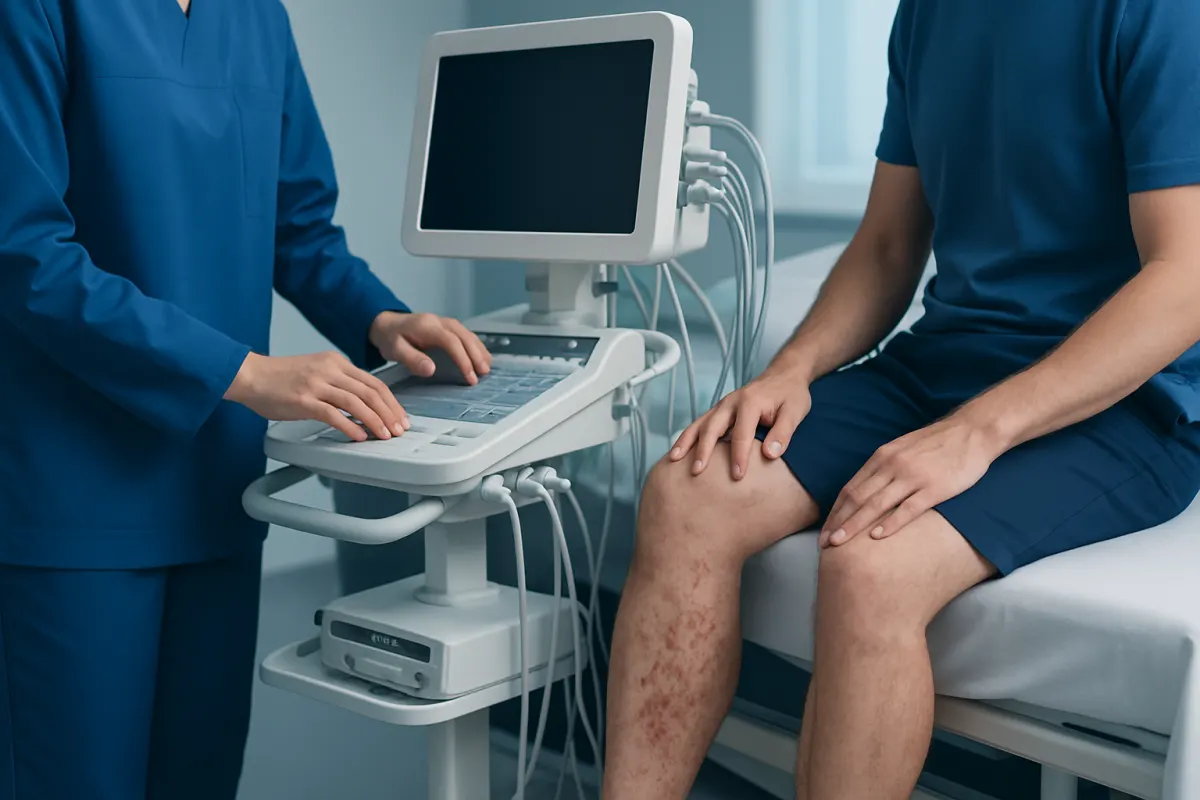
A vasculitis rash on ankles occurs when inflammation affects small blood vessels in the skin. Blood can leak from these inflamed vessels into the surrounding tissue, creating pinpoint spots or larger patches that look red, purple, reddish-brown, or bruise-like. The rash is often most noticeable around the ankles, feet, and lower legs because gravity and pressure in the leg veins can make this area more susceptible.
A classic finding is palpable purpura: purple-red spots that do not turn pale or disappear when gentle pressure is applied and may feel slightly raised. Individual spots may be a few millimeters wide or merge into larger areas. They can be painless, but some people notice itching, stinging, burning, tenderness, or mild swelling around the ankles.
The appearance can vary with skin tone. On lighter skin, lesions may be red or purple; on deeper skin tones, they may look dark purple, brown, grayish, or like new bruising. Over days to weeks, lesions may fade through brownish shades as the blood pigment is reabsorbed. A rash alone cannot confirm vasculitis, since infections, allergic reactions, bleeding disorders, vein problems, insect bites, and other skin conditions may look similar.
Why the ankles and lower legs are commonly affected
Small-vessel vasculitis often favors dependent parts of the body, especially the lower legs. When a person is standing or sitting, gravity increases pressure in the small vessels of the ankles and calves. This may make inflammation and leakage more visible there than on the upper body.
Heat, prolonged standing, walking, and leg swelling can sometimes make the rash more prominent or uncomfortable. This pattern does not mean that every ankle rash is vasculitis. For example, venous insufficiency can cause ankle swelling and brown discoloration, while contact dermatitis may cause a very itchy rash after exposure to footwear, socks, creams, or plants.
Clinicians consider the pattern alongside other features. Vasculitis is more likely when spots are non-blanching, raised, and occur in clusters on both lower legs. Blisters, small open sores, or blackened areas can occur in more severe skin inflammation and should be evaluated without delay.
Common triggers and possible causes

Cutaneous small-vessel vasculitis is an immune-mediated condition. In many cases, the immune system becomes activated and immune deposits contribute to inflammation in small skin vessels. The resulting condition may remain confined to the skin, or it may be part of a broader inflammatory illness affecting other areas of the body.
A recent infection can be a trigger, including respiratory, throat, or gastrointestinal infections. Some medicines may also be associated with a vasculitic rash, such as certain antibiotics, anti-inflammatory medicines, diuretics, or other prescription drugs. A suspected medicine should not be stopped without advice from the clinician who prescribed it, unless urgent medical care advises otherwise.
Other possible associations include autoimmune diseases, inflammatory bowel disease, chronic infections, and, less commonly, cancers or blood disorders. Some cases are linked with immunoglobulin A vasculitis, which may also cause joint pain, abdominal symptoms, or kidney involvement. However, extensive testing is not always necessary for every person; the appropriate tests depend on the rash, medical history, age, medicines, and accompanying symptoms.
Even after assessment, no specific trigger is identified in a substantial proportion of skin-limited cases. This is called idiopathic vasculitis. Not finding a cause does not mean symptoms should be ignored; follow-up helps confirm that the condition is settling and that there are no signs of involvement beyond the skin.
Symptoms that may occur with the rash
Skin symptoms may develop suddenly over a few days. New crops of spots can appear while older areas fade, and the rash may persist for several weeks. In addition to palpable purpura, some people develop flat purple spots, tiny blood-filled blisters, hives that last longer than a day, shallow ulcers, or painful nodules.
It is important to notice symptoms beyond the skin. Aching or swelling of the ankles, knees, wrists, or other joints may occur, particularly with certain forms of vasculitis. Fever, fatigue, reduced appetite, or unintentional weight loss can indicate a more general inflammatory process, though these symptoms also have many other possible causes.
Possible signs of organ involvement include dark, red, or foamy urine; reduced urination; abdominal pain; nausea or blood in the stool; cough, shortness of breath, or coughing blood; tingling, weakness, or new numbness in the hands or feet. These symptoms do not prove that vasculitis is affecting an organ, but they warrant timely medical assessment.
- Non-blanching spots: color remains when a clear glass or finger is gently pressed over the area.
- Palpable lesions: spots feel raised rather than completely flat.
- Symmetrical lower-leg distribution: both ankles or calves may be involved, although this is not universal.
- Changing lesions: new spots may develop over several days while older ones turn brown as they heal.
How clinicians diagnose an ankle vasculitis rash
Diagnosis begins with a careful medical history and skin examination. A clinician may ask when the rash began, whether it follows an infection or a new medicine, whether it is itchy or painful, and whether there are symptoms involving the joints, stomach, kidneys, lungs, or nerves. Photographs showing how the rash has changed can be useful, especially if lesions come and go.
Basic investigations may include a urine test, blood count, kidney and liver function tests, and markers of inflammation. Urine testing is particularly important because kidney involvement can sometimes be present before a person notices obvious urinary symptoms. Depending on the clinical picture, further blood tests may look for immune, infectious, or autoimmune causes.
A skin biopsy is often the most direct way to confirm cutaneous vasculitis. It involves removing a small sample of a fresh lesion under local anesthetic for examination in a laboratory. For the best diagnostic yield, clinicians commonly prefer a newly developed lesion rather than an older fading spot. Additional imaging or specialist assessment is considered when symptoms suggest involvement beyond the skin.
Prompt and accurate evaluation also helps rule out other causes of purpura, including low platelet counts, clotting problems, serious infections, and medication-related bleeding. The specific tests and urgency of care are individualized rather than based on the rash alone.
Treatment and practical self-care
Treatment depends on the severity, the underlying cause, and whether organs other than the skin are affected. If vasculitis is limited to the skin and symptoms are mild, it may improve with time after a trigger has resolved or has been addressed. A clinician may recommend rest, elevating the legs when possible, avoiding long periods of standing, and using comfortable clothing that does not rub irritated skin.
For discomfort, clinicians may suggest symptom-relieving treatment appropriate to the individual’s health history. It is important to seek advice before using anti-inflammatory pain medicines, particularly for anyone with kidney disease, stomach ulcers, blood-thinning treatment, or suspected kidney involvement. Scratching should be avoided where possible because broken skin can become infected.
If a medicine is thought to be the likely trigger, the prescriber may recommend an alternative. When there is persistent, painful, ulcerating, widespread, or recurrent skin disease, a dermatologist, rheumatologist, or other specialist may consider anti-inflammatory or immune-modifying treatment. Treatment for systemic vasculitis is more individualized and may require coordinated specialist care and monitoring.
Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals assess inflammatory skin symptoms and related systemic conditions for international patients. Care plans are based on the suspected type of vasculitis, test findings, overall health, and the person’s symptoms.
When to seek medical care
A new unexplained purple or red rash on the ankles should be reviewed by a doctor, particularly if it does not fade under pressure, is spreading, or lasts more than a few days. Medical assessment is also sensible after a recent infection or after starting a new medicine, because identifying a possible trigger can guide safe treatment decisions.
Urgent same-day medical care is needed if the rash is accompanied by fever and feeling very unwell, rapidly spreading dark or purple spots, severe pain, blistering, open sores, swelling of the face or throat, difficulty breathing, confusion, or fainting. These features can have causes other than vasculitis but should not be managed at home.
Prompt medical advice is also important for blood in the urine or stool, dark or foamy urine, reduced urination, significant abdominal pain, repeated vomiting, chest pain, shortness of breath, coughing blood, or new weakness or numbness. People with known kidney disease, autoimmune disease, a bleeding disorder, or a weakened immune system should contact their healthcare team early if this type of rash develops.
Until reviewed, it can help to record the timing of symptoms, take clear photographs in good light, and list all prescription medicines, over-the-counter products, supplements, and recent illnesses. This information can make the clinical assessment more efficient and accurate.
Frequently asked questions
01Can vasculitis cause a rash only on the ankles?
Yes. Small-vessel vasculitis often affects the ankles and lower legs first because gravity increases pressure in vessels in these areas. The rash can remain skin-limited, but a clinician should assess a new non-blanching rash to determine whether further tests are needed.
02Does a vasculitis rash fade when pressed?
Typically, the red-purple spots of vasculitis do not fade or turn white when pressed because blood has leaked outside small vessels. This is called non-blanching purpura. However, a pressure test cannot diagnose the cause, so medical evaluation remains important.
03Is vasculitis rash on ankles itchy?
It can be itchy, but it may also burn, sting, feel tender, or cause no discomfort at all. Severe pain, blisters, ulcers, or rapidly worsening skin changes should be assessed promptly.
04Can medications trigger ankle vasculitis?
Some medications can be associated with cutaneous vasculitis, often after a new treatment has been started. A person should not stop a prescribed medicine on their own; they should contact the prescribing clinician or seek urgent care if they have severe symptoms.
05How long does a skin-limited vasculitis rash last?
Many skin-limited episodes improve over several weeks, although new spots can appear for a period before the rash settles. Brownish discoloration may remain temporarily after inflammation resolves. Persistent, recurrent, or worsening rash needs follow-up.
06Can vasculitis affect the kidneys?
Some forms of vasculitis can affect the kidneys, which is why urine testing is often part of the assessment. Blood in the urine, foamy urine, swelling, or reduced urination should be reported promptly, although kidney involvement may initially cause no obvious symptoms.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.