Cancerous Ear Tumor: Diagnosis, Outlook, and Treatment
A cancerous ear tumor is an uncommon growth that may begin in the skin of the outer ear, ear canal, middle ear, or nearby structures. Early assessment is important because symptoms can resemble common ear or skin conditions, while timely diagnosis helps guide effective, individualized treatment.
Overview: What Is a Cancerous Ear Tumor?
A cancerous ear tumor is a malignant growth involving any part of the ear. It may arise on the visible outer ear (pinna), within the ear canal, in the middle ear, or, rarely, in deeper structures near the inner ear. The term can describe several different cancers rather than one single disease.
Most tumors found on the outer ear are skin cancers, commonly basal cell carcinoma or squamous cell carcinoma. Melanoma and less common skin cancers may also affect this sun-exposed area. Cancers that start in the ear canal or middle ear are uncommon, but they require careful specialist evaluation because of the ear’s close relationship to the facial nerve, skull base, jaw, and hearing structures.
Not every lump, scab, infection-like symptom, or area of irritation is cancer. Benign cysts, eczema, chronic infection, trauma, and noncancerous skin growths can cause similar changes. However, a change that does not heal or keeps returning should not be assumed to be harmless.
Symptoms That May Need Assessment
Symptoms vary according to where the tumor begins. A cancer on the outer ear may look like a pearly bump, a scaly patch, a thickened area, a changing mole, or a sore that repeatedly crusts, bleeds, or fails to heal. It may be painless at first.
A tumor in the ear canal or middle ear can cause persistent discharge, bleeding, earache, a blocked-ear sensation, hearing loss, ringing in the ear, or repeated symptoms diagnosed as infection. These symptoms are much more often caused by noncancerous conditions, but persistence or progression warrants examination.
More advanced disease may cause a noticeable mass, numbness, weakness of facial muscles, difficulty moving part of the face, dizziness, enlarged lymph nodes in the neck, or severe ongoing pain. These signs do not confirm cancer, but they need prompt medical attention.
- A sore, scab, or ulcer on the ear that does not heal
- Unexplained bleeding or discharge from the ear
- A new or enlarging lump on or around the ear
- Persistent ear pain or progressive hearing change
- A changing dark, irregular, or multi-colored skin lesion
Types, Causes, and Risk Factors
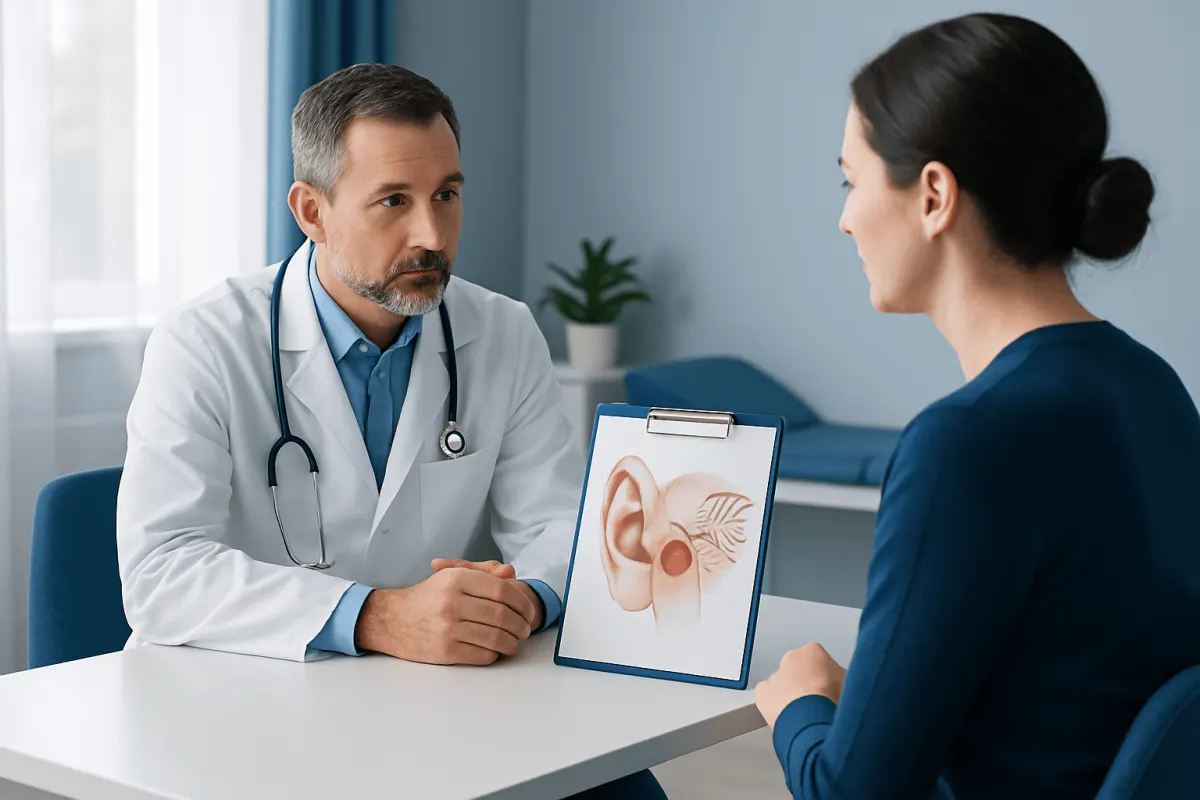
The type of cancer affects treatment and outlook. Basal cell carcinoma often develops on sun-exposed skin and usually grows slowly, although it can cause local damage if untreated. Squamous cell carcinoma may occur on the outer ear or in the ear canal and can be more likely to spread than basal cell carcinoma. Melanoma develops from pigment-producing cells and requires urgent assessment of any suspicious changing mole or dark lesion.
Rare cancers of the ear may arise from glands, connective tissue, or tissues lining the ear canal or middle ear. In some cases, cancer from nearby skin, salivary glands, or other head and neck sites can extend toward the ear rather than starting inside it.
Long-term ultraviolet exposure is a major risk factor for skin cancers of the outer ear. Other factors can include fair or easily sunburned skin, a history of skin cancer, older age, weakened immune function, prior radiation exposure, smoking for some head and neck cancers, and chronic inflammation or discharge from the ear. Having a risk factor does not mean that a person will develop cancer, and people without obvious risk factors can still be affected.
How a Cancerous Ear Tumor Is Diagnosed
Assessment usually begins with a clinical history and a detailed examination of the outer ear, ear canal, scalp, face, neck, and lymph nodes. An ear, nose, and throat specialist may examine the ear canal and eardrum using an otoscope or microscope. A dermatologist may assess a suspicious skin lesion with magnification techniques.
A biopsy is the essential test for confirming cancer. During this procedure, a clinician removes a small sample or, in some cases, the entire small lesion for laboratory examination. The pathology report identifies the cell type and provides information that helps the team plan treatment.
If cancer is confirmed or strongly suspected, imaging may be recommended to show whether the tumor has entered deeper tissues, bone, lymph nodes, or nearby structures. Depending on the situation, this may include CT, MRI, ultrasound, or PET-CT imaging. Hearing tests may also be useful before treatment when the canal, middle ear, or nearby structures are involved.
Specialists use the findings to determine the cancer stage where an accepted staging system applies. Staging describes the tumor’s size, local extent, lymph node involvement, and spread elsewhere in the body. It helps inform discussions about treatment options and expected outcomes.
Modern Treatment Approaches
Treatment is tailored to the cancer type, its exact location, depth, stage, and the person’s health and preferences. Care may involve dermatology, otolaryngology or head and neck surgery, plastic and reconstructive surgery, radiation oncology, medical oncology, radiology, pathology, and audiology.
Surgery is commonly used for localized cancers. For tumors on the outer ear, the goal is to remove the cancer with an appropriate margin while preserving appearance and function where possible. Reconstruction may use local tissue, skin grafts, or other techniques after removal. Some selected skin cancers may be treated with specialized margin-controlled surgery, often referred to as Mohs surgery, when preserving healthy tissue is especially important.
For cancers involving the ear canal or middle ear, surgery can be more complex and may involve removal of part of the canal, nearby bone, or other affected tissue. Radiation therapy may be used after surgery when there is a higher risk of recurrence, as the main treatment when surgery is not suitable, or to manage disease that cannot be completely removed. Radiotherapy is carefully planned to target the tumor while limiting exposure to nearby healthy structures.
Some advanced or recurrent cancers may be treated with systemic therapies, including immunotherapy, targeted therapy, or chemotherapy, depending on the cancer type and molecular features. Immunotherapy can be an option for certain skin cancers and head and neck cancers. A multidisciplinary cancer team can explain the expected benefits, possible side effects, and alternatives for an individual situation.
Outlook, Follow-Up, and Recovery
The outlook for a cancerous ear tumor depends mainly on the cancer type, how early it is identified, its size and depth, whether it involves bone or nerves, and whether it has reached lymph nodes or distant organs. Small cancers limited to the skin or superficial ear tissues are often highly treatable. Deeper ear canal and middle ear cancers may need more extensive treatment and close follow-up.
Follow-up is important after treatment because some cancers can recur locally or, less commonly, elsewhere. Follow-up appointments may include skin and ear examinations, neck examination, hearing evaluation, and imaging when clinically indicated. Patients should report new bleeding, pain, discharge, lumps, or changes near the treated area between scheduled visits.
Recovery can include wound care, management of swelling or discomfort, and support for hearing or cosmetic concerns. Reconstructive options and hearing rehabilitation can be discussed when needed. Emotional support is also valuable; a Prostate Cancer Diagnosis: Tests and Next Steps" class="ahp-ilk">cancer diagnosis and visible changes involving the ear can affect confidence, communication, and daily life.
Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals assess and treat ear and head and neck cancers for international patients, coordinating diagnostic, surgical, radiation, and supportive care when appropriate.
Prevention and When to Seek Medical Care
Not all ear cancers can be prevented, but protecting the outer ears from ultraviolet radiation can reduce the risk of common skin cancers. Helpful measures include applying broad-spectrum sunscreen to the ears and surrounding skin, wearing a wide-brimmed hat, seeking shade during intense sun exposure, and avoiding tanning beds. People with a prior skin cancer or reduced immune function may benefit from regular professional skin checks.
It is sensible to seek medical care for an ear sore or lesion that does not heal within several weeks, a spot that repeatedly bleeds or crusts, a changing mole, a new lump, or persistent ear discharge and pain. An ear symptom that repeatedly returns despite usual treatment should also be reviewed rather than continually self-treated.
Urgent medical evaluation is appropriate for new facial weakness, rapidly worsening hearing loss, significant bleeding, severe pain, marked dizziness, or a rapidly enlarging mass. These symptoms can have many causes, but early assessment is the safest approach. A qualified clinician can determine whether referral to dermatology, ENT, or an oncology team is needed.
Frequently asked questions
01Is a cancerous ear tumor common?
Cancer affecting the ear is uncommon overall. Skin cancers on the outer ear are more common than cancers that begin inside the ear canal or middle ear, largely because the outer ear receives sun exposure.
02Can an ear tumor be benign?
Yes. Many ear lumps and growths are benign, including cysts, skin tags, keloids, and some noncancerous gland or bone growths. A clinical examination and, when needed, biopsy are used to tell whether a lesion is benign or cancerous.
03What does ear cancer look like?
It may appear as a persistent scaly patch, sore, crusted area, bleeding lesion, pearly bump, or changing dark spot on the outer ear. Cancer inside the ear may not be visible and can instead cause discharge, pain, or hearing changes.
04How is a cancerous ear tumor confirmed?
A biopsy confirms the diagnosis by allowing a pathologist to examine tissue under a microscope. Imaging scans may then be used to understand the tumor’s size, depth, and relationship to nearby tissues.
05Can ear cancer affect hearing?
It can, particularly when a tumor involves the ear canal, eardrum, middle ear, or nearby bone. Hearing changes may also result from treatment, so hearing testing and rehabilitation are considered when appropriate.
06Is surgery always needed for an ear tumor?
No. Surgery is frequently used for localized tumors, but the best approach depends on the cancer type and location. Radiation therapy and systemic medicines may be used instead of or alongside surgery in selected situations.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Oncology care in Turkey — second opinion and treatment plan
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.