

Urinary Retention: Symptoms, Causes and Treatment

Key Takeaways
- Urinary retention means the bladder cannot empty fully or cannot empty at all.
- It may be acute, which is sudden and urgent, or chronic, which may develop slowly and be easier to miss.
- Common causes include blockage, medications, nerve problems, infection, and muscle weakness.
- Diagnosis often includes a physical exam, bladder scanning, urine tests, and sometimes imaging or specialist testing.
- Treatment depends on the cause and may involve catheter drainage, medicines, or procedures to relieve obstruction.
- Prompt medical evaluation is important if there is pain, a swollen lower abdomen, fever, or inability to pass urine.
Urinary retention happens when the bladder does not empty fully or at all, and it may appear suddenly or develop gradually. Understanding the signs, possible causes, and treatment options can help a person seek care at the right time and protect bladder and kidney health.
Overview
Urinary retention is the medical term for trouble emptying the bladder. Some people cannot pass urine at all, while others pass only small amounts and still feel full. In either case, urine remains in the bladder longer than it should, which can cause discomfort and sometimes lead to infection or strain on the kidneys.
The condition is usually described in two ways. Acute urinary retention comes on suddenly and is often painful and noticeable. Chronic urinary retention develops more slowly, and a person may not realize the bladder is not emptying well until symptoms become bothersome or a health check reveals the issue.
Because the bladder is part of the wider urinary system, the question is not only whether urine can be passed, but why it is not leaving the body normally. That is why the evaluation often looks beyond the bladder itself and includes the nerves, prostate, medications, and general health history.
Symptoms
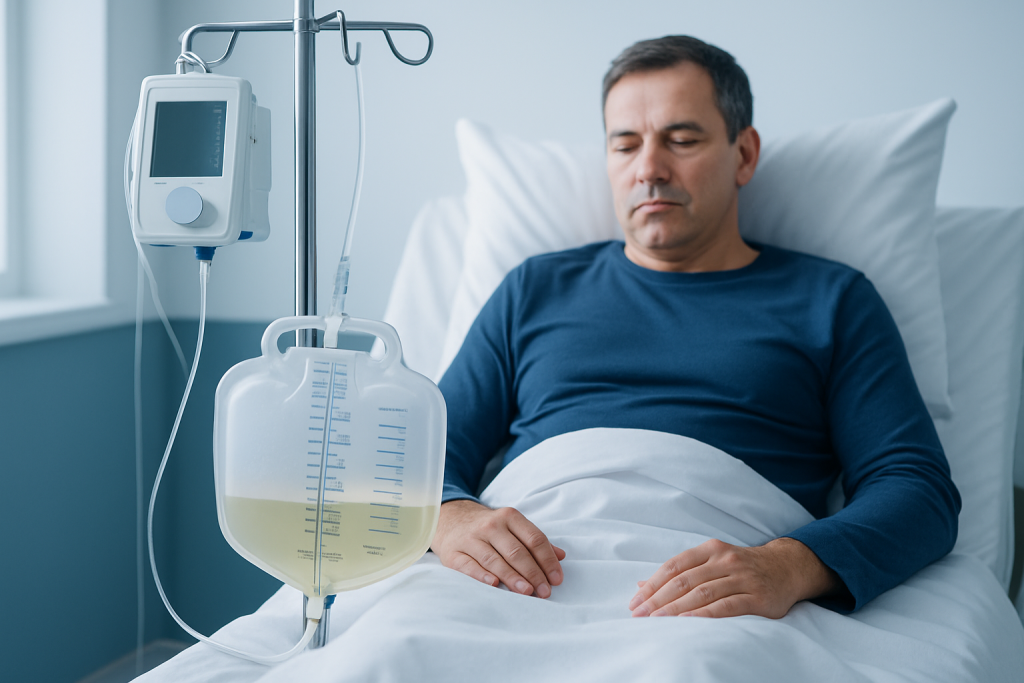
The symptoms depend on whether retention is sudden or gradual. Acute urinary retention often causes a strong urge to urinate with little or no urine coming out. The lower abdomen may feel painful, tight, or visibly swollen. This form is usually hard to ignore because it can become uncomfortable quickly.
Chronic urinary retention may be subtler. A person might urinate often, produce a weak stream, feel that the bladder never fully empties, or need to strain to start or keep the urine flowing. Some people notice dribbling after they think they are done, while others wake at night more often to urinate.
- Difficulty starting urination
- Weak urine stream
- Feeling of incomplete emptying
- Frequent urination in small amounts
- Lower abdominal pressure or discomfort
- Overflow dribbling or leakage
Symptoms can be more difficult to recognize in older adults or in people with nerve conditions, because they may not feel the usual urge to urinate as strongly. In those cases, routine medical follow-up may reveal the problem before it becomes severe.
Causes & Risk Factors

Urinary retention has several possible causes, and more than one may be present at the same time. A common pattern is physical blockage of the urinary tract, such as an enlarged prostate in men, narrowing of the urethra, bladder stones, constipation, or pelvic organ prolapse. When urine cannot pass through normally, the bladder may struggle to empty.
Another major group of causes involves nerve signaling. The bladder depends on nerves to know when to store urine and when to contract and empty. Conditions such as diabetes, spinal cord injury, stroke, multiple sclerosis, and some surgeries can disrupt those signals. In these situations, the bladder may not receive the message to empty, or the muscles may not contract effectively.
Medicines can also play a role. Some antihistamines, decongestants, antidepressants, opioid pain medicines, and drugs with anticholinergic effects can make urination harder for certain people. Infection, inflammation, and temporary swelling after surgery are additional contributors that may appear in otherwise healthy adults.
Risk is higher in people with a history of urinary tract problems, prostate enlargement, neurologic disease, diabetes, recent anesthesia, or prolonged immobility. Age can also increase risk, partly because bladder muscle strength, nerve function, and medication use change over time.
Diagnosis
Diagnosis starts with a detailed conversation about symptoms, timing, medications, prior surgeries, and any nerve or prostate-related conditions. The clinician will usually ask whether the person can urinate at all, how much comes out, and whether there is pain, fever, blood in the urine, or lower back discomfort.
A physical exam may include feeling the lower abdomen for bladder fullness and, when appropriate, a pelvic or prostate examination. A bladder scan, which uses ultrasound, can show how much urine remains after urination. This is one of the simplest ways to confirm incomplete emptying.
Testing may also include a urine test to check for infection or blood, blood tests to assess kidney function, and imaging if a blockage is suspected. In some cases, a specialist may recommend urodynamic testing or cystoscopy to understand how well the bladder and urinary tract are working. When a patient is traveling for care, these tests may be arranged close together so the cause can be identified efficiently and treatment can begin without unnecessary delay.
Treatment Options
Treatment depends on whether the problem is sudden or long-standing and on what is causing it. If the bladder is very full and the person cannot urinate, immediate drainage is often needed. This is typically done with a catheter, a thin tube that allows urine to leave the bladder and relieves pressure. The goal is comfort and safety, not only symptom control.
After the bladder is emptied, the next step is to address the underlying cause. If a medication is contributing, the prescriber may adjust the medicine or switch to another option. If an enlarged prostate is involved, medicines that relax the bladder neck or improve urine flow may be considered, and some people may need a procedure if the blockage is significant. In neurologic causes, management may focus on bladder training, intermittent catheterization, or treatment of the underlying condition.
Infection, constipation, or post-surgical swelling may improve with targeted treatment and time. For some people, especially those with chronic retention, a plan is built around regular follow-up, repeat bladder checks, and teaching safe catheter care if needed. This is often important for international patients, because the early recovery period may begin in one country and continue at home with a clear, written plan from the treating team.
When retention is caused by a structural problem, procedures or surgery may be discussed. The exact approach depends on the person’s age, general health, and the anatomy involved, so a specialist evaluation is essential before any decision is made.
Prevention & Self-care
Not every case of urinary retention can be prevented, especially when a nerve disorder or anatomic blockage is involved. Still, practical habits can reduce the chance that bladder emptying problems worsen or go unnoticed. One helpful step is reviewing medications with a clinician, particularly if a new drug seems to coincide with urinary changes.
Regular bathroom habits can also support bladder health. Some people benefit from allowing enough time to urinate without rushing, leaning slightly forward while seated, or trying a second attempt a few minutes later if the first pass feels incomplete. Constipation should be addressed promptly, since a backed-up bowel can press on the bladder and make urination harder.
- Keep follow-up appointments after surgery or a new diagnosis
- Report new trouble starting urine flow or weak stream early
- Stay hydrated unless a doctor has advised fluid restriction
- Avoid self-starting medicines that may worsen retention
- Monitor for changes in urine pattern if you have diabetes or a neurologic condition
For people recovering away from home, a written discharge plan matters. It should explain how to use any catheter, which symptoms should trigger medical contact, and when to return for a check. Clear instructions can make recovery safer and less stressful when the patient is managing care across borders.
When to See a Doctor
A person should seek medical care promptly if they cannot urinate, have significant lower abdominal pain or swelling, or notice that urine output has suddenly changed. These symptoms can indicate acute urinary retention, which should not be ignored.
It is also important to arrange evaluation if urination is becoming progressively weaker, bathroom trips are frequent but unproductive, or there is a feeling that the bladder never empties fully. Blood in the urine, fever, back pain, vomiting, or new confusion in an older adult deserve timely assessment as well.
Even when symptoms seem mild, chronic retention can quietly affect bladder function over time. A clinician can help determine whether the cause is temporary or needs longer-term treatment. In complex cases, multidisciplinary specialists and JCI-accredited hospitals such as those at Acibadem Health Point can help diagnose and treat urinary retention for international patients, with coordinated care before and after travel.
Living with Urinary Retention
Many people feel relieved once the cause is identified, because urinary retention is a symptom with several possible explanations rather than a single diagnosis. That means the treatment path can be very different from one person to another, and improvement often depends on matching the plan to the underlying issue.
Follow-up matters even after symptoms improve. Some patients need repeat bladder scans, medication review, or a stepwise plan for catheter use and removal. Others may need evaluation by a urologist, neurologist, or pelvic health specialist to prevent the problem from returning.
Questions are worth asking at every stage: What caused the retention? Is it safe to stop or change any medicines? Do I need a catheter temporarily or long term? Which warning signs should prompt urgent review? Clear answers help people stay confident and active while recovering.
Frequently asked questions
01Is urinary retention the same as not urinating at all?
Not always. Some people with urinary retention cannot pass urine, while others can urinate but still do not empty the bladder well. Both situations deserve medical attention because urine left behind can cause discomfort and complications.
02Can urinary retention go away on its own?
Sometimes a temporary cause, such as a medication effect or swelling after surgery, may improve when the trigger is addressed. However, a clinician should still evaluate the problem so the bladder is not left stretched or overfilled for too long.
03What is the first treatment if the bladder is full and I cannot urinate?
The first priority is usually to relieve the bladder by draining urine, often with a catheter. After that, the care team looks for the reason the retention happened and plans the next steps.
04Can constipation really affect urination?
Yes. A full bowel can press on the bladder or urethra and make urine flow more difficult. Treating constipation may improve bladder emptying in some people.
05Which medicines can cause urinary retention?
Several medicines can contribute, including some antihistamines, decongestants, antidepressants, opioid pain medicines, and drugs with anticholinergic effects. A doctor or pharmacist can review the full medication list to see whether one of them may be involved.
06Should someone with urinary retention travel for care?
Travel may be appropriate when a specialist evaluation, procedure, or coordinated follow-up is needed and the person is stable enough to travel. The important part is having a clear plan for bladder management, medications, and follow-up before leaving.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


