

Red Eardrum: Possible Causes and Clinical Significance
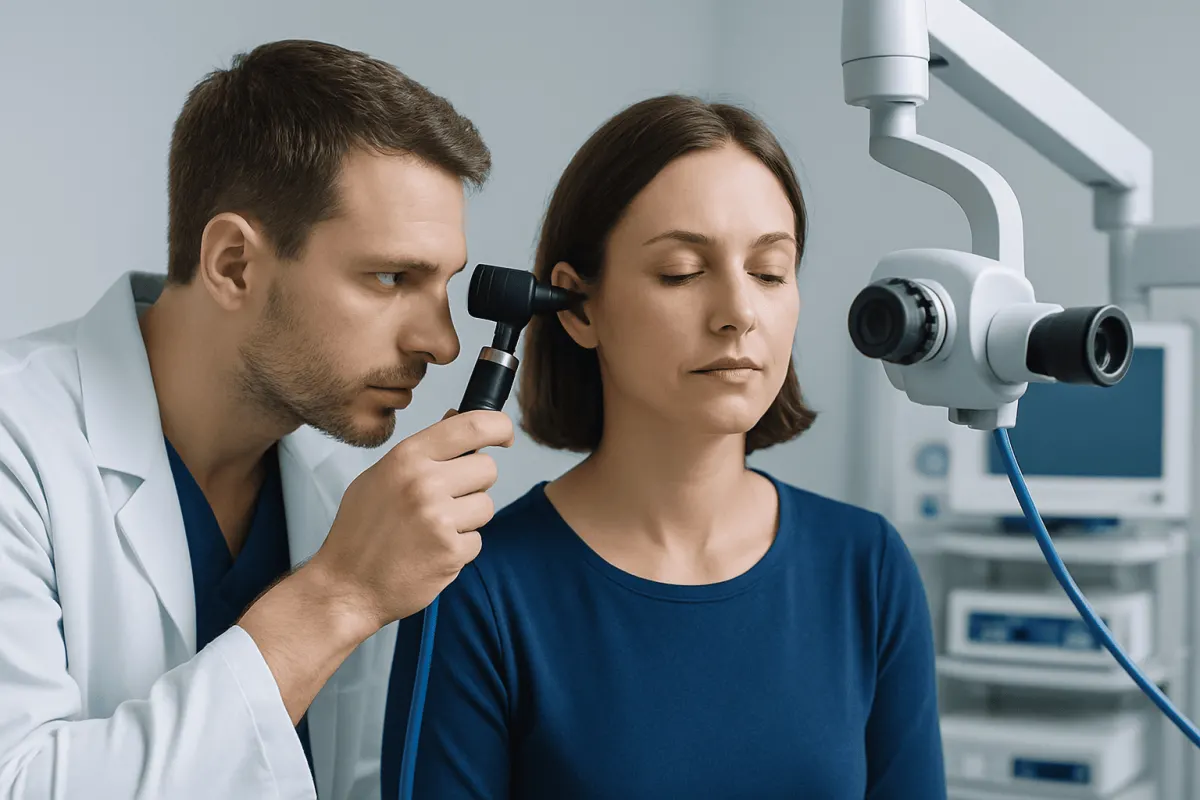
A red eardrum, also called a red tympanic membrane, is usually noticed during an ear examination rather than by the patient. It can occur with middle-ear infection, pressure changes, irritation, fever, or crying, so a clinician considers the full set of symptoms and the eardrum’s movement and appearance before making a diagnosis.
What does a red eardrum mean?
A red eardrum means that the tympanic membrane, the thin tissue separating the ear canal from the middle ear, looks more pink or red than usual when viewed with an otoscope. It may suggest inflammation or increased blood flow, but redness alone does not confirm an ear infection. A clinician also looks for bulging, fluid behind the eardrum, reduced movement, a perforation, or changes in the ear canal.
The eardrum normally appears pearly gray and slightly translucent. Its color can change briefly for everyday reasons, including crying, coughing, straining, fever, or a recent upper respiratory infection. Lighting, the viewing angle, and the examination technique can also affect how red it appears.
A red eardrum is common in children because colds and middle-ear problems are frequent in early life. However, adults can also develop this finding, particularly during respiratory infections, allergies, sinus symptoms, or changes in air pressure. The meaning depends on the person’s symptoms, medical history, and examination results.
Symptoms that may occur with a red eardrum
Some people with a red eardrum have no ear symptoms. In this situation, the finding may be temporary or related to a mild viral illness. Others may have symptoms that point toward inflammation or infection in the middle ear, such as earache, pressure, fullness, muffled hearing, or difficulty hearing soft sounds.
In babies and young children, ear discomfort can be less specific. A child may tug at the ear, cry more than usual, sleep poorly, feed less, or seem unusually irritable. Fever may occur, but it is not present in every case and does not by itself establish an ear infection.
Additional symptoms can help distinguish middle-ear concerns from problems affecting the outer ear. Itching, pain when the outer ear is pulled, or tenderness around the ear canal may be more consistent with outer-ear inflammation. Nasal congestion, sore throat, cough, and recent cold symptoms commonly accompany pressure changes or fluid in the middle ear.
- Ear pain, pressure, or a blocked feeling
- Temporary hearing reduction or popping sensations
- Fever or recent cold symptoms
- Fluid or discharge from the ear
- Balance symptoms, nausea, or dizziness in some cases
Common causes and contributing factors

Acute otitis media, commonly called a middle-ear infection, is an important cause of a red eardrum. It often develops after a viral cold causes swelling near the Eustachian tube, the passage that helps ventilate the middle ear. Fluid can then collect behind the eardrum, and bacteria may sometimes contribute to infection. In acute otitis media, a bulging eardrum or new ear drainage is generally more informative than redness alone.
Middle-ear fluid without active infection, known as otitis media with effusion, can also create pressure, hearing changes, and an altered eardrum appearance. This often follows a cold or an ear infection and may resolve over time. Allergies, chronic nasal inflammation, enlarged adenoids in children, and exposure to tobacco smoke can contribute to Eustachian tube dysfunction.
Other possibilities include temporary vascular flushing from fever, crying, vigorous coughing, vomiting, or anxiety during an examination. Irritation after swimming, skin conditions affecting the ear canal, injury from inserting objects into the ear, and pressure changes during flying or diving may also cause ear symptoms and visible redness.
Risk factors for middle-ear problems include young age, frequent viral respiratory infections, attendance at group childcare, passive smoke exposure, and certain craniofacial or immune conditions. These factors do not mean that a person will develop an infection, but they can help a clinician interpret repeated symptoms.
How clinicians evaluate a red eardrum
A healthcare professional begins by asking about pain, fever, hearing changes, recent colds, swimming, travel, allergies, and previous ear problems. They will examine both ears, the nose, throat, and surrounding tissues. Comparing the two ears can be useful because a person’s normal eardrum appearance may vary slightly.
Otoscopy allows the clinician to inspect the eardrum for redness, opacity, fluid levels, retraction, bulging, holes, scarring, or drainage. Pneumatic otoscopy, which gently changes air pressure in the ear canal, can help assess whether the eardrum moves normally. Limited movement may indicate fluid or pressure behind it.
In selected cases, tympanometry may be used to measure how the eardrum responds to pressure changes. Hearing testing may be recommended when hearing loss is persistent, when middle-ear fluid lasts for an extended period, or when recurrent ear concerns affect speech, learning, work, or daily communication.
Most uncomplicated cases do not require scans or blood tests. Further testing is considered only when symptoms are unusual, severe, recurrent, or suggest a complication or another condition. A careful examination is important because treating redness alone, without confirming the cause, may lead to unnecessary medication.
Treatment options and supportive care
Treatment depends on the underlying cause. When a red eardrum is associated with a viral cold, mild pressure changes, or short-lived irritation, care may focus on rest, fluids, and symptom relief. Pain can often be managed with age-appropriate over-the-counter pain medicine when it is safe for the individual and used according to a clinician’s or product label’s instructions.
Not every middle-ear infection needs antibiotics. Many mild cases, particularly in otherwise well children and adults, improve with observation and pain control. A clinician may recommend antibiotics when examination findings and symptoms support a bacterial infection, or when a person is very young, significantly unwell, has severe symptoms, has certain health risks, or does not improve as expected.
If fluid remains after an infection, clinicians may recommend monitoring because it often clears gradually. Persistent fluid, repeated infections, or ongoing hearing concerns may require assessment by an ear, nose, and throat specialist. Management may include hearing evaluation and, for selected patients, procedures to improve middle-ear ventilation.
Ear drops should only be used when advised by a qualified clinician. Some drops are not appropriate if there is a hole in the eardrum or ear tubes are present. It is also important not to use leftover antibiotics, insert objects into the ear, or try to remove suspected wax or fluid with cotton swabs.
Prevention and everyday ear care
Many ear infections cannot be completely prevented, especially in young children who commonly catch viral illnesses. However, reducing respiratory infection exposure where practical, keeping recommended vaccinations up to date, and avoiding tobacco smoke can support ear and respiratory health. Handwashing and staying home when acutely unwell can also reduce the spread of cold viruses.
For infants, feeding in a more upright position rather than while lying flat may help reduce reflux of milk toward the Eustachian tube. Parents and caregivers should avoid placing cotton swabs or other objects into a child’s ears. Earwax normally protects the ear canal and usually moves outward naturally.
During air travel, swallowing, chewing gum when age-appropriate, drinking fluids, or using a pacifier for an infant during descent may help equalize ear pressure. People with a significant cold, severe nasal congestion, or a recent ear procedure should ask a clinician whether flying or diving is advisable.
People with recurring ear symptoms may benefit from discussing allergies, nasal congestion, frequent sinus symptoms, or smoking exposure with a healthcare professional. Addressing these contributing factors can sometimes reduce pressure-related ear discomfort and repeat middle-ear fluid problems.
When to seek medical care
Medical assessment is advisable for ear pain that is severe, lasts longer than a day or two, repeatedly returns, or occurs with fever or reduced hearing. Children under six months with possible ear Sinus Infection Symptoms: Causes and Treatment" class="ahp-ilk">infection symptoms should be assessed promptly. Parents should also seek advice if a child seems unusually sleepy, difficult to console, is drinking poorly, or is not improving as expected.
Urgent medical care is needed for swelling, redness, or marked tenderness behind the ear; an ear that appears pushed forward; severe headache; stiff neck; confusion; weakness of the face; severe dizziness; or persistent vomiting. These symptoms are uncommon but need prompt evaluation because they can indicate a more serious problem.
Ear drainage, particularly blood, pus, or clear fluid after an injury, should also be assessed. Sudden or substantial hearing loss requires timely medical attention. A clinician can determine whether the eardrum is intact and whether infection, injury, wax, or another ear condition is responsible.
For international patients needing evaluation of ongoing ear concerns, Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals can assess and treat ear conditions with appropriate diagnostic support. Individual care plans should always be based on an in-person clinical evaluation.
Frequently asked questions
01Does a red eardrum always mean an ear infection?
No. A red eardrum can occur with an ear infection, but it may also be caused by crying, fever, coughing, irritation, or a recent cold. Clinicians look for other signs, especially bulging, fluid behind the eardrum, reduced movement, and relevant symptoms, before diagnosing an infection.
02Can a cold cause a red eardrum?
Yes. A cold can inflame the nose and Eustachian tubes, which may alter pressure in the middle ear and affect the eardrum’s appearance. Viral infections can also cause temporary redness without a bacterial middle-ear infection.
03How long does a red eardrum last?
The duration depends on the cause. Redness related to temporary irritation or a viral illness may settle as symptoms improve, while middle-ear fluid can remain for longer after an infection has resolved. Persistent pain, hearing changes, or recurrent symptoms should be reviewed by a healthcare professional.
04Is a red eardrum contagious?
The red eardrum itself is not contagious. However, a cold or other respiratory virus that contributes to ear inflammation can spread from person to person. Good hand hygiene and avoiding close contact when acutely unwell can help limit viral transmission.
05Should a person use ear drops for a red eardrum?
Ear drops should not be used unless a clinician recommends a specific product. The correct treatment depends on whether the issue is in the outer ear, middle ear, or eardrum, and some drops are unsafe if the eardrum is perforated. Avoid putting oils, peroxide, or leftover medicines into the ear without medical advice.
06Can a red eardrum cause hearing loss?
Redness itself does not usually cause hearing loss. If fluid or pressure builds behind the eardrum, sound may not travel normally and hearing can become temporarily muffled. Persistent, sudden, or significant hearing loss should be assessed promptly.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


