Posterior Nosebleeds: When Deep Nasal Bleeding Needs Care

A posterior bleeding nose, also called a posterior nosebleed, begins deep in the nasal cavity and may cause blood to flow into the throat as well as out of the nostrils. It is less common than a front-of-the-nose bleed but can be harder to control, so prompt medical assessment is often appropriate.
Overview: what is a posterior bleeding nose?
A posterior bleeding nose is a nosebleed that starts from blood vessels deep in the back of the nasal cavity. The medical term for any nosebleed is epistaxis. Most nosebleeds begin near the front of the nasal septum, the wall between the nostrils, where vessels are close to the surface. Posterior bleeding is less frequent, but it can involve larger vessels and may be more difficult to stop without medical help.
Because the bleeding point is farther back, blood may flow from one or both nostrils, drip into the throat, or do both. A person may notice a persistent metallic or salty taste, need to spit out blood, cough, or feel nauseated after swallowing blood. The amount seen from the nose does not always reflect the amount of bleeding, particularly when much of it is travelling into the throat.
Although a posterior nosebleed can look dramatic, effective treatments are available. The priority is to control the bleeding safely, protect the airway, and identify factors that may have contributed. People who suspect posterior bleeding should seek medical assessment, especially if bleeding is heavy, recurrent, or does not stop with correct first aid.
How posterior bleeding differs from a common nosebleed
Anterior nosebleeds are the more familiar type. They often occur after dry air, a cold, allergies, nose blowing, minor injury, or picking the nose. They commonly bleed from one nostril and can often be managed at home with steady pressure. Posterior bleeding tends to occur deeper in the nose and is more likely to continue despite simple first-aid measures.
It is not always possible to tell the exact source at home. However, bleeding that is heavy, appears to come from both nostrils, repeatedly runs down the back of the throat, or continues for longer than about 15 to 20 minutes of uninterrupted pressure should be treated as potentially significant. Feeling faint, weak, short of breath, or unwell is also important, regardless of where the bleeding started.
A clinician can examine the nose with appropriate lighting and instruments to locate the likely source. Sometimes blood from a front-of-the-nose bleed can run backward when a person lies down or tilts their head back, which is one reason remaining upright and leaning forward is recommended during first aid.
Causes and risk factors

Posterior nosebleeds may happen when a blood vessel at the back of the nasal cavity breaks. In some cases there is no single clear trigger. Dryness and irritation of the nasal lining, respiratory infections, sinus inflammation, forceful nose blowing, and trauma to the face or nose can all contribute to bleeding.
Risk increases with age because blood vessels and nasal tissues can become more fragile. High blood pressure may make a nosebleed harder to control, though it is not always the original cause. Medicines that affect clotting, including anticoagulants, antiplatelet medicines, and some anti-inflammatory pain medicines, can increase the likelihood or duration of bleeding. A person should never stop a prescribed blood-thinning medicine on their own because of a nosebleed; a doctor should advise on any changes.
Less commonly, repeated or unexplained bleeding may be related to a bleeding or platelet disorder, liver disease, nasal structural problems, or an abnormal growth in the nose or sinuses. These causes are not the usual explanation, but they are reasons a doctor may recommend further examination when nosebleeds recur, occur on one side repeatedly, or are accompanied by persistent blockage, pain, or other concerning symptoms.
What to do during a nosebleed
For immediate first aid, the person should sit upright and lean slightly forward. They should gently blow the nose once if there are large clots obstructing it, then pinch the soft part of the nose just below the bony bridge. Pressure should be firm and continuous for 15 minutes, timed without repeatedly checking whether the bleeding has stopped. Breathing through the mouth is expected during this time.
Leaning forward helps prevent blood from being swallowed. The head should not be tipped backward, and the person should not lie flat. A cool compress across the bridge of the nose or cheeks may feel soothing, but it does not replace direct pressure. If available and suitable for the individual, a clinician or pharmacist may advise on a short-term nasal decongestant spray; this is not appropriate for everyone and should not delay urgent evaluation for significant bleeding.
After bleeding has stopped, it is sensible to avoid strenuous activity, hot drinks, alcohol, forceful nose blowing, bending heavily, and picking the nose for at least 24 hours. Keeping the nasal passages moist with saline spray or gel and using a humidifier during dry weather may help reduce irritation. If bleeding resumes, repeat firm pressure and seek medical care if it does not settle promptly.
How doctors diagnose and treat posterior nosebleeds
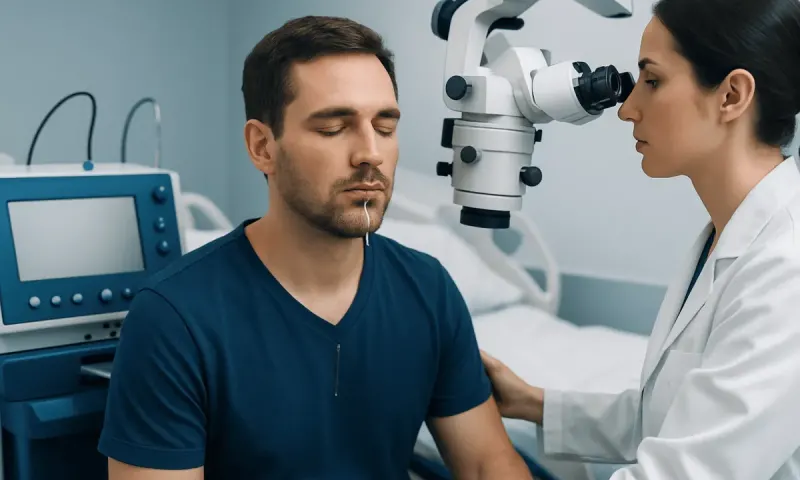
Medical assessment begins with checking the person’s general condition, including pulse, blood pressure, and signs of substantial blood loss. The clinician will ask about the timing and pattern of bleeding, recent injury or illness, previous nosebleeds, and medicines. Examination may include looking inside the nose after suctioning clots and applying a local anaesthetic or vasoconstrictor medicine to improve visibility.
When bleeding is mild and a source can be seen, a clinician may treat it with chemical or electrical cautery. Cautery seals a bleeding vessel and is usually performed only when the bleeding point is clearly identified. It should not be attempted at home. If the source is farther back or bleeding is more substantial, absorbable material or nasal packing may be placed to apply pressure inside the nose. Some people need observation in hospital, particularly if packing is used or if they have medical conditions that raise bleeding risk.
For persistent bleeding that does not respond to packing, specialists may use endoscopic surgery to control the responsible vessel or interventional radiology to block a bleeding artery from within the blood vessel. Blood tests may be requested when bleeding is severe, recurrent, or linked to possible clotting problems. Treatment is individualized, including careful review of medicines that affect bleeding and management of underlying conditions.
When to seek medical care
Emergency medical care is appropriate if bleeding is heavy, if it does not stop after 15 to 20 minutes of continuous correct pressure, or if blood is flowing freely into the throat. Urgent assessment is also important after a significant injury to the head or face, or when a person feels faint, confused, very weak, has chest discomfort, difficulty breathing, or shows other signs of being unwell.
People taking anticoagulants or antiplatelet medicines, those with a known bleeding disorder, and those with serious liver disease should have a lower threshold for contacting a doctor or emergency service. Children with persistent bleeding, adults with repeated episodes, and anyone who has needed nasal packing in the past should also seek timely advice if another significant episode occurs.
A non-urgent appointment with an ear, nose, and throat specialist may be helpful for recurring nosebleeds, one-sided blockage, ongoing crusting, or bleeding without an obvious trigger. Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals assess and treat ear, nose, and throat conditions for international patients when specialist care is needed.
Prevention and self-care after recovery
Many nosebleeds can be reduced by protecting the nasal lining. Regular saline spray, saline gel, or a thin layer of a clinician-recommended moisturizing product inside the front of the nostrils can help during dry seasons. A bedroom humidifier may also be useful where indoor heating or air conditioning causes dry air. It is important to keep humidifiers clean according to the manufacturer’s instructions.
Gentle nose care matters. People should avoid picking the nose, insert tissues or cotton buds only when medically advised, and blow the nose gently. Treating allergies, colds, or nasal inflammation with advice from a healthcare professional may reduce frequent rubbing and forceful blowing. Protective equipment should be used for sports or work where facial injury is possible.
For people with recurrent bleeding, a doctor can review blood pressure control, nasal medicines, supplements, and drugs that affect clotting. Prescribed treatment should not be stopped without professional guidance. Keeping a brief note of episodes, including their duration, likely trigger, side of the nose, and medicines taken, can make a medical assessment more informative.
Frequently asked questions
01Is a posterior bleeding nose dangerous?
A posterior bleeding nose can be more serious than a typical front-of-the-nose bleed because it may involve deeper, larger blood vessels and can be difficult to stop. It does not always mean there is a serious underlying disease, but heavy or persistent bleeding should be assessed urgently.
02How can a person tell if blood is coming from the back of the nose?
Blood repeatedly draining into the throat, bleeding from both nostrils, or bleeding that continues despite firm pressure may suggest a deeper source. Only a medical examination can confirm the location of the bleeding vessel.
03Should a person lean their head back during a nosebleed?
No. Leaning backward can cause blood to run into the throat and stomach, which may lead to coughing, choking, or nausea. The person should sit upright, lean forward slightly, and pinch the soft part of the nose continuously.
04Can high blood pressure cause posterior nosebleeds?
High blood pressure is not always the direct cause of a nosebleed, but it may make bleeding more difficult to control and is more common in people who have posterior nosebleeds. A clinician can check blood pressure and advise on long-term management if needed.
05Can blood thinners cause a posterior nosebleed?
Blood-thinning medicines can make any nosebleed more likely to continue or recur, even when they are not the original cause. A person should seek medical advice for significant bleeding but should not stop prescribed anticoagulant or antiplatelet medicine without instruction from the clinician who manages it.
06What happens if nasal packing is needed?
Nasal packing uses a soft absorbent material or inflatable device placed inside the nose to put pressure on the bleeding area. It may be uncomfortable, and some people need observation or follow-up for removal, but it is a commonly used way to control bleeding when simple measures are not enough.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Persistent digestive symptoms? Get evaluated in Turkey
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.