Blood Test for Prostate Cancer: PSA Ranges Explained
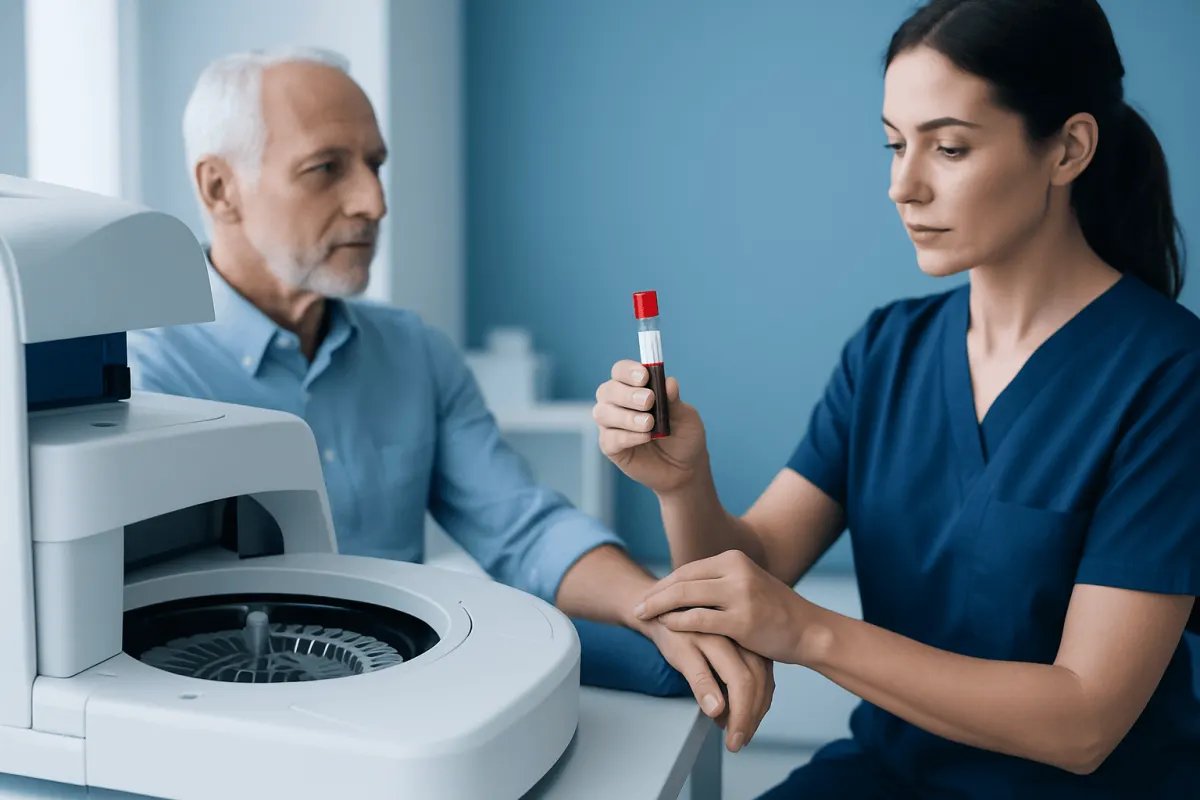
The main blood test for prostate cancer is the prostate-specific antigen (PSA) test. PSA levels may rise with prostate cancer, but they also change with age, prostate size, infection, inflammation and recent activities, so one result must be interpreted in clinical context.
Blood test for prostate cancer: the key number first
The standard blood test for prostate cancer is the prostate-specific antigen, or PSA, test. PSA is a protein made by prostate cells. A PSA result below 4 nanograms per millilitre (ng/mL) has historically been described as within a common reference range, but this is not a firm boundary between health and cancer. Some people with a PSA below 4 ng/mL have prostate cancer, while many people with a higher result do not.
PSA is best understood as a risk marker rather than a cancer diagnosis. The meaning of a result depends on age, the size of the prostate, symptoms, family history, medicines, prior PSA results and findings from a rectal examination or imaging. Clinicians commonly look at whether the PSA is unexpectedly high for the individual, whether it rises over time, and whether there are other signs that need investigation.
A raised PSA may lead to repeating the blood test after avoiding temporary influences, assessing for infection or inflammation, and discussing further tests. These can include a digital rectal examination, urine testing, prostate MRI and, in selected situations, a biopsy. Prostate cancer is often slow growing, but accurate assessment helps identify people who may benefit from closer monitoring or treatment.
PSA reference ranges change with age and context
PSA tends to increase gradually with age because the prostate often enlarges over time. Age-specific reference ranges are sometimes used as a guide, although laboratories and clinical guidelines may differ. A commonly used approximate framework is up to 2.5 ng/mL for ages 40 to 49, up to 3.5 ng/mL for ages 50 to 59, up to 4.5 ng/mL for ages 60 to 69, and up to 6.5 ng/mL for ages 70 to 79. These figures are not diagnostic cut-offs and should not replace an individual medical assessment.
PSA is primarily used in people who have a prostate. It is not generally used as a screening marker in people without a prostate, although very low PSA levels can occasionally be measured in other contexts. A person’s sex assigned at birth, gender identity and surgical history should be considered respectfully and individually when deciding whether PSA testing is relevant.
Several non-cancerous factors can temporarily or persistently raise PSA. Benign prostatic enlargement, inflammation of the prostate, urinary tract infection, urinary retention, catheter use and recent prostate procedures are important examples. Ejaculation and vigorous cycling may also have a short-term effect in some people. Clinicians may advise postponing testing during an active urinary infection and may recommend avoiding ejaculation and strenuous cycling for a short period before a repeat test.
- 5-alpha-reductase inhibitor medicines used for enlarged prostate or hair loss can lower PSA readings and require adjusted interpretation.
- Recent biopsy, cystoscopy or catheterisation can increase PSA temporarily.
- PSA results should ideally be compared using the same laboratory method when possible.
What is an average PSA score for a 70 year old?

There is no single “average” PSA score that applies to every 70-year-old, because prostate size, health conditions and previous results vary considerably. In age-specific reference frameworks, a PSA up to about 6.5 ng/mL may be considered within an expected range for people aged 70 to 79. However, a result below this level does not completely exclude cancer, and a result above it does not establish cancer.
For a 70-year-old, the most useful question is often how the result compares with previous PSA values and the person’s overall risk. A PSA that has risen substantially from an established baseline, an abnormal rectal examination, a strong family history or a known inherited cancer-risk variant may justify further evaluation even when the number is within an age-adjusted range.
Health, life expectancy, personal priorities and potential benefits and harms of testing also matter. Shared decision-making with a doctor can help determine whether PSA screening or further assessment is appropriate. This is particularly important for older adults, for whom an abnormal test may not always require immediate invasive testing or treatment.
What levels in blood indicate prostate cancer?
No PSA level in the blood can by itself indicate with certainty that a person has prostate cancer. Risk generally becomes more likely as PSA rises, but there is overlap between cancer and non-cancer conditions. PSA values between about 4 and 10 ng/mL are often called a borderline range and may prompt repeat testing or additional risk assessment. Values above 10 ng/mL are more concerning, but can still occur with benign enlargement or significant inflammation.
A clinician may use additional PSA-based measures to refine risk. These include the percentage of free PSA, PSA density, which compares PSA with prostate volume, and the pattern of PSA change over time. These measures are not stand-alone diagnostic tools; they are interpreted alongside age, examination findings, MRI results and individual risk factors.
Multiparametric MRI can help identify areas of the prostate that may need targeted sampling and may help some people avoid unnecessary biopsy. If a biopsy is recommended, it is the test that can confirm whether cancer cells are present and, if so, describe their grade. Cancer Treatment: Options for Every Stage" class="ahp-ilk">Prostate cancer treatment decisions are based on confirmed diagnosis, cancer characteristics, symptoms and personal health, not on PSA alone.
What are the first hints that your body is fighting prostate cancer?
There are usually no early body signals showing that the immune system is “fighting” prostate cancer. Early prostate cancer often causes no symptoms at all, which is why PSA testing and risk-based discussions may be considered for some people. A normal PSA does not guarantee that cancer is absent, and symptoms alone cannot confirm it.
When symptoms occur, they are more often caused by benign prostatic enlargement or another urinary condition than by cancer. These symptoms can include a weak urine stream, difficulty starting urination, needing to urinate frequently, waking at night to pass urine, urgency, or a feeling that the bladder has not emptied fully. Pain or burning during urination can suggest infection and should be assessed.
Blood in the urine or semen, persistent pelvic discomfort, unexplained weight loss, persistent bone pain or new weakness require prompt medical attention, although these signs have many possible causes and do not automatically mean cancer. Medical evaluation aims to identify the cause rather than assume the worst. Benign prostatic hyperplasia is a common non-cancerous explanation for urinary symptoms in people with a prostate.
What is the strongest predictor of prostate cancer?
Age is the strongest overall predictor of prostate cancer: the condition is more common as people get older. Family history is also highly important. Having a father, brother or son with prostate cancer, especially when it was diagnosed at a younger age or affected more than one close relative, increases risk. Certain inherited genetic changes, including BRCA-related variants and other DNA-repair gene variants, can also raise risk.
For an individual who is being assessed, an abnormal prostate biopsy is the only way to confirm cancer. Before biopsy, a combination of PSA level and trend, prostate MRI findings, digital rectal examination, family history, ancestry and genetic risk factors gives a more informative estimate than any single measurement. Black men and people of African ancestry may have a higher risk of developing and dying from prostate cancer in some populations, so clinicians may discuss earlier or more individualised assessment.
Maintaining a healthy weight, staying physically active and not smoking support general health, but they cannot eliminate prostate cancer risk. People with a strong family history may benefit from discussing earlier PSA testing and, where appropriate, genetic counselling with a qualified clinician.
When to seek medical care
A person should arrange a medical appointment if they have a raised PSA result, a PSA that is increasing over repeated tests, persistent urinary symptoms, blood in the urine, blood in semen, or ongoing pelvic pain. A doctor can review possible temporary causes of PSA elevation and decide whether a repeat test, examination, urine test, MRI or referral is appropriate.
Urgent assessment is needed for inability to pass urine, fever or chills with urinary symptoms, severe pain, or visible blood in the urine with clots. These symptoms may relate to infection, urinary obstruction or another condition needing timely care; they should not be self-managed as a presumed PSA issue.
Screening discussions are most useful before a test is done. A clinician can explain possible benefits, false-positive results, overdiagnosis and follow-up choices in light of the person’s age and risk profile. Acıbadem Health Point’s multidisciplinary specialists in JCI-accredited hospitals assess prostate concerns and support international patients through diagnostic and treatment planning.
Frequently asked questions
01Can a PSA blood test diagnose prostate cancer?
No. PSA is a marker of prostate activity, not a definitive cancer test. An elevated result may be caused by benign prostate enlargement, infection, inflammation or recent procedures, so further assessment may be needed.
02Is a PSA level of 4 ng/mL high?
A PSA of 4 ng/mL has traditionally been used as a general reference point, but it is not a universal threshold. Its meaning depends on age, previous PSA values, prostate size, medicines and other clinical findings.
03Should PSA be repeated if it is high?
Often, yes. A clinician may repeat PSA testing after treating or excluding infection and allowing time after activities or procedures that can affect the result. Repeating the test can help determine whether the elevation is temporary or persistent.
04Can prostatitis raise PSA?
Yes. Prostatitis, meaning inflammation or infection of the prostate, can raise PSA and sometimes raise it substantially. A doctor should assess urinary or pelvic symptoms and advise when repeat testing is most appropriate.
05Does an enlarged prostate raise PSA?
Yes. Benign prostatic enlargement can increase PSA because there is more prostate tissue producing the protein. This common condition is not cancer, but a raised PSA still needs appropriate medical interpretation.
06What should someone avoid before a PSA test?
A clinician may advise avoiding ejaculation and vigorous cycling for a short time before testing because they may affect PSA in some people. It is also important to tell the clinician about urinary symptoms, infections, recent procedures and all medicines, especially drugs that affect prostate size.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Oncology care in Turkey — second opinion and treatment plan
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.