Angioplasty vs Stent: What Is the Difference?
Angioplasty and stent placement are closely related treatments for narrowed coronary arteries, but they are not the same thing. Angioplasty uses a small balloon to widen the artery; a stent is a tiny mesh scaffold that may be placed afterward to help the artery remain open.
Angioplasty vs stent: a side-by-side comparison
In an angioplasty versus a stent comparison, angioplasty describes the technique used to widen a narrowed blood vessel, while a stent is a device that can be left inside the vessel afterward. Both are commonly used during catheter-based treatment of coronary artery disease, which is narrowing of the blood vessels that supply the heart muscle.
| Feature | Angioplasty | Stent |
|---|---|---|
| What it is | A procedure in which a small balloon is inflated inside a narrowed artery. | A small expandable mesh tube that supports the artery from within. |
| Main purpose | To compress plaque and improve the channel for blood flow. | To help keep the treated artery open after it has been widened. |
| How it is used | Usually performed through a catheter inserted via an artery in the wrist or groin. | Usually delivered on the angioplasty balloon and expanded at the narrowed area. |
| Left in the body? | No. The balloon and catheter are removed after treatment. | Yes. The stent remains permanently in the artery. |
| Common modern approach | Often serves as part of a procedure that includes a stent. | Drug-eluting stents are commonly used to reduce the chance of repeat narrowing. |
The phrase “angioplasty vs stent placement” can therefore be misleading because they are frequently parts of the same treatment session. A cardiologist may perform balloon angioplasty first and then deploy a stent if the artery needs continuing support. In some carefully selected cases, balloon angioplasty alone is used.
How clinicians tell angioplasty and stenting apart
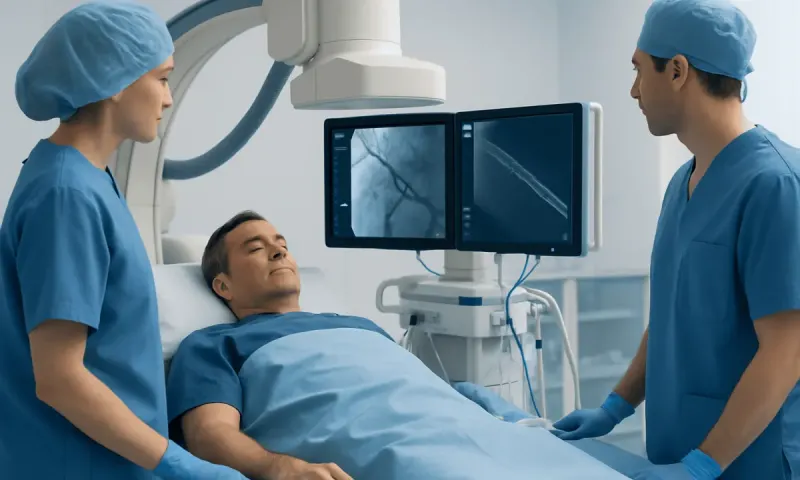
Coronary angioplasty, often called percutaneous coronary intervention (PCI), begins with a thin flexible tube called a catheter. Under X-ray guidance, the cardiologist advances it to the coronary arteries. Contrast dye helps show narrowed areas, and a balloon catheter may then be inflated briefly to widen the vessel.
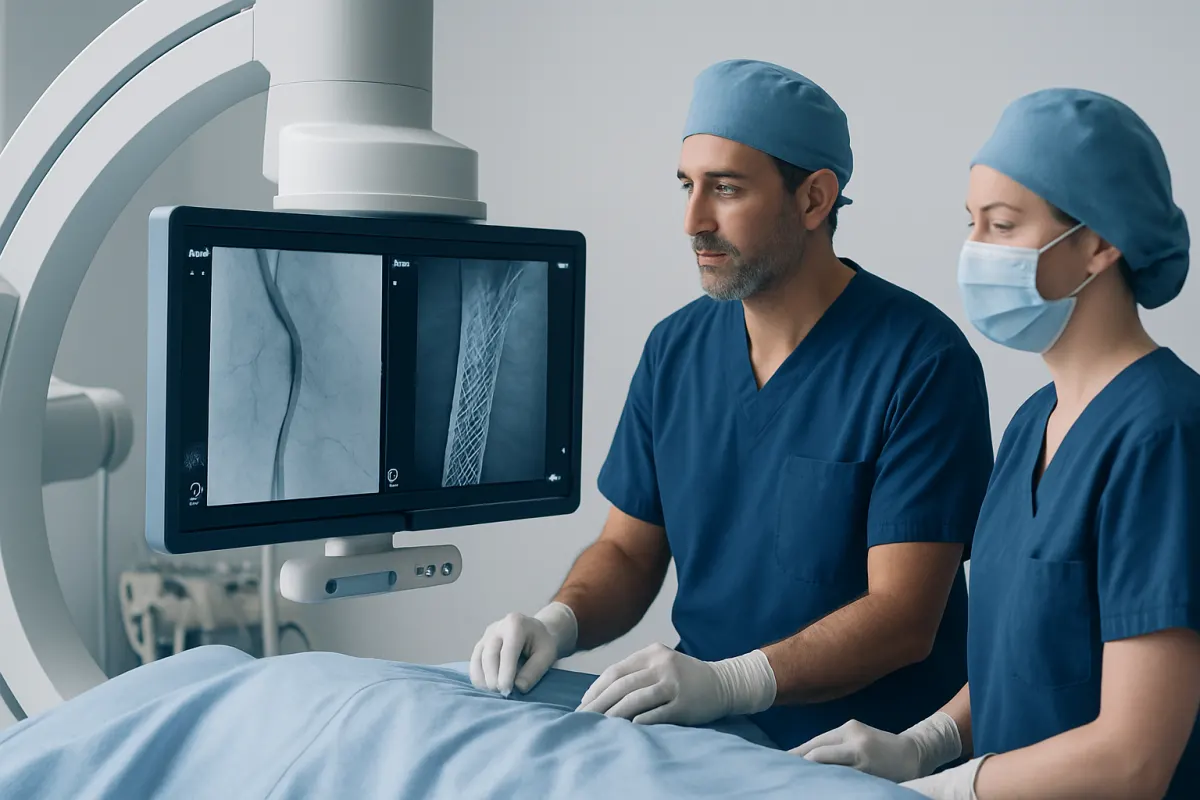
Stenting is an additional step, not a separate open operation. A collapsed stent is mounted on a balloon catheter and positioned at the narrowed segment. As the balloon expands, the stent opens and presses against the artery wall. The balloon is deflated and removed, but the stent stays in place to support the vessel.
Most coronary stents used today release medication gradually. These drug-eluting stents help limit tissue growth that could otherwise narrow the treated segment again. People who receive a stent usually need antiplatelet medicines for a period determined by their cardiology team, because stopping these medicines without medical advice can increase the risk of a clot forming in the stent.
Both approaches treat obstructive coronary artery disease, but neither removes the underlying tendency to form plaque. Long-term heart health also depends on controlling blood pressure, cholesterol and diabetes when present, avoiding tobacco, being physically active as advised, and following an appropriate eating pattern.
How to determine if angioplasty is needed

Angioplasty is considered when a narrowed coronary artery is likely to be causing reduced blood flow to the heart muscle, symptoms, or an acute heart problem. Typical symptoms include pressure, tightness, heaviness, burning, or pain in the chest that may spread to the arm, shoulder, jaw, neck, back, or upper abdomen. Some people, especially older adults and people with diabetes, may instead notice breathlessness, unusual fatigue, nausea, or reduced exercise tolerance.
A clinician considers the full clinical picture rather than an angiogram image alone. Assessment may include a medical history, physical examination, electrocardiogram, blood tests, echocardiogram, exercise or other stress testing, coronary CT angiography, and invasive coronary angiography. In selected cases, tests performed during angiography can measure whether a narrowing is actually limiting blood flow.
In stable coronary artery disease, medication and lifestyle measures are often tried first when symptoms are manageable and there is no high-risk anatomy. Angioplasty may be recommended if symptoms continue despite appropriate treatment, if testing indicates important reduced blood flow, or if anatomy suggests a higher risk. During a heart attack caused by a blocked coronary artery, urgent angioplasty with stenting is often used to restore blood flow quickly.
A cardiologist should explain the expected benefit in the individual situation. For many people with stable symptoms, PCI is especially helpful for relieving angina; it is not automatically the best choice for every narrowing seen on a scan.
Does 70% blockage require a stent?
No. A 70% blockage does not automatically require a stent. The percentage seen on angiography is important, but it is only one part of the decision. Its meaning can vary according to the artery involved, the length and appearance of the narrowing, whether it supplies a large area of heart muscle, and whether symptoms or tests show that blood flow is significantly restricted.
For an intermediate or uncertain narrowing, a cardiologist may use physiologic measurements during angiography, such as fractional flow reserve or an equivalent assessment, to determine whether the lesion is affecting blood flow enough to benefit from intervention. Stress test findings, recurrent angina despite medication, and high-risk features can also influence the recommendation.
Some people with a 70% narrowing can be managed with medicines and risk-factor treatment, while others may benefit from PCI. A sudden blockage causing a heart attack is assessed differently from stable disease found during an outpatient evaluation. The best approach is individualized and should be discussed with a cardiologist who can review the images and overall medical context.
Can angioplasty be done without putting a stent?
Yes. Angioplasty can be done without putting in a stent, though this is less common for many coronary artery narrowings today. Balloon-only angioplasty may be considered when placing a permanent implant is unsuitable, when the vessel is very small, when anatomy makes a stent difficult to use, or in certain types of restenosis, meaning a narrowing that has developed within a previously placed stent.
Specialized balloon technologies, including drug-coated balloons in selected circumstances, may also be considered by interventional cardiologists. However, balloon angioplasty alone has a greater chance of the artery narrowing again in some situations because there is no scaffold remaining to support the vessel wall.
If a stent is placed, the patient needs to take prescribed antiplatelet medication reliably. This requirement matters when planning treatment for someone with a high bleeding risk, an upcoming surgery, medication intolerance, or difficulty taking medicines consistently. The care team weighs these issues against the expected benefit of stenting.
Angioplasty versus a stent is therefore not usually an either-or decision made in isolation. It is a decision about the safest and most effective way to restore blood flow for the specific artery, clinical situation, and person.
How to decide stent vs bypass?
Stenting and coronary artery bypass grafting (CABG) both improve blood supply to the heart, but they do so differently. A stent treats a narrowing from inside the artery through a catheter. Bypass surgery uses blood vessels from elsewhere in the body to create new routes around blocked coronary arteries.
Stenting may be suitable for a limited number of accessible narrowings, particularly when rapid recovery and a less invasive procedure are priorities. Bypass surgery may be favored for complex disease affecting several major coronary arteries, certain blockages in the left main coronary artery, diffuse disease, or disease in people with diabetes. Heart pumping function, kidney health, age, other medical conditions, and the likelihood of durable results all matter.
When the choice is not straightforward, a multidisciplinary heart team may review angiography findings and discuss options with the patient. The conversation should include likely symptom relief, recovery needs, potential complications, the possibility of future procedures, and personal preferences. Information on coronary artery bypass surgery can help patients understand how this alternative differs from catheter-based treatment.
Angioplasty vs stent recovery is generally shorter than recovery after bypass surgery because PCI does not require opening the chest. However, a shorter recovery alone should not determine the choice; the anatomy and long-term treatment strategy remain central.
Treatment, recovery and everyday care
During an angioplasty vs stent procedure, patients are commonly awake but receive local anesthetic at the catheter entry site and medicine to help them relax if needed. The procedure may take less than an hour or longer, depending on the number and complexity of treated vessels. Afterward, monitoring helps detect bleeding at the access site, changes in heart rhythm, chest symptoms, or other concerns.
Recovery after an uncomplicated planned PCI is often relatively quick, although timing varies. The clinician gives individualized instructions about wound care, driving, work, lifting, exercise, bathing, and resuming sexual activity. Mild tenderness or bruising near the wrist or groin can occur, but growing swelling, ongoing bleeding, marked pain, numbness, or a cool limb should be reported urgently.
After stent placement, antiplatelet therapy is a key part of treatment. Patients should not stop aspirin, a second antiplatelet medicine, or any other heart medicine unless the prescribing clinician specifically advises it. Cardiac rehabilitation, when available and appropriate, offers supervised activity, education, and support for long-term risk reduction.
Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals diagnose and treat coronary artery disease for international patients, with treatment planning based on individual clinical assessment.
When to seek medical care
Anyone with new, recurrent, or worsening chest discomfort should seek prompt medical assessment, especially if it happens during activity or emotional stress and improves with rest. A medical review is also important for unexplained shortness of breath, reduced ability to exercise, palpitations, or fatigue that is new or progressing, particularly in people with cardiovascular risk factors.
Emergency care is needed for chest pressure, pain, heaviness, or tightness lasting more than a few minutes, or symptoms that return repeatedly. Urgent warning signs include pain spreading to the arm, jaw, back, or upper abdomen; breathlessness; cold sweating; nausea; fainting; or sudden severe weakness. People should contact local emergency services rather than drive themselves.
After angioplasty or stent placement, emergency assessment is needed for renewed chest pain, severe breathlessness, fainting, uncontrolled bleeding from the catheter site, or signs of an allergic or medication reaction. Regular follow-up helps the cardiology team review symptoms, medicines, blood pressure, cholesterol, and progress with prevention measures.
Frequently asked questions
01Is angioplasty the same as a stent?
No. Angioplasty is the procedure that uses a balloon to widen a narrowed artery. A stent is a small mesh tube that may be placed during angioplasty to help the artery stay open.
02Which is better, angioplasty or a stent?
They are usually not competing treatments because a stent is often used as part of angioplasty. The better approach depends on the artery anatomy, the reason for treatment, bleeding risk, medication needs, and the person’s overall health.
03How long does it take to recover after angioplasty and stent placement?
Many people recover from an uncomplicated catheter procedure within days, but recovery varies with the access site, the reason for treatment, and other health conditions. A heart attack, complications, or physically demanding work can require a longer recovery plan from the care team.
04Can a stent become blocked again?
Yes. A treated artery can narrow again over time, and a clot can form in a stent, especially if prescribed antiplatelet medication is stopped too soon. Taking medicines as directed and addressing cholesterol, smoking, blood pressure, diabetes, diet, and activity can reduce risk.
05Is a stent permanent?
Yes. Most coronary stents are designed to remain in the artery permanently. The artery lining gradually grows over the stent, while medication released by many modern stents helps lower the chance of excessive tissue growth.
06What happens if a coronary blockage is not treated with a stent?
Not every coronary blockage needs a stent. Depending on symptoms and test results, treatment may include medicines, lifestyle changes, monitoring, or bypass surgery; however, a suspected heart attack or severe ongoing symptoms need urgent medical evaluation.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Heart care in Turkey — expert evaluation and treatment
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.