The Trachea Keeps Air Moving, and Its Problems Can Mimic Asthma

Ever wondered why a cough or wheeze sometimes doesn’t get better with the usual inhalers? Sometimes the problem isn’t in the lungs at all — it’s in the windpipe itself.
Your trachea, or windpipe, is the tube that connects your throat to your lungs and keeps air moving in and out with every breath. When it becomes irritated, narrowed, injured, or blocked, you may notice cough, wheezing, noisy breathing, or shortness of breath. These symptoms deserve a proper medical assessment.
Overview: what the trachea does
The trachea is the windpipe, a firm but flexible tube that carries air from the larynx (voice box) down toward the lungs. Its job sounds simple, but it matters: it keeps an open path for every breath you take. In adults, the trachea extends from the lower neck into the chest, where it divides into the right and left main bronchi, which then enter the lungs.
The tracheal wall contains C-shaped rings of cartilage that help prevent the airway from collapsing. Its inner lining is covered with a moist mucous membrane and tiny hair-like structures called cilia. Together, mucus and cilia help trap dust, germs, and other particles, then move them upward so they can be coughed out or swallowed.
The trachea sits close to the thyroid gland, esophagus, and major blood vessels, so problems in nearby structures can sometimes affect breathing too. Many people assume airway symptoms are “lung problems,” but the trachea itself can be the source of a cough, wheeze, or noisy breathing. That’s why some breathing symptoms need a closer look beyond routine treatment for asthma or infection.
How the trachea is built and why that matters
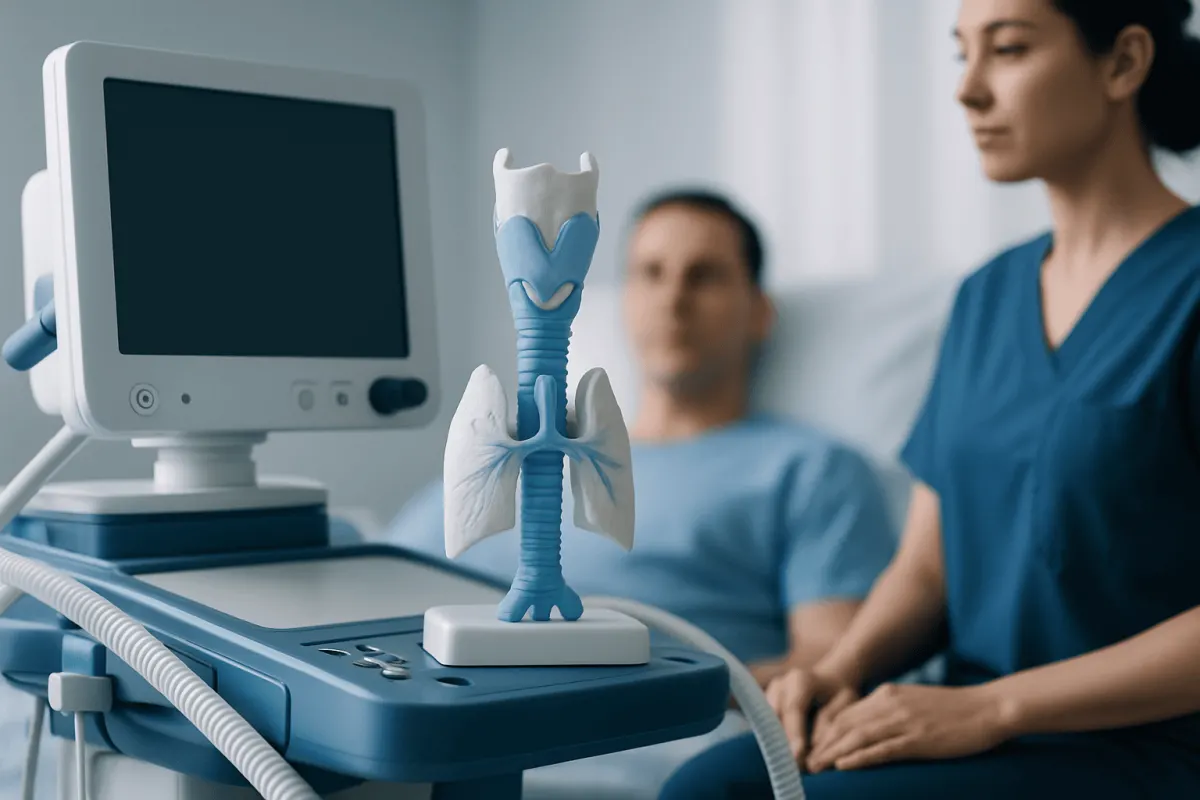
Your trachea is built to be both stable and adaptable. The cartilage rings are open at the back, where a band of muscle and connective tissue gives it some flexibility. This structure helps the airway stay open while also allowing the esophagus, which sits just behind it, to expand when swallowing food.
The inner lining of the trachea is part of the body’s natural defense system. When a person inhales irritants such as smoke, dust, or chemical fumes, the trachea responds by increasing mucus production and triggering cough. This is protective in the short term, but repeated irritation can lead to inflammation and ongoing symptoms.
The trachea also matters during illness and medical care. Swelling, infection, injury from intubation, or scar tissue can narrow the airway. Even a small amount of narrowing may cause symptoms because airflow through the trachea needs enough space to move freely. That’s why a tracheal problem can feel serious even when the changes on imaging look small.
Symptoms of trachea problems
Tracheal symptoms can vary depending on whether the problem is sudden or gradual, and whether it affects the lining, the shape of the airway, or the space inside it. Some symptoms overlap with asthma, bronchitis, or other lung conditions, which is one reason tracheal disorders may be overlooked at first.
Common symptoms include persistent cough, noisy breathing, wheezing, shortness of breath, throat discomfort, chest tightness, hoarseness, or a feeling that breathing is restricted. Some people notice symptoms mainly during exercise, while others have trouble even at rest. A harsh sound when breathing in, called stridor, can suggest narrowing in the upper airway, including the trachea.
Warning signs that deserve prompt medical assessment include coughing up blood, sudden trouble breathing, choking, bluish lips, or severe noisy breathing. Symptoms that do not improve with standard treatment for asthma or chest infection may also point to a tracheal cause.
- Persistent or unexplained cough
- Wheezing or whistling sounds during breathing
- Stridor or noisy breathing
- Shortness of breath, especially with exertion
- Hoarseness or voice changes
- Recurrent chest infections
Common tracheal conditions, causes, and risk factors
Several different conditions can affect the trachea. Short-term problems include irritation from infections, smoke exposure, allergic reactions, or inhaled foreign bodies. In children especially, an object stuck in the airway can quickly become an emergency. In adults, swelling after infection or trauma may temporarily narrow the airway.
Longer-term tracheal disorders include tracheal stenosis, which means narrowing of the windpipe, often due to scar tissue after prolonged intubation or tracheostomy. The trachea can also weaken and collapse more than usual during breathing, a condition called tracheomalacia. Other causes of airway blockage include benign growths, inflammatory disease, compression from nearby masses, or cancers involving the airway. Where relevant, doctors may also assess related respiratory conditions such as lung cancer if imaging suggests a mass affecting the airway.
Risk factors depend on the condition but may include smoking, previous airway surgery, prolonged use of a breathing tube, prior radiation treatment, autoimmune or inflammatory disease, severe infections, inhalation injury, and gastroesophageal reflux that may worsen irritation in some patients. A history of repeated unexplained “bronchitis” or poor response to inhalers can sometimes provide an important clue that the central airway should be examined more closely.
How doctors diagnose trachea disorders
Diagnosis usually begins with a medical history and physical examination. A doctor will ask when symptoms started, whether they are constant or intermittent, and whether there are triggers such as exercise, lying flat, infection, or environmental exposure. Listening to the chest and neck can help distinguish lower-lung wheeze from upper-airway noise.
Imaging and airway visualization are often important. A chest X-ray may offer initial clues, but a CT scan usually provides better detail about the width, shape, and surrounding structures of the trachea. In some cases, doctors may request bronchoscopy to look directly inside the airway, identify narrowing or blockage, and sometimes collect samples or provide treatment during the same procedure.
Breathing tests may also be used, especially if symptoms have been mistaken for asthma. Depending on the case, evaluation can involve ENT specialists, pulmonologists, thoracic surgeons, radiologists, and anesthesiologists. This team approach is particularly helpful when symptoms are complex or when a structural airway problem is suspected.
Treatment options for trachea conditions
Treatment depends entirely on the cause. Mild inflammation or infection may improve with supportive care and medicines prescribed by a doctor, such as treatments for infection, airway inflammation, or acid reflux when appropriate. Stepping away from irritants like tobacco smoke matters too — ongoing exposure can worsen swelling and mucus production.
When the airway is narrowed or blocked, treatment may involve procedures rather than medicine alone. Bronchoscopy can sometimes be used to remove mucus plugs, foreign bodies, or certain growths, and to assess stenosis in detail. Some patients may need airway dilation, laser or other endoscopic techniques, stent placement, or surgery to restore a stable airway. If a nearby condition is contributing to symptoms, treatment may address that condition as well, such as lung cancer treatment when a tumor is affecting the airway.
In selected cases of significant structural narrowing, surgeons may recommend trachea surgery to remove a damaged segment or reconstruct the airway. If tracheal disease is related to a mass or another chest condition, broader evaluation by thoracic surgery specialists may be needed. Near the end of the care pathway, centers such as Acıbadem Health Point can provide multidisciplinary assessment and treatment for international patients through JCI-accredited hospitals when advanced airway evaluation is required.
Prevention and self-care
Not every tracheal disorder can be prevented, but some steps can reduce risk and support airway health. Avoiding smoking and secondhand smoke is one of the most important measures. Using workplace respiratory protection when exposed to dust, chemicals, or fumes can also help reduce irritation and injury.
Prompt treatment of respiratory infections, good control of chronic conditions, and follow-up after intubation or airway surgery may lower the risk of complications such as scarring or ongoing inflammation. People with reflux symptoms should discuss management with a doctor, since repeated throat and airway irritation may contribute to discomfort in some cases.
One honest word of caution: self-care is no substitute for a medical assessment when breathing symptoms won’t go away. Drinking enough fluids, avoiding known irritants, and taking prescribed medicines correctly can help day to day — but if you develop new wheezing, stridor, or unexplained shortness of breath, get it checked rather than assuming it’s a routine chest infection.
When to seek medical care
See a doctor if you have a cough that won’t go away, repeated chest infections, unexplained wheezing, hoarseness, or shortness of breath that’s new or getting worse. If symptoms persist despite routine inhalers or antibiotics — especially if they keep coming back — they deserve further evaluation.
Urgent care is needed for sudden breathing difficulty, choking, severe noisy breathing, bluish lips, confusion, or coughing up blood. These symptoms can signal a blocked or significantly narrowed airway and should not be managed at home.
For non-emergency concerns, a doctor may refer the patient to an ENT specialist, pulmonologist, or thoracic surgeon depending on the suspected cause. Early assessment often makes it easier to identify whether the problem is simple irritation, a treatable narrowing, or a related condition elsewhere in the chest.
Frequently asked questions
01What is the trachea and what does it do?
The trachea is the windpipe, the tube that carries air between the throat and the lungs. It helps keep the airway open and also helps filter, moisten, and clear inhaled particles through mucus and cilia.
02Is the trachea the same as the throat?
No. The throat usually refers to the pharynx and nearby structures, while the trachea is the airway tube below the voice box that leads toward the lungs. They are connected but have different roles in breathing and swallowing.
03What symptoms can suggest a trachea problem?
Possible symptoms include persistent cough, wheezing, noisy breathing, stridor, hoarseness, and shortness of breath. These symptoms can overlap with asthma or bronchitis, so medical evaluation may be needed if they persist or do not respond to usual treatment.
04Can the trachea become narrowed?
Yes. The trachea can narrow because of scar tissue, inflammation, injury, tumors, or external pressure from nearby structures. This is called tracheal stenosis when the airway becomes abnormally tight.
05How are tracheal disorders diagnosed?
Doctors often combine a medical history, examination, imaging such as CT, and sometimes bronchoscopy to look directly inside the airway. Breathing tests may also help, particularly when symptoms resemble asthma.
06Are trachea conditions treatable?
Many tracheal conditions are treatable, but the treatment depends on the cause. Care may include medicines, removal of irritants, bronchoscopy-based procedures, or surgery for significant narrowing or structural problems.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Hair transplant in Turkey — costs, graft counts & a free assessment
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.