

Restrictive Lung Disease: Early Signs, Risk Factors, and How It Is Treated
Have you noticed that the walk to your car, or one flight of stairs, leaves you needing to stop and catch your breath? Or that you cannot quite pull in a full, satisfying breath, no matter how hard you try?
That feeling can come from a group of conditions we call restrictive lung disease. In these conditions the lungs cannot expand fully, so taking a deep breath becomes hard work. Getting checked early helps us find the cause and choose the right treatment, which may include medicines, pulmonary rehabilitation, oxygen therapy, or care for an underlying condition.
What restrictive lung disease means
This is not one single illness. It is a pattern of breathing difficulty: the lungs cannot open up fully, so less air comes in with each breath. This can cause shortness of breath, especially during activity, and may gradually affect everyday tasks such as walking, climbing stairs, or speaking for long periods.
Doctors usually divide restrictive lung disease into two broad groups. In one group, the problem is inside the lungs themselves, often due to inflammation or scarring of lung tissue. In the other, the lungs may be healthy but cannot expand normally because of issues affecting the chest wall, breathing muscles, nerves, or body habitus.
Why does this split matter? Because we treat the cause, not just the breathing pattern. Some causes can be managed mainly with medicines, while others require pulmonary rehabilitation, oxygen support, or treatment for another condition affecting the lungs or muscles.
Restrictive lung disease is different from obstructive lung diseases such as asthma or chronic obstructive pulmonary disease, where the main problem is difficulty pushing air out of narrowed airways. In restrictive disease, the main issue is reduced lung volume. Some people can have features of both patterns at the same time, which is why proper testing is important.
Early signs and symptoms
The most common early sign of restrictive lung disease is shortness of breath during physical activity. At first, a person may notice that tasks once considered easy now feel more tiring, such as walking uphill, carrying groceries, or hurrying to catch transportation. As the condition progresses, breathlessness may occur with lighter activity or even at rest.
A dry cough is another common symptom, especially in conditions that involve inflammation or scarring of lung tissue. Some people also report chest tightness, a feeling that they cannot take a satisfying deep breath, reduced stamina, or unexplained fatigue. Because all of this creeps up slowly, people often blame it on getting older, being out of shape, or stress.
Other symptoms depend on the cause. A person with an autoimmune disorder may also have joint pain, skin changes, or muscle weakness. Someone with a neuromuscular condition may notice trouble with posture, swallowing, or weakness in the arms and legs. Swelling of the legs, sleep-related breathing problems, or weight changes may suggest a broader medical issue contributing to restricted breathing.
- Shortness of breath, especially with exertion
- Dry, persistent cough
- Reduced exercise tolerance
- Fatigue or low energy
- Difficulty taking a full deep breath
- In advanced cases, low oxygen levels or bluish lips and fingertips
Causes and risk factors

There are many possible reasons behind it. Intrinsic causes affect the lung tissue itself. These include interstitial lung diseases, which involve inflammation or scarring in the lungs. Examples include idiopathic pulmonary fibrosis, lung involvement related to autoimmune diseases, hypersensitivity reactions to inhaled particles, and certain occupational lung conditions. Patients who want to learn more about lung scarring may also read about interstitial lung disease.
Extrinsic causes are outside the lungs but limit lung expansion. These include severe obesity, significant spinal curvature, chest wall deformities, and conditions that weaken the breathing muscles. Neuromuscular disorders can interfere with the diaphragm and other muscles needed for normal breathing. Pleural diseases, which affect the lining around the lungs, may also reduce lung expansion.
Risk factors vary by cause. They may include exposure to dusts, molds, chemicals, or asbestos; a history of radiation therapy to the chest; use of certain medications known to affect the lungs; smoking history; connective tissue diseases such as rheumatoid arthritis or systemic sclerosis; and family history of some fibrotic lung disorders. Repeated exposure in the workplace or home can be especially relevant.
Not everyone with a risk factor develops restrictive lung disease, and some people have no obvious trigger. For this reason, diagnosis often involves careful review of symptoms, work history, environmental exposures, medications, and other medical conditions. Finding the underlying cause helps guide treatment and gives a clearer sense of what to expect over time.
How doctors diagnose restrictive lung disease
Diagnosis usually starts with a medical history and physical examination. The doctor asks when symptoms began, how quickly they changed, and whether there are possible triggers such as workplace exposures, birds or mold at home, autoimmune symptoms, medications, or family history. During the exam, the clinician checks breathing effort, oxygen levels, lung sounds, and signs of related illness elsewhere in the body.
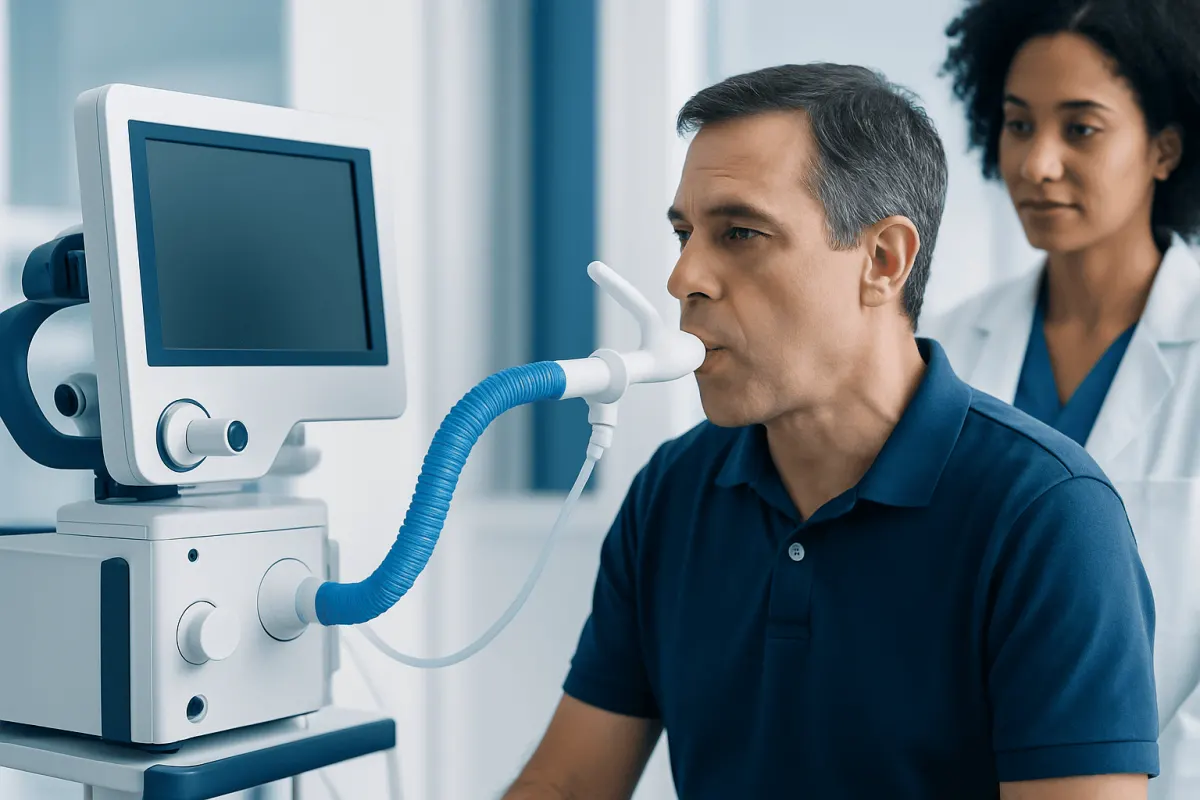
The most important test is usually pulmonary function testing. These breathing tests measure lung volumes and how well air moves in and out. In restrictive lung disease, total lung capacity is reduced. Doctors may also measure how efficiently oxygen passes from the lungs into the blood. These results help confirm restriction and estimate its severity.
Imaging is often needed to look for the cause. A chest X-ray may show broad changes, but a high-resolution CT scan gives more detail about inflammation, scarring, pleural disease, or other structural problems. In selected cases, blood tests can look for autoimmune disease, and exercise testing may assess oxygen levels during activity. Some patients are referred for bronchoscopy or, less commonly, lung biopsy if the diagnosis remains unclear.
Because restrictive lung disease can overlap with other respiratory conditions, diagnosis is often made by a pulmonologist working with radiologists, rheumatologists, or neurologists when needed. Advanced lung testing and diagnostic imaging can help clarify whether the problem lies in the lung tissue, pleura, chest wall, or breathing muscles.
Treatment options and what they aim to do
Treatment for restrictive lung disease depends on its cause, severity, and how quickly it is progressing. The main goals are to reduce symptoms, preserve lung function, improve daily activity, and treat the underlying condition whenever possible. Some people need only monitoring and symptom support, while others benefit from long-term specialist care.
When inflammation is part of the process, doctors may use medicines such as corticosteroids or other immune-modifying treatments. In some fibrotic lung diseases, antifibrotic therapy may be considered to slow worsening. If the restriction is related to an autoimmune disease, treatment often focuses on controlling that condition. If obesity, chest wall issues, or neuromuscular disease is involved, care may include weight management, breathing support, physical therapy, or treatment directed at the primary disorder.
Supportive care is also important. Pulmonary rehabilitation can help improve exercise tolerance, breathing efficiency, and confidence with activity. Oxygen therapy may be recommended if blood oxygen levels are low, especially during exercise or sleep. For selected patients with severe, progressive disease, more advanced options may be discussed, including pulmonary rehabilitation and specialist evaluation for lung transplant.
Regular follow-up helps doctors monitor symptoms, breathing tests, oxygen levels, and treatment response. In complex cases, a multidisciplinary team can be helpful. Acıbadem Health Point’s multidisciplinary specialists in JCI-accredited hospitals diagnose and treat restrictive lung disease for international patients, particularly when advanced imaging, pulmonary testing, or coordinated specialty care is needed.
Living with restrictive lung disease: self-care and prevention
What you do at home will not replace treatment, but it can genuinely change how you feel day to day. People with restrictive lung disease often benefit from pacing activities, taking planned rest breaks, and using breathing strategies taught by respiratory specialists. Staying as physically active as possible within safe limits can help maintain strength and endurance.
Avoiding irritants is another key step. Tobacco smoke, workplace dust, chemical fumes, and indoor mold can worsen respiratory symptoms or contribute to ongoing lung injury in some conditions. Vaccinations may be recommended to reduce the risk of respiratory infections, which can place additional strain on the lungs. Good nutrition, hydration, and adequate sleep also support overall respiratory health.
Some preventive steps depend on the cause. For example, people with occupational exposures may need workplace assessment and protective equipment. Those with autoimmune disease should keep regular follow-up with their specialist. Individuals with obesity-related restriction may be advised on structured weight management, as reducing mechanical pressure on the chest and abdomen can improve breathing.
If symptoms interfere with exercise, structured respiratory care may help. In appropriate cases, a doctor may suggest supervised programs or respiratory therapy to improve breathing mechanics and day-to-day function. Any new plan should be tailored to the person’s diagnosis, current lung function, and overall health.
When to seek medical care
Medical review is important if shortness of breath, dry cough, or unusual fatigue lasts more than a few weeks, keeps returning, or gradually worsens. A person should also seek care if breathing problems begin to limit routine activities, disturb sleep, or reduce exercise tolerance without a clear explanation. Even mild symptoms deserve attention when they persist.
Urgent medical care is needed for severe shortness of breath, chest pain, confusion, bluish lips or fingertips, or a sudden drop in oxygen levels if these are being monitored at home. These symptoms can signal a serious breathing problem and should not be ignored.
People who already have a lung condition should contact their doctor sooner if they develop fever, a clear increase in cough, more mucus than usual, swelling in the legs, or faster decline in stamina. Early treatment of infections, flare-ups, or oxygen-related problems may help prevent complications.
With so many possible causes behind it, this is not something to work out on your own; let a doctor examine you. Timely assessment can identify reversible factors, rule out other conditions, and provide a practical plan for treatment and follow-up.
Frequently asked questions
01Is restrictive lung disease the same as interstitial lung disease?
No. Restrictive lung disease is a breathing pattern in which the lungs cannot fully expand, while interstitial lung disease is one important group of conditions that can cause this pattern. Some people with restrictive lung disease have problems outside the lungs, such as chest wall, neuromuscular, or obesity-related causes.
02Can restrictive lung disease be cured?
Some causes are manageable and partly reversible, while others are chronic and require long-term treatment. The outcome depends on the specific diagnosis, how early it is found, and how well the underlying cause can be treated. A doctor can explain whether the goal is reversal, slowing progression, or symptom control.
03What is usually the first symptom of restrictive lung disease?
The earliest symptom is often shortness of breath with exertion. A person may notice reduced stamina or unusual fatigue before symptoms become obvious at rest. A dry cough can also appear early, especially in lung tissue disorders.
04How is restrictive lung disease confirmed?
Doctors usually confirm it with pulmonary function tests that show reduced lung volumes. Imaging, especially CT scanning, often helps identify the cause. Additional blood tests or specialist assessments may be needed depending on the clinical picture.
05Does oxygen therapy mean the disease is severe?
Not always. Oxygen therapy is prescribed when oxygen levels are too low, which can happen at rest, during exercise, or during sleep. Some people need it only in specific situations, while others require more continuous support.
06Can exercise help if breathing is limited?
Yes, when it is guided appropriately. Pulmonary rehabilitation and supervised activity programs can improve endurance, breathing efficiency, and confidence with movement. Exercise plans should be tailored to the person’s diagnosis and current respiratory status.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


