Photokeratitis: Diagnosis, Outlook, and Modern Treatment Approaches

You spent the day on the slopes, or out on the water, or a few minutes watching someone weld. Your eyes felt fine. Then, hours later, they start to burn as if they are full of sand.
That is photokeratitis: a temporary sunburn-like injury to the clear front surface of the eye, caused by ultraviolet (UV) light. It is often very uncomfortable but usually improves within one to three days with eye protection, supportive treatment, and medical evaluation when symptoms are severe or do not settle.
Overview: what photokeratitis is and what to expect
What happens is an acute ultraviolet light injury to the surface of the eye, especially the cornea and the surrounding conjunctiva. Put simply, your eye gets sunburned. It can happen after exposure to intense sunlight, tanning lamps, welding arcs, or bright UV sources reflected by snow, water, sand, or ice.
The condition often starts several hours after exposure rather than immediately. Many people notice that their eyes feel normal at first, then become painful later the same day or during the night. This delay can make it harder to connect the symptoms to a day spent skiing, boating, sunbathing, or working with UV-producing equipment.
The good news: in most uncomplicated cases, the surface cells of the eye repair themselves within 24 to 72 hours. Still, do not brush it off. Symptoms can be intense, and other problems such as a corneal abrasion, a foreign body, or infection can feel much the same. A clinician may recommend assessment by an eye specialist, especially if vision changes are marked or symptoms affect only one eye.
Symptoms and how they may feel
Photokeratitis commonly affects both eyes because UV exposure usually reaches both sides at the same time. Typical symptoms include burning or pain, tearing, redness, a gritty or sandy sensation, blurred vision, swollen eyelids, headache, and marked sensitivity to light. Some people also describe halos around lights or difficulty keeping the eyes open.
Symptoms often develop 6 to 12 hours after exposure. The delay happens because UV light damages the superficial cells of the cornea, and discomfort rises as those cells become inflamed and begin to shed. This pattern can help distinguish photokeratitis from some immediately painful eye injuries, although only an examination can confirm the cause.
How bad it gets varies a lot. A mild case may just feel like dry, irritated eyes, while heavier exposure can make ordinary indoor light hard to bear. Contact lens wearers may notice greater irritation, but lenses should not be worn again until a doctor says the surface has healed.
- Eye pain or burning
- Redness and tearing
- Light sensitivity
- Blurred or hazy vision
- Gritty, foreign-body sensation
- Eyelid swelling or spasm
Causes and risk factors

The cause of photokeratitis is exposure to ultraviolet radiation, mainly UV-B and sometimes UV-C, that reaches the eye without adequate protection. Common situations include time on snowy mountains, high-altitude hiking, boating, beach exposure, and work involving welding torches, mercury vapor lamps, or other industrial UV sources. Tanning beds can also contribute.
Reflective surfaces increase risk because they bounce UV light upward into the eyes. Snow is especially important, which is why the condition is often called snow blindness. Water, white sand, concrete, and ice can also intensify exposure. Cloud cover does not fully block UV radiation, so people may be exposed even on overcast days.
Risk rises when protective eyewear is missing, poorly fitted, or does not block 100% of UVA and UVB. People who remove eye protection for only a few minutes during welding or outdoor recreation can still develop symptoms. Other factors that may raise susceptibility include dry eyes, recent eye surface irritation, and prolonged contact lens wear. Doctors may also consider other causes of painful red eyes, such as corneal abrasion or conjunctivitis, because these may overlap in symptoms but need different management.
How photokeratitis is diagnosed
Diagnosis is based on the story of recent UV exposure, symptoms, and an eye examination. A doctor will ask where the person has been, whether eye protection was used, when symptoms started, and whether one or both eyes are affected. This timing matters because photokeratitis often has a delayed onset after exposure.
The examination usually includes checking vision, looking at the eyelids and eye surface, and assessing how the pupils react to light. Fluorescein dye may be placed on the eye to highlight tiny areas of surface injury. With blue light, the affected corneal surface may show scattered superficial damage rather than one deep scratch. This can help distinguish photokeratitis from a single corneal cut or embedded foreign material.
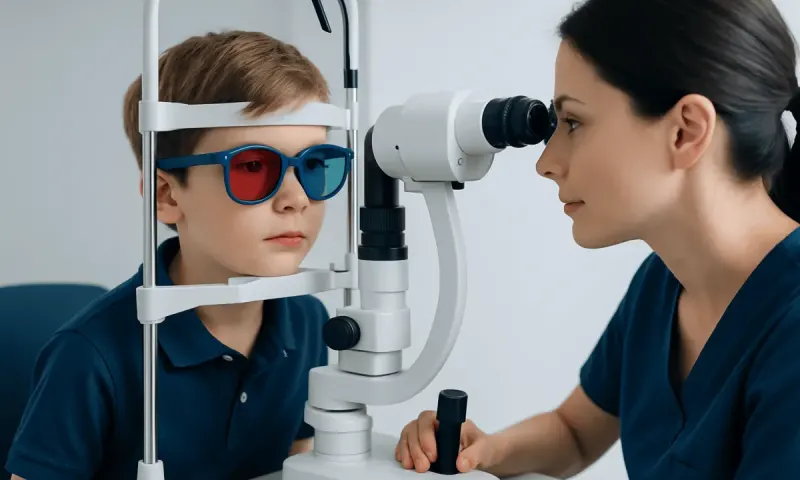
In some cases, a slit-lamp microscope is used for a more detailed view of the cornea. This is especially helpful if symptoms are severe, if only one eye is involved, if there was work-related exposure, or if there is concern about another problem such as infection. When vision changes, persistent pain, or uncertainty about the cause are present, an ophthalmology assessment may be recommended through ophthalmology care.
Modern treatment approaches and recovery
Treatment for photokeratitis is usually supportive while the eye surface heals. The first steps are to stop further UV exposure, rest the eyes, and avoid rubbing them. A clinician may recommend preservative-free lubricating drops or ointment to reduce discomfort and support the healing surface. Cool compresses and staying in dim light can also help.
Pain relief may be needed when symptoms are significant. Depending on the examination findings, a doctor may suggest oral pain relievers and, in selected cases, other short-term supportive medicines. Contact lenses should generally be avoided until the eye surface has recovered. If there is concern about a break in the surface or a higher risk of infection, prescription antibiotic drops or ointment may be used, but not everyone needs them.
Eye patching is not routinely recommended in many modern treatment plans, because it may not improve healing and can sometimes make monitoring symptoms more difficult. Most people start feeling better within a day, and many recover fully within 48 to 72 hours. However, severe pain, worsening vision, or delayed improvement should prompt re-evaluation. If doctors need a detailed look at the front of the eye or want to exclude a deeper corneal problem, they may use corneal topography or other specialist eye assessments as part of a broader evaluation.
Prevention and self-care
Prevention comes down to one thing: reliable UV protection. Sunglasses should block 100% of UVA and UVB and fit well enough to reduce light entering from the sides. Wraparound styles are especially useful near water, sand, and snow. In winter sports or high-altitude environments, snow goggles with proper UV filtration are often the safest choice.
For occupational exposure, protective shields and safety eyewear designed for the specific task are essential. Welders should use approved helmets and filters, and bystanders nearby should also protect their eyes. Tanning beds and artificial UV sources should be approached with caution, as the eyes can be injured even during relatively short exposures if protective eyewear is not used.
At home, self-care after suspected exposure includes moving away from bright light, removing contact lenses, using lubricating drops if advised, and arranging medical review when pain or vision changes are notable. People with repeated irritation or underlying surface problems such as significant dry eye may benefit from a more comprehensive eye examination to discuss prevention strategies and ensure there is no separate eye condition contributing to symptoms.
When to seek medical care
Medical care is advisable if there is moderate to severe eye pain, reduced vision, symptoms in only one eye, significant discharge, or a feeling that something is still stuck in the eye. Assessment is also important after welding exposure, chemical exposure, trauma, or if the person cannot comfortably open the eyes. Children, contact lens wearers, and anyone with a history of eye disease should have a lower threshold for professional evaluation.
Urgent care is especially important if symptoms do not begin to improve within 24 hours, if they worsen, or if there are warning signs such as increasing redness, nausea with severe headache, or marked sensitivity to light with persistent blurred vision. These features can overlap with other eye conditions that need prompt treatment.
If you are travelling from abroad for a specialist opinion, Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals diagnose and treat eye conditions with coordinated care. The aim is straightforward: confirm what is going on, ease your symptoms safely, and protect your eyesight for the long run.
Frequently asked questions
01How long does photokeratitis last?
Most cases improve within 24 to 72 hours because the eye surface heals quickly. If symptoms are not clearly improving after a day, or if vision is getting worse, a doctor should re-evaluate the eye.
02Can photokeratitis cause permanent damage?
Uncomplicated photokeratitis usually heals without lasting damage. Permanent problems are uncommon, but severe exposure, repeated UV injury, or a missed alternative diagnosis can increase risk, which is why persistent symptoms should be checked.
03Is photokeratitis the same as snow blindness?
Yes. Snow blindness is a common name for photokeratitis that happens after UV light reflects strongly off snow or ice. The same type of injury can also happen at the beach, on the water, or during welding.
04Should contact lenses be worn during recovery?
No, contact lenses should generally be removed and not worn again until the eye has healed and a clinician says it is safe. Lenses can worsen irritation and may raise the risk of infection while the corneal surface is recovering.
05Can eye drops help photokeratitis?
Lubricating drops or ointment can help relieve discomfort and support the healing surface. Prescription drops are sometimes used depending on the examination, but self-treating with leftover medications is not recommended without medical advice.
06How can photokeratitis be prevented?
The best prevention is well-fitting eye protection that blocks 100% of UVA and UVB. Wraparound sunglasses, ski goggles, and approved welding shields are especially important around snow, water, sand, high altitude, and artificial UV sources.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.