Pancreatitis Supportive Therapy: Early Signs, Risk Factors, and How It Is Treated

A sudden, boring pain high in your abdomen that won’t let up — one that may bore straight through to your back — is not something to wait out at home. That kind of pain is often how pancreatitis announces itself.
Supportive therapy for pancreatitis means steadying you first: controlling the pain and nausea, giving fluids and nutrition, and watching closely for complications while the team works out what caused the attack and treats it. Getting seen early matters, because pancreatitis can be mild and settle on its own — or it can be severe and need hospital care.
What Is Pancreatitis Supportive Therapy?
Pancreatitis supportive therapy is the medical care used to help a person recover when the pancreas becomes inflamed. It usually includes assessment in a hospital or emergency setting, fluid replacement, pain control, treatment for nausea, nutritional support, and regular checks for complications. At the same time, the clinical team looks for the trigger, such as gallstones, alcohol-related pancreatic injury, very high blood triglycerides, or a medication effect.
The pancreas is an organ behind the stomach that helps digest food and regulates blood sugar through hormone production. In pancreatitis, digestive enzymes can become active too early and irritate pancreatic tissue. Acute pancreatitis starts suddenly and may resolve after treatment, whereas chronic pancreatitis is ongoing inflammation that can gradually cause permanent pancreatic damage.
If you hear the word “supportive,” don’t read it as “doing nothing.” It is active treatment that protects your hydration, nutrition, breathing, circulation, comfort, and organ function while the inflammation settles. The individual plan depends on symptom severity, test results, the suspected cause, and whether complications are present.
Early Signs and Symptoms of Pancreatitis
The most typical symptom of acute pancreatitis is sudden pain in the upper abdomen. The pain may be severe and persistent, may spread through to the back, and can worsen after eating. Some people find that sitting forward or curling slightly forward is more comfortable, although this does not confirm the diagnosis.
Other possible symptoms include nausea, vomiting, abdominal tenderness or bloating, fever, a fast heartbeat, and difficulty eating or drinking. Symptoms vary considerably. Mild cases may involve significant pain but improve within days, while more serious inflammation can cause dehydration, low blood pressure, breathing problems, or effects on the kidneys and other organs.
Chronic pancreatitis may cause repeated or ongoing upper abdominal discomfort, unintended weight loss, nausea, and greasy, loose, or difficult-to-flush stools. These stool changes can occur when the pancreas no longer produces enough digestive enzymes to absorb fat normally. Over time, chronic pancreatitis can also contribute to diabetes because insulin-producing cells may be affected.
- Sudden Abdominal Pain: Causes and Treatment" class="ahp-ilk">upper abdominal pain that does not settle should be assessed urgently.
- Repeated vomiting, fever, marked weakness, or inability to keep fluids down needs prompt care.
- Yellowing of the skin or eyes may suggest a bile duct problem, including a gallstone blockage.
Causes and Risk Factors
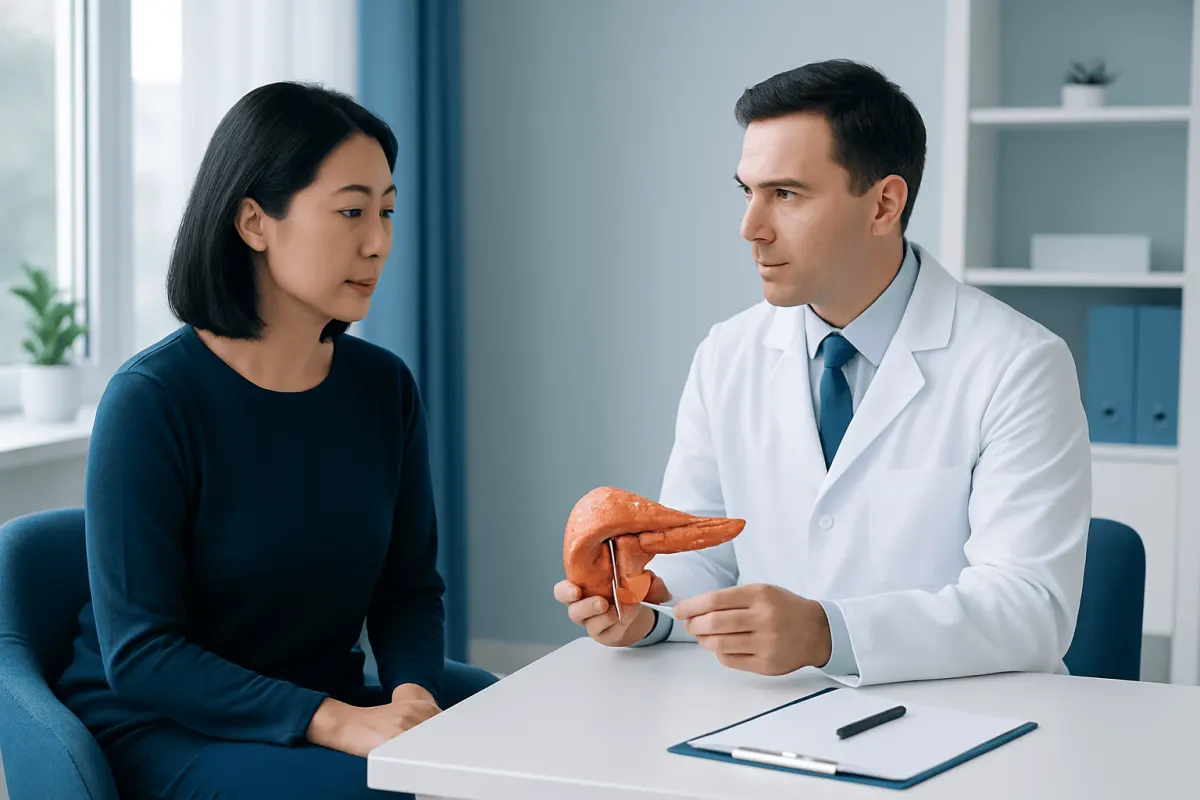
Gallstones and alcohol use are among the most common causes of acute pancreatitis. A gallstone can move from the gallbladder into the bile duct and obstruct the area where pancreatic drainage occurs. Alcohol can injure the pancreas over time and may lead to either acute episodes or chronic disease, although not everyone who drinks alcohol develops pancreatitis.
Other recognized causes include markedly elevated triglyceride levels, high calcium levels, abdominal injury, some infections, inherited conditions, autoimmune pancreatitis, and certain medicines. Pancreatitis can also occur after an endoscopic procedure involving the bile or pancreatic ducts, called ERCP. In some cases, even careful testing does not identify a clear cause; this may be described as idiopathic pancreatitis.
Risk is influenced by personal health history. Previous pancreatitis, gallstones, smoking, obesity, poorly controlled triglycerides, and continued heavy alcohol use can raise the likelihood of future episodes. A clinician may also review family history and medication use, because identifying a reversible cause is an important part of preventing recurrence.
How Pancreatitis Is Diagnosed and Assessed
Clinicians diagnose pancreatitis using the person’s symptoms, physical examination, and blood tests. Blood levels of pancreatic enzymes, especially lipase, are commonly measured. Tests may also assess liver function, blood count, kidney function, electrolytes, blood sugar, calcium, triglycerides, and markers that help the team understand how the illness is affecting the body.
Imaging is selected according to the clinical situation. An abdominal ultrasound is often used to look for gallstones and widening of the bile ducts. CT, MRI, or MRCP imaging may be used when the diagnosis is uncertain, symptoms are severe, a complication is suspected, or the care team needs a more detailed view of the pancreas and bile ducts.
The watching does not stop once the diagnosis is made. Medical teams monitor pain, urine output, blood pressure, pulse, oxygen levels, temperature, fluid balance, and the ability to tolerate food. This helps distinguish mild acute pancreatitis from cases that need more intensive observation or organ support. Imaging is not always needed immediately in a straightforward mild case, as results may not change early treatment.
What Supportive Treatment Involves
In acute pancreatitis, early supportive care often begins with intravenous fluids to correct dehydration and maintain circulation. The amount and type of fluid are tailored to the individual, because both insufficient and excessive fluid administration can be harmful. Frequent clinical review and blood tests help guide this treatment.
Pain is treated with appropriate medicines, and anti-nausea medication may be offered when needed. Oxygen, breathing support, or treatment in a higher-acuity unit may be necessary for people with severe disease. Antibiotics are not routinely used for uncomplicated pancreatitis because the inflammation itself is often not caused by a bacterial infection; they may be used when there is evidence of an infection elsewhere or an infected pancreatic complication.
Food matters here more than most people expect. People are generally encouraged to resume eating when nausea and pain allow, often starting with easily tolerated foods. If oral intake is not possible for a prolonged period or illness is severe, nutrition may be provided through a feeding tube into the stomach or small intestine. Tube feeding is often preferred over intravenous nutrition when feasible because it helps support the gut.
Sorting out the cause often takes a step beyond supportive care. For example, a bile duct blockage from gallstones may need urgent endoscopic treatment, and gallbladder removal may be advised after recovery to reduce recurrence. High triglycerides, alcohol dependence, medication concerns, and autoimmune causes each require a tailored plan. Chronic pancreatitis management can include nutrition support, pancreatic enzyme replacement, diabetes care, pain management, and treatment of complications.
Recovery, Prevention, and Self-Care
Recovery time depends on the cause and severity of pancreatitis. Many people with mild acute pancreatitis begin improving within several days, but tiredness and appetite changes can persist temporarily. Before leaving hospital, the care team may discuss follow-up tests, diet progression, medication changes, and whether treatment of gallstones or another underlying condition is needed.
After an episode, avoiding alcohol is important, particularly when alcohol may have contributed to pancreatic inflammation. Stopping smoking is also strongly recommended, as smoking can increase the risk of recurrent acute pancreatitis and progression of chronic pancreatitis. People who would like support with alcohol reduction or smoking cessation should discuss available services with a healthcare professional.
Eating a balanced diet usually does you more good than cutting things out sharply. Smaller meals may be easier during recovery, and limiting very fatty foods can reduce discomfort for some people, especially if digestion is impaired. However, long-term dietary changes should be individualized with a doctor or dietitian, particularly for people who have weight loss, diabetes, or signs of poor nutrient absorption.
If you have had more than one episode, follow-up really counts. Managing triglycerides, diabetes, gallstones, and other relevant health conditions can lower risk. People with chronic pancreatitis should seek medical advice about new pain, weight loss, diarrhea, or changes in blood sugar, since these symptoms may indicate a need to adjust treatment.
When to Seek Medical Care
Anyone with new, severe, or persistent upper abdominal pain should seek urgent medical assessment, particularly when pain is accompanied by vomiting, fever, or pain spreading to the back. Pancreatitis cannot be safely diagnosed at home, and similar symptoms can also occur with gallbladder disease, ulcers, bowel conditions, heart problems, and other illnesses that need timely evaluation.
Emergency care is particularly important for fainting, confusion, shortness of breath, chest pain, a swollen or very tender abdomen, persistent inability to drink fluids, yellow skin or eyes, or signs of severe dehydration such as very little urine. These symptoms may indicate a serious complication or another urgent condition.
People who have had pancreatitis before should contact their clinician promptly if familiar symptoms return, even if they seem milder than a prior episode. Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals diagnose and treat pancreatitis for international patients, with care plans based on the suspected cause and each person’s clinical needs.
Frequently asked questions
01Can pancreatitis be treated at home?
Suspected acute pancreatitis should not be managed at home without medical assessment. It can cause dehydration and, in some cases, complications that need monitoring and hospital-based treatment. A doctor can determine whether symptoms are due to pancreatitis and how severe the illness is.
02What is the main goal of pancreatitis supportive therapy?
The main goal is to support the body while pancreatic inflammation improves and to prevent or identify complications early. This includes managing fluids, pain, nausea, nutrition, and organ function. Clinicians also investigate and address the underlying cause whenever possible.
03Will a person with pancreatitis need to stop eating?
Not always. Current care commonly supports restarting oral food as soon as pain and nausea improve enough for the person to tolerate it. If eating is not possible, a feeding tube may be used in some cases to provide nutrition safely.
04Are antibiotics routinely given for pancreatitis?
No. Most acute pancreatitis is inflammatory rather than caused by a bacterial infection, so antibiotics are not routinely needed. They may be prescribed if a clinician identifies a bacterial infection, such as cholangitis, pneumonia, a urinary infection, or infected pancreatic tissue.
05Can pancreatitis happen again?
Yes, recurrence is possible if the underlying cause remains present. Removing gallstones when appropriate, avoiding alcohol, stopping smoking, and treating high triglycerides can reduce risk. Follow-up care is important after any episode, especially if the cause was not clear.
06What is the difference between acute and chronic pancreatitis?
Acute pancreatitis is a sudden episode of inflammation that may resolve completely, particularly when the cause is treated. Chronic pancreatitis involves repeated or long-lasting inflammation that can lead to permanent damage. Chronic disease may affect digestion and blood sugar control over time.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Persistent digestive symptoms? Get evaluated in Turkey
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.