MitraClip vs Open Mitral Valve Surgery: Choosing Care

MitraClip and open mitral valve surgery can both treat mitral regurgitation, a leaking mitral heart valve. The best approach depends on why the valve leaks, whether a durable surgical repair is feasible, the person’s symptoms, heart function, anatomy and overall surgical risk.
Overview: Why Mitral Valve Treatment Is Needed
The mitral valve sits between the heart’s left upper and lower chambers. It should close tightly as the heart pumps blood forward. When it does not close properly, blood can flow backward into the left atrium. This is called mitral regurgitation, or a leaky mitral valve.
Mild regurgitation may only need monitoring. However, severe regurgitation can cause breathlessness, tiredness, reduced exercise tolerance, fluid retention, irregular heart rhythms or enlargement and weakening of the heart over time. In suitable patients, repairing or replacing the valve can reduce symptoms and help protect heart function.
Two important treatment approaches are open mitral valve surgery and MitraClip, also called transcatheter edge-to-edge repair. They are not interchangeable options for every person. A cardiology and cardiac surgery team evaluates which treatment can provide the safest and most effective result for the individual valve and overall health situation.
What Are MitraClip and Open Mitral Valve Surgery?
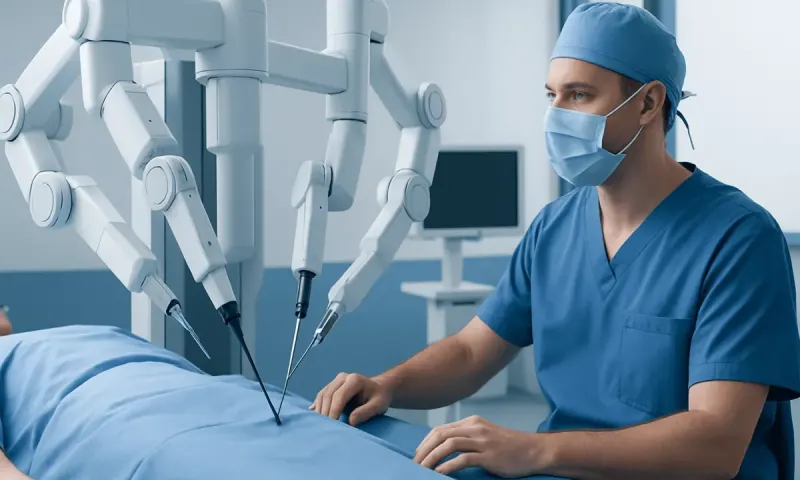
Open mitral valve surgery is performed in an operating room under general anesthesia. The surgeon reaches the heart through an incision in the chest, often using a heart-lung machine during the procedure. Whenever possible, the surgeon repairs the person’s own valve. Repair may involve reshaping valve tissue, replacing or strengthening supporting cords, or placing a supportive ring around the valve. If repair is not possible, the valve may be replaced with a mechanical or biological valve.
MitraClip is a minimally invasive catheter procedure. A specialist inserts a thin tube through a vein in the groin and guides it into the heart. A small clip is positioned to bring portions of the leaking mitral valve leaflets closer together, improving closure and reducing backward flow. It does not require opening the chest.
The procedure is commonly performed with general anesthesia and detailed ultrasound imaging from the esophagus, called transesophageal echocardiography. MitraClip can substantially reduce leakage in appropriately selected patients, but it does not reconstruct every part of the valve in the way surgery can.
- Surgery may offer the most complete and durable correction for many repairable degenerative valve problems.
- MitraClip can be a valuable alternative for selected patients for whom surgery would carry excessive risk or is not suitable.
The Cause of the Leak Matters

One of the first questions is why the mitral valve is leaking. In primary, or degenerative, mitral regurgitation, the valve itself is abnormal. For example, a leaflet may prolapse because supporting tissue has stretched or ruptured. When an experienced surgical team expects a durable repair, surgery is often the preferred treatment for people who can safely undergo it.
In secondary, or functional, mitral regurgitation, the valve leaflets may be structurally normal but do not meet properly because the left ventricle has enlarged or changed shape. This can occur with heart failure, coronary artery disease or previous heart muscle injury. Medicines and other heart-failure treatments are important first steps, and selected patients may be evaluated for MitraClip if significant symptoms and leakage persist.
Other causes, such as infection of the valve, rheumatic valve disease, severe valve calcium buildup or radiation-related changes, need individualized assessment. Some of these conditions may require surgery because tissue needs to be removed, repaired or replaced. In some cases, other valve or heart conditions can also influence the recommended approach.
A related condition, mitral valve regurgitation, can range from mild to severe. The cause, severity and effects on the heart help determine whether monitoring, medication, a catheter procedure or surgery is appropriate.
How Specialists Decide Between MitraClip and Surgery
Treatment choice is made through a comprehensive assessment rather than by age alone. Echocardiography is the main imaging test used to measure the severity of leakage, examine leaflet motion and assess heart size and pumping function. A transesophageal echocardiogram and sometimes CT imaging may be needed to determine whether the valve anatomy is suitable for a clip.
For MitraClip, the location and width of the leak, leaflet length and mobility, degree of calcification, valve opening size and the relationship of the leaflets all matter. The team also considers whether placing a clip could narrow the valve too much and create mitral stenosis. Some valves simply cannot be treated safely or effectively with a clip.
For surgery, clinicians estimate operative risk using the person’s medical history, physical condition and validated risk tools. Factors can include lung disease, kidney impairment, frailty, prior chest surgery, liver disease, previous radiation treatment, coronary artery disease and whether additional procedures are needed. If bypass surgery, treatment of another valve, or surgery for an enlarged aorta is needed at the same time, open surgery may be the more practical way to address all problems together.
Guidelines recommend discussion by a multidisciplinary heart team, often including an interventional cardiologist, cardiac surgeon, imaging specialist, anesthesiologist and heart-failure clinician. The patient’s priorities, expected recovery, travel and support needs, and personal preferences should be included in shared decision-making.
Benefits, Limits and Recovery Considerations
Open surgery can provide a highly durable repair, particularly for certain degenerative valve conditions treated in experienced repair centers. It also allows the surgeon to directly assess the valve and address complex structural problems. However, it is a major operation. Recovery generally takes longer, and risks may include bleeding, infection, stroke, irregular rhythms, kidney complications and complications related to anesthesia or the heart-lung machine.
MitraClip avoids a chest incision and is usually associated with a shorter hospital stay and earlier physical recovery than open surgery. It can improve symptoms and reduce regurgitation for many carefully selected patients. Its main limitations are that it may leave some residual leakage, may not provide the same long-term durability as a successful surgical repair in every situation, and is not suitable for all forms of mitral valve disease.
Neither approach removes the need for follow-up. Repeat echocardiograms help assess the valve and heart function. People may still need medicines for heart failure, blood pressure, rhythm disorders or fluid control. Depending on the situation, care may include heart failure treatment alongside valve intervention.
Recovery planning should be individualized. After surgery, cardiac rehabilitation can support a gradual return to activity. After MitraClip, clinicians typically advise wound care for the groin access site, short-term activity restrictions and prompt reporting of new or worsening symptoms.
Preparing for a Heart Team Consultation
People referred for mitral valve treatment can prepare by bringing prior echocardiogram reports, cardiac imaging, medication lists, records of previous procedures and information about symptoms. It can be helpful to note when breathlessness occurs, whether activity has become more difficult, and whether there has been ankle swelling, palpitations, fainting or chest discomfort.
Useful questions include: Is the leak primary or secondary? Is my valve likely to be repairable with surgery? Is my anatomy suitable for MitraClip? What are the goals of treatment in my case? Will I need other heart procedures? What does recovery involve, and what follow-up will be needed?
A person should also tell the team about medicines, allergies, dental problems, past bleeding, kidney disease and plans for pregnancy, if relevant. Anticoagulants, diabetes medicines and some supplements may need special instructions before either procedure. Medication changes should only be made under the guidance of the treating team.
Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals evaluate and treat mitral valve conditions for international patients, with treatment planning based on individual clinical findings.
When to Seek Medical Care
Anyone with known moderate or severe mitral regurgitation should attend recommended cardiology follow-up appointments, even if they feel well. Symptoms can develop gradually, and imaging may identify changes in heart size or function before they are obvious in daily life. Earlier assessment can help ensure treatment is considered at the appropriate time.
A medical review should be arranged for increasing shortness of breath, reduced ability to exercise, persistent fatigue, new swelling in the legs or abdomen, awareness of a fast or irregular heartbeat, or unexplained weight gain related to fluid retention. These symptoms can have many causes, but they deserve assessment, particularly in someone with valve disease.
Urgent medical attention is needed for severe or sudden breathlessness, fainting, chest pain, blue or gray lips, confusion, or symptoms of stroke such as facial drooping, arm weakness or difficulty speaking. These symptoms may indicate a serious heart or circulation problem and should not be managed at home.
The choice between MitraClip and surgery should be revisited if symptoms, heart function or health status changes. A treatment that is not right at one point may become appropriate later, and ongoing care helps keep the plan aligned with the person’s needs.
Frequently asked questions
01Is MitraClip better than open mitral valve surgery?
Neither treatment is universally better. Open surgery is often favored when a lasting valve repair is feasible and the person can safely have surgery, while MitraClip is particularly valuable for selected people with high surgical risk or unsuitable surgical options. The best choice depends on valve anatomy, the cause of regurgitation and overall health.
02Can MitraClip replace mitral valve surgery?
MitraClip can be an alternative to surgery for some patients, but it cannot replace surgery in every situation. Complex valve damage, active valve infection, certain anatomical features and the need for additional heart surgery may make open surgery more appropriate. A heart team can determine whether catheter treatment is technically suitable.
03Who is usually eligible for MitraClip?
Eligibility generally includes significant mitral regurgitation, symptoms or heart-related effects despite appropriate medical care when relevant, and valve anatomy that can be treated with a clip. It is commonly considered when surgical risk is high or prohibitive, although exact eligibility depends on the cause of the leak and local clinical guidelines. Detailed imaging is essential before a decision is made.
04How long does recovery take after MitraClip compared with surgery?
Recovery after MitraClip is usually shorter because the procedure uses a vein in the groin rather than a chest incision. Many people leave the hospital sooner and resume light activities earlier than after open surgery. Surgical recovery varies, but it generally requires several weeks and may include cardiac rehabilitation.
05Will mitral regurgitation return after treatment?
Residual or recurrent leakage can occur after either MitraClip or surgery. The likelihood depends on the original valve problem, the procedure performed, the condition of the heart and the durability of the repair. Regular clinical reviews and echocardiograms are important after treatment.
06Are medications still needed after MitraClip or mitral valve surgery?
Some people continue to need medicines after valve treatment, especially if they have heart failure, high blood pressure, atrial fibrillation or coronary artery disease. The medication plan may change over time based on symptoms, heart function and the type of valve procedure. A cardiologist should guide all medication decisions.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Heart care in Turkey — expert evaluation and treatment
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.