

Laparoscopic vs Robotic Surgery: Key Differences

Laparoscopic and robotic surgery are both minimally invasive approaches performed through small incisions. In laparoscopic surgery, the surgeon directly holds the instruments; in robotic-assisted surgery, the surgeon controls robotic instruments from a console, which can provide magnified 3D vision and greater instrument flexibility.
Overview: a side-by-side comparison
What is the difference between laparoscopic and robotic surgery? Both are minimally invasive operations performed through several small incisions rather than one large opening. The main difference is how the surgeon views the surgical area and controls the instruments: laparoscopic instruments are held directly by the surgeon, while robotic-assisted instruments are controlled by the surgeon from a nearby console.
Neither technique means that surgery is performed without a surgeon. In robotic-assisted surgery, the surgeon remains in full control throughout the procedure. The robotic platform translates the surgeon’s hand movements into precise movements of small instruments inside the body.
| Feature | Laparoscopic surgery | Robotic-assisted surgery |
|---|---|---|
| Surgeon control | Surgeon holds and moves long instruments directly | Surgeon controls instruments from a console |
| View of the operation | Usually a high-definition 2D camera image | Usually magnified high-definition 3D visualization |
| Instrument movement | Long, rigid instruments with limited angles | Wristed instruments that can rotate and articulate inside the body |
| Incisions | Several small incisions | Several small incisions, often similar in size and number |
| Suitable uses | Many common abdominal, pelvic, chest, and other procedures | Selected procedures where visualization and precision may be especially useful |
| Recovery | Often faster than open surgery, depending on the procedure | Often similar to laparoscopy; depends on the operation and individual factors |
Both methods may reduce tissue disruption compared with open surgery, but they are not interchangeable in every situation. Some operations are safest when performed openly, especially in emergencies, complex anatomy, significant scar tissue, or when an unexpected finding occurs.
How a clinician tells the approaches apart
A clinician distinguishes laparoscopic and robotic-assisted surgery by the surgical platform, not simply by the size of the scars. Both approaches commonly involve a camera inserted through a small port and additional ports for instruments. Carbon dioxide gas may be used during abdominal procedures to create working space.
During laparoscopy, the operating surgeon stands beside the patient and manipulates the camera and instruments by hand. The surgeon works while looking at a monitor. During robotic-assisted surgery, the surgeon sits at a console and controls the robotic arms; a trained operating-room team remains at the patient’s side to assist with positioning, instrument changes, and safety checks.
The terms can occasionally be confusing because robotic surgery is a form of minimally invasive surgery and may also be described as robot-assisted laparoscopy. A procedure can also begin laparoscopically or robotically and be converted to open surgery if this becomes the safest option. Conversion is a clinical safety decision, not necessarily a complication or failure.
Before recommending an approach, the surgical team considers the diagnosis, location of the problem, prior operations, body anatomy, need for reconstruction, anesthesia considerations, and the surgeon’s experience with each technique.
Why do surgeons prefer robotic surgery?
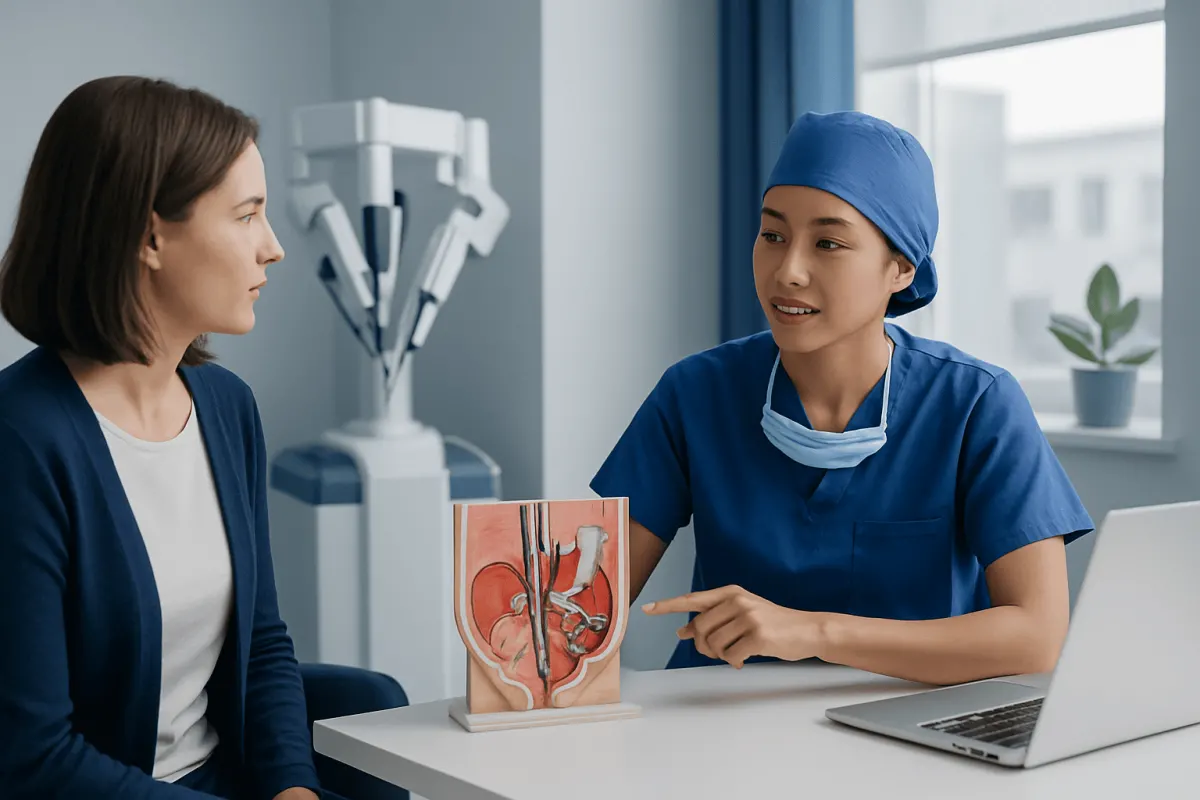
Some surgeons prefer robotic assistance for selected procedures because the system can offer a stable, magnified 3D view and instruments that bend and rotate in ways that standard laparoscopic instruments cannot. These features can be helpful when operating in confined spaces, working around delicate structures, or placing detailed sutures.
For example, robotic techniques may be considered in certain pelvic, colorectal, urologic, gynecologic, thoracic, and complex abdominal operations. The technology can improve ergonomics for the surgeon as well, potentially reducing the physical strain of long procedures.
However, a surgeon’s preference should always be matched to the patient’s needs. A well-performed laparoscopic procedure may be an excellent choice for many people, and for some operations it may be simpler and just as effective. The important question is not which technology is newest, but which approach is likely to provide a safe, appropriate operation for that individual.
Patients can reasonably ask their surgeon why a particular approach is advised, how often the surgeon performs that procedure using the proposed method, and what alternatives are available.
Which surgery is better, robotic or laparoscopic?
Neither robotic nor laparoscopic surgery is universally better. The most suitable method depends on the operation being performed, the patient’s anatomy and health, the complexity of the condition, and the experience of the surgical team.
For straightforward operations, standard laparoscopy may provide very similar results with small incisions and a relatively efficient procedure. In other cases, robotic assistance may make technically demanding dissection or reconstruction more manageable. Evidence comparing the two approaches varies by operation, and differences in recovery or complication rates are often small when both are performed by experienced teams.
For people asking about the difference between laparoscopic and robotic hernia surgery, both approaches repair the hernia through small incisions and usually place mesh when clinically appropriate. Robotic assistance may facilitate suturing and repair in some complex, recurrent, or bilateral hernias, but conventional laparoscopy remains an established option.
For the difference between laparoscopic and robotic gallbladder surgery, laparoscopic removal is widely used and effective for most people needing gallbladder surgery. Robotic removal may be used in selected settings, but it is not routinely necessary solely because it is robotic. Treatment planning should be individualized for conditions such as gallstones or gallbladder inflammation.
What is the downside of robotic surgery?
Robotic surgery has potential limitations. It requires specialized equipment, operating-room staff, and surgeons with specific training. Set-up can take time, and not every hospital or surgical center has the same robotic platforms or experience with every type of procedure.
As with any surgery, robotic procedures carry possible risks related to anesthesia, bleeding, infection, blood clots, injury to nearby structures, or the need to change to an open operation. These risks depend much more on the type of surgery and a person’s health than on the word “robotic” alone.
Another practical consideration is cost. The cost difference between laparoscopic and robotic surgery can vary substantially by country, hospital, insurance coverage, procedure, equipment use, and length of stay. The cost difference between laparoscopic and robotic surgery in India also varies between cities, institutions, and individual care plans, so people should request a written estimate and ask what is included.
Robotic technology can be valuable when it serves a clear clinical purpose, but it should not replace shared decision-making. Patients should feel comfortable asking whether the expected benefits of robotic assistance apply to their own procedure.
Is robotic surgery more painful than laparoscopic surgery?
Robotic surgery is generally not expected to be more painful than laparoscopic surgery simply because a robot is used. Both approaches use small incisions, and many people experience less incision-related discomfort and a faster return to everyday activities than they would after a comparable open operation.
However, pain varies from person to person. The underlying condition, size and position of the incisions, extent of tissue work, use of gas in abdominal surgery, duration of the operation, and individual pain sensitivity can all affect recovery. Shoulder-tip discomfort for a short time after abdominal minimally invasive surgery can occur because of the gas used to create space.
After surgery, the care team may recommend early gentle movement, breathing exercises, hydration, wound care, and prescribed or over-the-counter pain medicines when appropriate. Patients should follow their surgeon’s instructions, particularly regarding driving, lifting, exercise, bathing, and returning to work.
Increasing pain rather than gradual improvement, fever, persistent vomiting, wound redness or drainage, chest pain, shortness of breath, or leg swelling should be reported promptly to the surgical team or assessed urgently as advised.
What to do for each case: preparing for a surgical decision
When surgery is being considered, patients should first understand the diagnosis and whether an operation is needed now. In some cases, observation, medicines, lifestyle measures, endoscopy, or other treatments may be appropriate alternatives. If surgery is recommended, the surgeon can explain whether open, laparoscopic, or robotic-assisted treatment is most suitable.
Useful questions include: What is the goal of the operation? Why is this approach recommended for this case? What are the expected benefits and possible complications? Could the surgery need to change to an open procedure? What recovery restrictions should be expected? How will the procedure be covered or billed?
People sometimes search for the difference between laparoscopic and robotic surgery in Hindi. The core distinction is the same in any language: in laparoscopy, the surgeon operates using hand-held long instruments, while in robotic-assisted surgery, the surgeon controls robotic instruments from a console. An interpreter or translated consent discussion can help ensure that a patient understands the plan before agreeing to surgery.
For people with conditions that may require abdominal surgery, discussion with a qualified Trauma Surgeon: Key Differences" class="ahp-ilk">general surgeon is the safest next step. The decision should be based on clinical assessment rather than online comparisons alone.
When to seek medical care
Medical advice is appropriate when symptoms may suggest a condition requiring assessment, such as persistent or severe abdominal or pelvic pain, repeated vomiting, fever with abdominal pain, yellowing of the skin or eyes, a painful or enlarging hernia bulge, unexplained weight loss, rectal bleeding, or a major change in bowel habits.
Urgent assessment is important for sudden severe pain, a rigid abdomen, fainting, vomiting blood, black stools, inability to pass stool or gas with abdominal swelling, chest pain, difficulty breathing, or a hernia bulge that becomes very painful, discolored, or cannot be gently reduced. These symptoms can have many causes, but they should not be ignored.
People preparing for planned surgery should tell the care team about all medicines, allergies, prior operations, pregnancy possibility, smoking or nicotine use, and chronic conditions. They should not stop prescription medicines unless advised by a clinician.
Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals assess surgical conditions and discuss appropriate open, laparoscopic, and robotic-assisted options for international patients.
Frequently asked questions
01Is robotic surgery the same as laparoscopic surgery?
Robotic-assisted surgery is a type of minimally invasive surgery and is closely related to laparoscopy. Both use small incisions and a camera, but the surgeon controls robotic instruments from a console rather than holding conventional laparoscopic instruments directly.
02Does the robot operate on the patient by itself?
No. The surgeon controls the robotic system throughout the procedure and makes all operative decisions. The robot does not act independently or replace the surgical team.
03Are robotic surgery scars smaller than laparoscopic scars?
Scars are often similar because both techniques typically use several small ports. The exact number, size, and location of incisions depend on the operation, the patient’s anatomy, and whether an additional incision is needed to remove tissue or an organ.
04Is recovery faster after robotic surgery?
Recovery can be quicker than after open surgery for many minimally invasive operations, but robotic surgery is not always faster than standard laparoscopy. Recovery depends on the procedure, the reason for surgery, overall health, and whether complications occur.
05Can every operation be done robotically?
No. Not all operations are appropriate for robotic assistance, and some are best performed laparoscopically or through an open incision. Emergency circumstances, complex disease, prior surgery, and the need for direct access may influence the choice.
06What should a patient ask before robotic surgery?
Patients can ask why robotic assistance is recommended, what alternatives exist, and what experience the surgeon has with the planned procedure. It is also sensible to ask about possible conversion to open surgery, expected recovery, risks, and estimated out-of-pocket costs.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


