Embryo Heart Rate by Week: Normal Ranges and Meaning
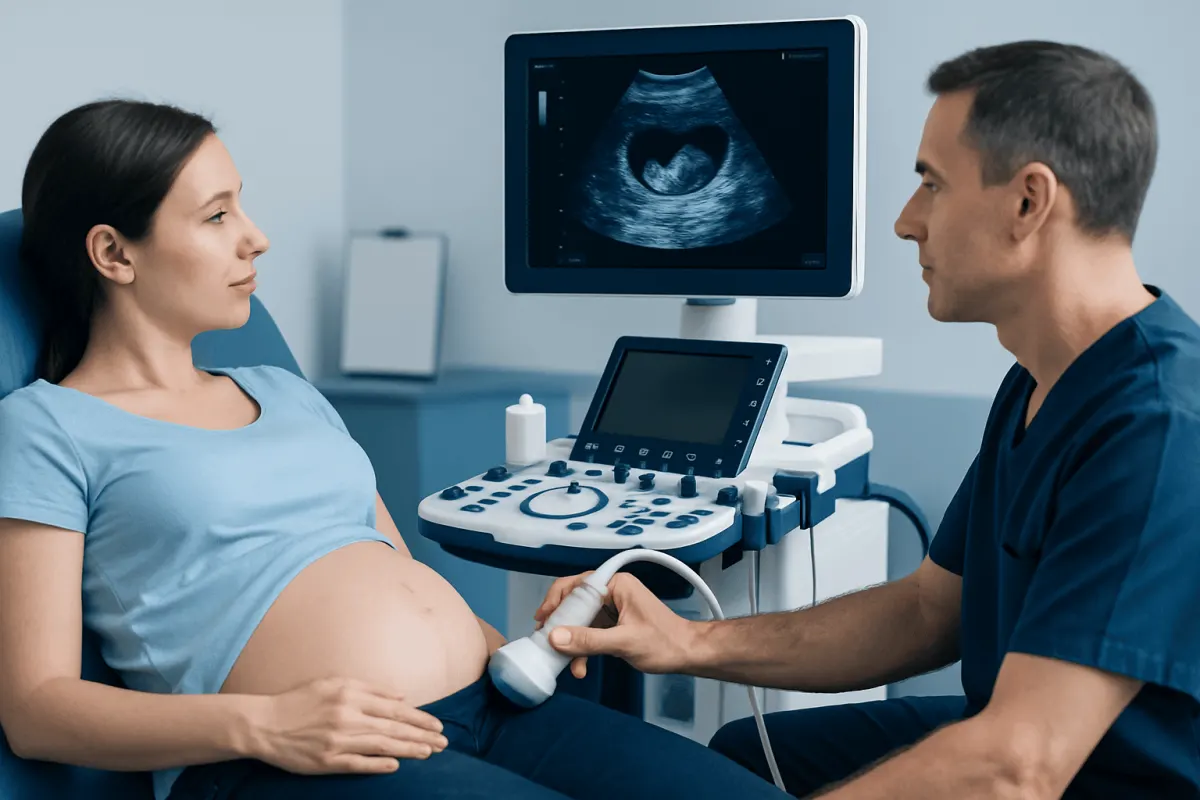
Embryo heart rate is assessed by ultrasound and changes rapidly during early development, so the pregnancy’s exact gestational age matters as much as the number itself. A single reading should be interpreted by a qualified clinician alongside embryo size, dating, symptoms, and follow-up findings.
Embryo Heart Rate: Why the Number Changes So Quickly
An embryo heart rate is the number of heartbeats measured in one minute during an early pregnancy ultrasound. It is an important observation because the developing heart begins beating early in pregnancy, but the rate is not fixed: it normally changes quickly from week to week. For this reason, the most useful interpretation combines the heart rate with the gestational age, embryo measurement and the type of ultrasound performed.
In the earliest weeks, clinicians may refer to an embryonic heart rate or cardiac activity. Later in pregnancy, the term fetal heart rate is more commonly used. A heartbeat that is not yet visible very early in pregnancy does not automatically mean that there is a problem; ovulation, implantation or pregnancy dating may have occurred later than expected.
Ultrasound findings are best reviewed in context. A clinician may recommend another scan after an appropriate interval when dates are uncertain or the findings are earlier than expected. This approach can provide a clearer and more reliable picture than drawing conclusions from one early measurement.
What Is the Normal Heart Rate for an Embryo?
There is no single normal embryo heart rate for every stage of early pregnancy. In general, the rate begins relatively slowly once cardiac activity can first be detected, rises rapidly during the following weeks, and commonly reaches its highest range around the end of the embryonic period and early fetal period. It then gradually settles to a lower rate later in the first trimester.
As a broad clinical guide, an embryo heart rate at 5 weeks may not yet be detectable, especially on an abdominal scan. When cardiac activity is first seen around 5.5 to 6 weeks, the rate may be roughly 90 to 110 beats per minute. By 7 to 8 weeks it often rises into the approximate 120 to 170 beats-per-minute range. An embryo heart rate at 9 weeks and an embryo heart rate at 10 weeks may commonly be in the 150 to 190 beats-per-minute range, although individual findings vary.
These ranges are not diagnostic cutoffs for every pregnancy. The clinician also evaluates crown-rump length, whether the pregnancy is in the uterus, the person’s menstrual and ovulation history, and whether measurements match the estimated dates. A transvaginal ultrasound may identify early structures sooner and with more detail than an abdominal ultrasound.
- Very early pregnancy: cardiac activity may be too early to detect reliably.
- About 6 to 8 weeks: the rate generally rises quickly as the embryo develops.
- About 9 to 10 weeks: rates may be at their fastest in normal development.
- After the first trimester: the fetal heart rate usually slows into a lower, more stable range.
What Is a Concerning Fetal Heart Rate?

A concerning fetal heart rate is one that appears unexpectedly slow or fast for the gestational age, especially when it persists on repeat assessment or occurs with other ultrasound findings. In very early pregnancy, a slower-than-expected rate can be associated with a higher risk of pregnancy loss, but it is not a definite prediction for an individual pregnancy. Dating uncertainty is common and can substantially change how a measurement is interpreted.
Clinicians may pay particular attention to markedly low rates in an embryo whose size confirms a later gestational age, or to a sustained rate that is unusually high beyond the period when faster rates are expected. They also look for associated findings, including embryo growth, the yolk sac, pregnancy location, signs of bleeding around the gestational sac, and maternal symptoms.
A repeat ultrasound may be recommended when the heartbeat is slow, very early, difficult to measure, or inconsistent with the estimated pregnancy dates. Follow-up imaging can show whether growth and cardiac activity are progressing as expected. Blood tests for pregnancy hormone levels may occasionally be useful, but they do not replace ultrasound for evaluating embryo development.
Is 170 Too High for Fetal Heart Rate?
A fetal heart rate of 170 beats per minute is often not too high during early pregnancy. Around 8 to 10 weeks, it can fall within an expected physiologic range because the developing heart normally beats faster at this stage. Therefore, the answer depends strongly on when the measurement was taken and how the gestational age was established.
Later in pregnancy, clinicians use different expectations for the fetal heart rate. A rate above the expected range that remains elevated may be called fetal tachycardia and can prompt a fuller assessment. Temporary increases may occur with normal fetal activity, maternal fever, dehydration, certain medicines, infection, thyroid disease, or other factors; a clinician determines whether further evaluation is needed.
A single ultrasound reading should not be interpreted in isolation. The ultrasound team may recheck the rate during the scan, compare it with previous results, and consider maternal health and symptoms. Pregnant individuals should contact their maternity clinician if they have concerns about an ultrasound report rather than trying to interpret a number alone.
Does a Down Syndrome Fetus Have a Normal Heart Rate?
Yes. A fetus with Down syndrome can have a normal heart rate, and heart rate alone cannot diagnose or exclude Down syndrome. The same is true for most chromosomal conditions: fetal heart rhythm measurements are not used as a screening or diagnostic test for chromosome differences.
Screening for Down syndrome may include first-trimester ultrasound assessment, blood-based screening such as cell-free DNA screening, or combined screening based on local clinical practice. Screening estimates the chance of a condition but does not provide a diagnosis. Diagnostic tests, such as chorionic villus sampling or amniocentesis, can provide more definitive chromosome information when appropriate.
Some fetuses with Down syndrome have structural heart differences, while many do not. If an ultrasound suggests a possible structural concern or a screening result indicates increased chance, a clinician may discuss referral for detailed imaging, genetic counselling, or fetal echocardiography. These steps are individualized and should be discussed carefully with an obstetric or maternal-fetal medicine team.
How Embryo Heart Rate Is Measured and Followed
Embryo heart rate is usually measured during ultrasound by observing cardiac motion and calculating beats per minute. In very early pregnancy, a transvaginal scan often provides the clearest view because the embryo is small and located deep in the pelvis. As pregnancy progresses, abdominal ultrasound becomes increasingly informative.
At an early viability scan, clinicians generally assess more than the embryology heartbeat. They confirm the location of the pregnancy, look for a gestational sac and yolk sac when expected, measure the embryo, assess cardiac activity, and compare the findings with known dates. This comprehensive assessment helps prevent misinterpretation of one isolated feature.
If follow-up is needed, the timing is selected to allow meaningful developmental change. Repeating a scan too soon can increase uncertainty, while an interval of several days to about a week or more may clarify embryo growth and the heart rate pattern. The care team will recommend timing based on the individual ultrasound findings and clinical situation.
When to Seek Medical Care
Pregnant individuals should contact their obstetric clinician or early pregnancy service if they have questions about an embryo heart rate result, have been advised to arrange repeat imaging, or develop symptoms that concern them. Prompt medical assessment is particularly important with vaginal bleeding, worsening pelvic or abdominal pain, severe one-sided pain, dizziness, fainting, shoulder-tip pain, fever, or feeling acutely unwell.
Emergency care is appropriate for heavy bleeding, severe pain, collapse or fainting, or signs of a possible ectopic pregnancy. These symptoms need timely assessment regardless of whether a heartbeat has been seen previously. A confirmed intrauterine pregnancy and a reassuring heart rate do not replace evaluation when severe symptoms occur.
Routine prenatal care, avoiding alcohol and smoking, taking recommended prenatal supplements, and discussing prescribed or non-prescribed medicines with a clinician support general pregnancy health. Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals provide assessment and care for international patients with early-pregnancy concerns when needed.
Frequently asked questions
01Can an embryo heartbeat be seen at 5 weeks?
Sometimes, but it is often too early to see cardiac activity at 5 weeks, particularly if dates are based on the last menstrual period rather than confirmed ovulation. A transvaginal ultrasound may detect early development sooner than an abdominal scan. If the scan is inconclusive, a repeat ultrasound is commonly recommended.
02What is a normal embryo heart rate at 5 weeks?
At 5 weeks, a heartbeat may not yet be visible, so there is no single expected rate for every pregnancy at that point. When cardiac activity is first detected in the following days, the rate may initially be lower before rising rapidly. Accurate pregnancy dating is essential for interpretation.
03What should the embryo heart rate be at 9 weeks?
At 9 weeks, the heart rate is often relatively fast and may commonly fall around 150 to 190 beats per minute. Normal variation exists, and the measurement should be assessed with embryo size and ultrasound dating. A clinician can explain whether a specific result is appropriate for the pregnancy stage.
04What should the embryo heart rate be at 10 weeks?
At 10 weeks, the rate may still be near its early-pregnancy peak and can be higher than later in pregnancy. A value that would be considered fast later in gestation may be normal at this stage. The ultrasound report and the clinician’s interpretation are more informative than one number alone.
05Does a slow embryo heart rate always mean miscarriage?
No. A slow rate can increase concern in some circumstances, but it does not confirm miscarriage on its own. Uncertain dates, very early measurement, and technical factors can affect the result. Follow-up ultrasound is often the most helpful next step.
06Can stress cause a high fetal heart rate?
Everyday emotional stress is not usually considered a direct explanation for an abnormal fetal heart rate measurement. However, factors such as maternal fever, illness, dehydration, medicines, and later-pregnancy fetal activity can affect the rate. Any persistent or unexpected finding should be reviewed by the maternity care team.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Heart care in Turkey — expert evaluation and treatment
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.