

Bowens Disease: Early Signs, Risk Factors, and How It Is Treated
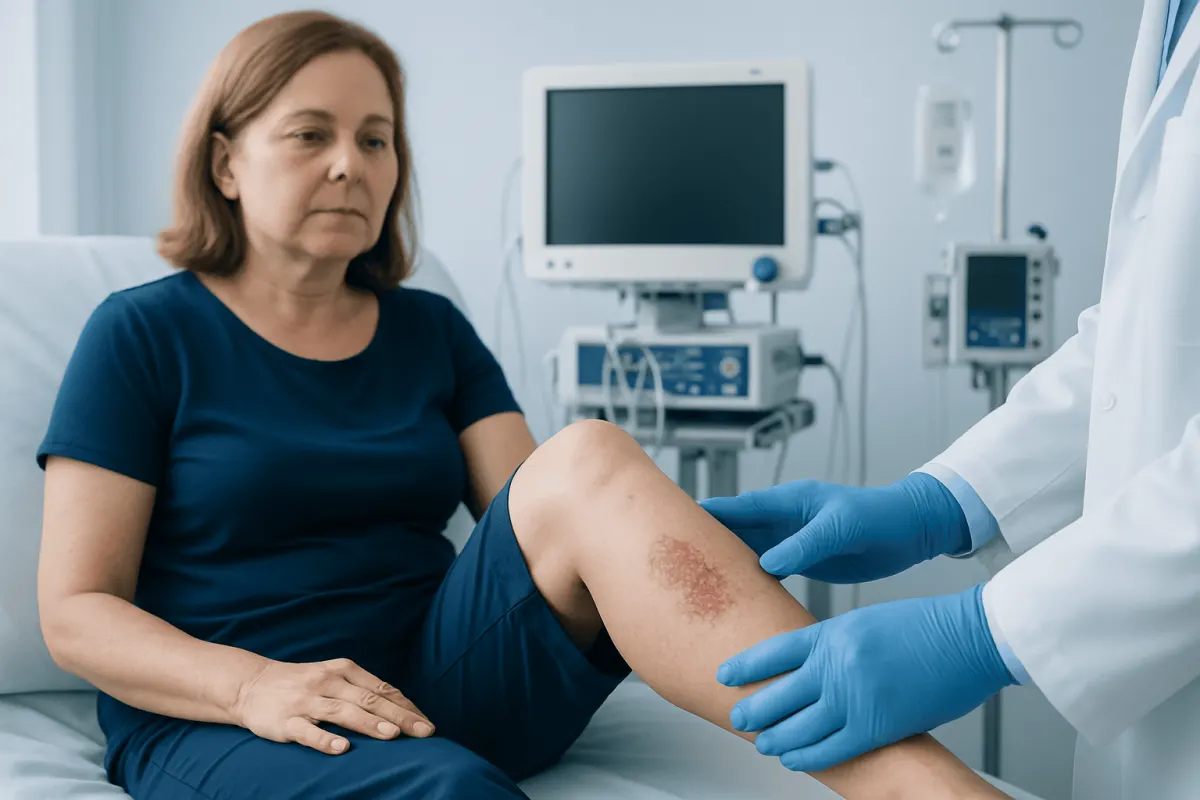
Have you got a scaly patch of skin that just will not clear up, no matter how much cream you put on it? Maybe it has been there for months. It might be red, or pink, or a little rough to the touch, and you have started to wonder whether it is more than dry skin.
Sometimes it is. Bowens disease, also called Acne Treatment Options: Topical, Oral, and Procedure-Based Care" class="ahp-ilk">Treatment Options" class="ahp-ilk">squamous cell carcinoma in situ, is a very early form of skin cancer confined to the outer layer of the skin. It often appears as a persistent scaly patch and can usually be treated effectively before it grows deeper into the skin.
What Is Bowens Disease?
Bowens disease is an early form of squamous cell carcinoma, a common type of skin cancer. It is also known as squamous cell carcinoma in situ. “In situ” means that the abnormal cells are present only in the epidermis, the thin outer layer of the skin, and have not grown into deeper tissues.
Because it stays in the surface layer, Bowens disease is generally very treatable. That said, please do not ignore it. Left alone, a lesion can sometimes develop into invasive squamous cell carcinoma, where the cancer cells extend deeper into the skin. Getting it looked at and treated early helps reduce that possibility.
Bowens disease is not contagious, and it is not the same as melanoma. It can occur on sun-exposed skin, such as the lower legs, head, neck, hands, and forearms, but it may also develop in areas that receive little sun exposure. When it affects the genital or anal area, it may be described using site-specific terms and requires careful specialist assessment.
How Bowens Disease May Look and Feel
Bowens disease often starts as a slowly enlarging patch that remains in the same place for months or longer. The patch may be red, pink, brown, or skin-colored. It commonly has a dry, rough, crusted, or scaly surface and may resemble eczema, psoriasis, a fungal rash, or a healing injury.
The edges are sometimes sharply defined, sometimes not. Some patches are flat, others sit slightly raised. Most do not hurt, which is exactly why they get overlooked. Now and then one will itch, feel tender, bleed if you rub it, or scab over and then scab again.
On darker skin tones, the area may appear darker than surrounding skin rather than red. A persistent patch that changes in appearance, becomes thicker, develops an ulcer, or does not respond to usual skin care deserves medical review. Photographs taken over time can be helpful for documenting change, but they cannot replace an in-person skin examination.
- A scaly patch that persists despite moisturizers or prescribed rash treatments
- A slowly growing red, brown, or pink area with a rough surface
- Repeated crusting, minor bleeding, tenderness, or itching in one spot
- A non-healing lesion, especially on previously sun-damaged skin
Why Bowens Disease Develops and Who Is at Risk

Long-term exposure to ultraviolet, or UV, radiation is an important risk factor for Bowens disease. UV radiation comes mainly from sunlight and can also come from tanning beds. It can damage skin-cell DNA over time, especially in areas that have received years of intermittent or regular sun exposure.
Risk climbs with age, simply because UV damage and other cellular changes pile up over the years. If you have fair skin, light-colored eyes, freckles, a history of frequent sunburns, or you have spent a lot of your life outdoors, you may be more likely to develop sun-related skin changes. But Bowens disease turns up in people of every skin tone, so never dismiss a patch based on how it looks alone.
Other factors may include a weakened immune system due to certain medicines or medical conditions, prior radiation treatment, chronic wounds or inflammation, and past exposure to arsenic. Some lesions in genital or anal skin are associated with certain types of human papillomavirus, or HPV. Having one lesion also means it is sensible to have the rest of the skin checked regularly, as sun damage can affect multiple areas.
How the Diagnosis Is Confirmed
A dermatologist or another qualified clinician will begin by asking about the lesion, including when it appeared, whether it has changed, and any symptoms such as bleeding or itching. They will examine the area and may assess other parts of the skin for signs of sun damage or additional suspicious lesions.
Although the appearance can suggest Bowens disease, many skin conditions look similar. For this reason, diagnosis is usually confirmed with a skin biopsy. After numbing the skin with local anesthetic, the clinician removes a small sample or the entire lesion and sends it to a laboratory for examination under a microscope.
The biopsy tells us whether this is Bowens disease or something else: an inflammatory condition, a benign growth, a fungal infection, or invasive squamous cell carcinoma. It also shapes the treatment plan. The location, size, thickness, borders, number of lesions, immune status, and any previous treatment all influence which approach is most appropriate.
Treatment Options for Bowens Disease
Treatment is individualized. The best option depends on where the lesion is located, how large it is, whether it has been treated before, and the person’s general health, skin-healing ability, and preferences. In some situations, a clinician may recommend a short period of monitoring before treatment planning, but confirmed lesions are commonly treated because of the possibility of progression.
Surgical excision removes the lesion along with a small margin of surrounding skin and allows the tissue to be examined. This approach may be especially useful when the diagnosis is uncertain, the area is thickened, the borders are unclear, or there is concern for invasion. Curettage and cautery, in which the lesion is scraped and treated with heat or electricity, may be suitable for selected superficial lesions.
Non-surgical choices include cryotherapy, which destroys abnormal cells by freezing them; topical medicines such as 5-fluorouracil or imiquimod; and photodynamic therapy, which combines a light-sensitive treatment with a specific light source. These methods can be useful for superficial or larger areas and may avoid surgery in some locations. They can cause temporary redness, soreness, crusting, or inflammation as the skin responds to treatment.
Radiotherapy is used less often but may be considered when surgery is not suitable or for selected difficult-to-treat areas. Whatever method is chosen, follow-up is important to confirm healing and identify recurrence or new lesions early. A specialist may also recommend regular full-skin examinations for people with significant sun damage or other risk factors.
Protecting the Skin and Supporting Follow-Up
Sun protection cannot reverse all existing sun damage, but it can help reduce further UV injury and lower the risk of additional skin cancers. Protection is useful throughout the year, including on cloudy days, because UV radiation can still reach the skin. It is particularly important for people who have had Bowens disease or other types of skin cancer.
Practical measures include seeking shade when possible, wearing a broad-brimmed hat and protective clothing, avoiding tanning beds, and using a broad-spectrum sunscreen with SPF 30 or higher on exposed skin. Sunscreen should be applied generously and reapplied according to the product instructions, especially after swimming, sweating, or towel drying.
Checking your own skin regularly is how most people spot a changing patch, sore, or growth. Look at the obvious sun-exposed areas, but also the scalp, the backs of your legs, your feet, and your nails. A mirror or a trusted family member can help check hard-to-see areas. Any persistent or changing lesion should be assessed rather than repeatedly treated at home as a presumed rash.
When to Seek Medical Care
Book an appointment if a skin patch has stuck around longer than several weeks, particularly if it is rough, scaly, crusted, growing, bleeding, or healing and breaking down again. Prompt review is also advisable for new changes in a previous scar, chronic wound, or area of skin that has received radiation treatment.
Do not wait if a lesion turns painful, grows quickly, opens into a sore, or develops a firm raised area. And if you have reduced immunity, a personal history of skin cancer, or a lot of sun-damaged spots, ask sooner rather than later.
Bowens disease is often manageable with outpatient treatment, and early evaluation can make treatment more straightforward. Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals diagnose and treat skin conditions, including Bowens disease, for international patients. A dermatologist can explain the diagnosis, discuss suitable options, and create an appropriate follow-up plan.
Frequently asked questions
01Is Bowens disease cancer?
Bowens disease is an early form of squamous cell skin cancer called squamous cell carcinoma in situ. The abnormal cells are confined to the outermost layer of skin and have not invaded deeper tissue. It is generally very treatable, but medical assessment and treatment are important.
02Can Bowens disease go away on its own?
A persistent lesion should not be expected to resolve on its own. Some skin conditions that resemble Bowens disease may improve, but a confirmed diagnosis usually needs treatment or specialist-directed monitoring. This helps reduce the chance of progression to invasive squamous cell carcinoma.
03What does Bowens disease look like?
It often looks like a persistent dry, scaly, red, pink, brown, or skin-colored patch. It may be flat or slightly raised and can resemble eczema, psoriasis, or a fungal infection. Its appearance varies between individuals and across skin tones, so a biopsy may be needed for confirmation.
04Is Bowens disease caused by sun exposure?
Long-term UV exposure is a major risk factor, particularly for lesions on sun-exposed skin. However, Bowens disease may also occur in areas with little sun exposure. Other possible factors include immune suppression, previous radiation, chronic skin injury, and certain HPV-related changes in genital or anal skin.
05How is Bowens disease treated?
Treatment can include surgical removal, curettage and cautery, freezing with cryotherapy, topical prescription medicines, or photodynamic therapy. The choice depends on the lesion’s site, size, features, and the individual’s medical circumstances. A clinician will discuss expected healing, possible side effects, and follow-up needs.
06Can Bowens disease come back after treatment?
A treated lesion can sometimes recur, and people who have had Bowens disease may also develop new lesions elsewhere. Follow-up appointments and regular skin checks help detect changes early. Ongoing sun protection is an important part of reducing additional UV-related skin damage.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Oncology care in Turkey — second opinion and treatment plan
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


