

Which Surgery Is Best for an Umbilical Hernia?
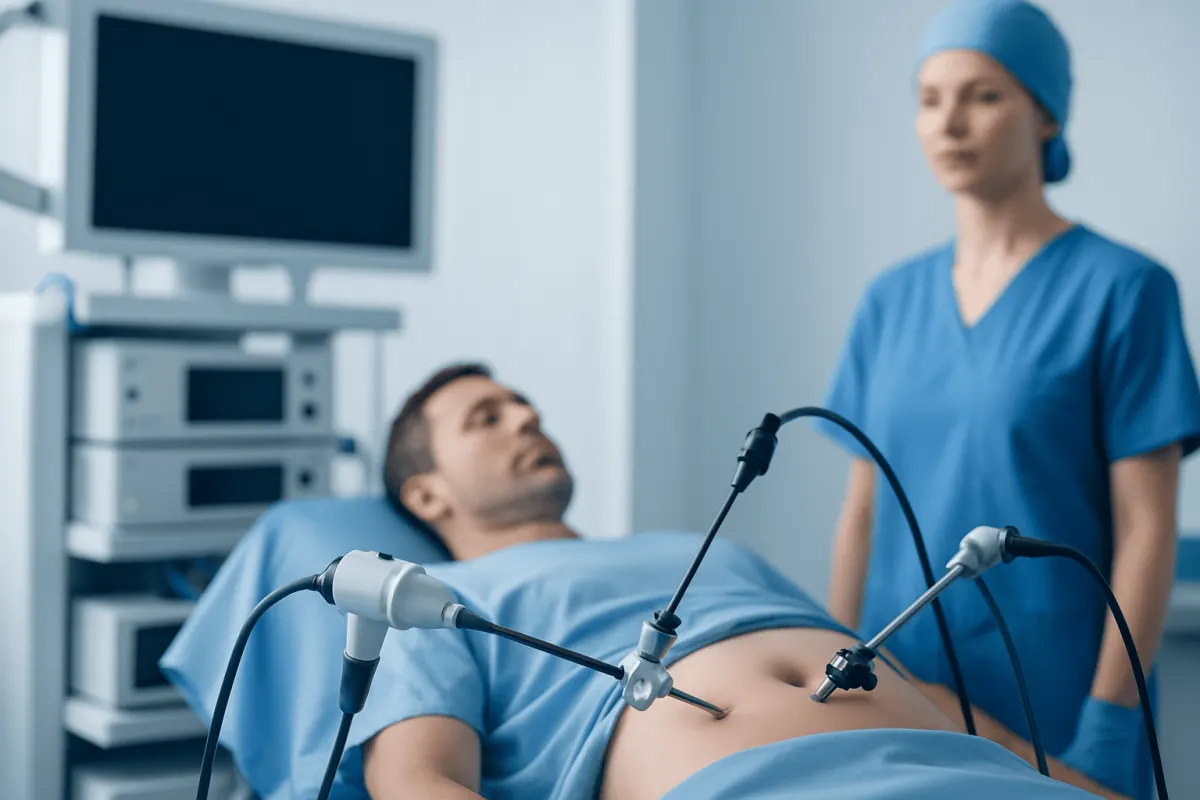
The best surgery for an umbilical hernia is individualized: a small, uncomplicated hernia may be repaired through a short open incision, while laparoscopic or robotic repair can be useful for larger, recurrent, or more complex hernias. A general surgeon assesses the hernia’s size, contents, symptoms, previous operations, and the person’s overall health to recommend the safest approach.
Which surgery is best for umbilical hernia?
Which surgery is best for umbilical hernia? There is no single best operation for every person. For a small, first-time hernia, an open repair through one incision is often effective. For a larger hernia, a hernia that has returned after surgery, or a person with factors that make wound complications more likely, minimally invasive laparoscopic repair may offer advantages.
Umbilical hernia repair closes a weak opening in the abdominal wall near the belly button. The surgeon may use stitches alone for a very small defect, or reinforce the repair with surgical mesh. Mesh is a sterile material designed to support the abdominal wall; it is frequently considered in adult repairs because it can lower the likelihood that the hernia returns.
The decision is made with a surgeon for umbilical hernia repair after an examination and discussion of symptoms, hernia size, body weight, smoking status, medical conditions, prior abdominal surgery, pregnancy plans, and personal preferences. The aim is a durable repair with an approach suited to the individual rather than a one-size-fits-all procedure.
Understanding an umbilical hernia and its seriousness
An umbilical hernia occurs when fatty tissue or part of the intestine pushes through a weak area in the abdominal wall around the navel. It may look like a soft bulge that becomes more noticeable with coughing, lifting, straining, or standing. In adults, it does not usually close on its own.
How serious is a hernia in the belly button? Many are not immediately dangerous, especially when the bulge is soft, can be gently pushed back while lying down, and causes little discomfort. However, hernias can slowly enlarge and may become painful or harder to reduce. Rarely, tissue can become trapped in the opening, which can block the bowel or affect its blood supply.
For this reason, a new or changing belly-button bulge should be evaluated by a qualified clinician. A planned discussion with a general surgeon can help clarify whether observation or elective repair is more appropriate. Information about the condition is also available through umbilical hernia guidance.
Can I live a normal life with an umbilical hernia? Some adults with a small, painless, reducible hernia can continue usual daily activities while monitoring it with their doctor. They should avoid activities that consistently cause pain or forceful straining. Living with a hernia is not necessarily unsafe in the short term, but it requires awareness of symptom changes and periodic medical review.
Surgery options for umbilical hernia: open or laparoscopic
When people ask, which surgery is best for umbilical hernia: open or laparoscopic?, the answer depends mainly on the hernia and the person having surgery. Both are established methods. The best choice balances repair strength, recovery needs, anesthesia considerations, surgical history, and the likelihood of complications.
Open umbilical hernia repair uses an incision near or within the belly button. The surgeon returns the hernia contents to the abdomen, closes the defect with sutures, and may place mesh to reinforce the area. It is often suitable for small to moderate primary hernias and can be a straightforward option with a single incision.
Laparoscopic repair uses a camera and instruments inserted through several small abdominal incisions. The surgeon repairs the defect from inside the abdominal wall and generally uses mesh. This approach may be helpful for larger or recurrent hernias, or when minimizing a larger incision is important. Robotic-assisted repair is another minimally invasive technique used in selected cases, but it is not automatically better than conventional laparoscopic or open surgery.
Mesh is not required for every repair. For very small defects, stitches alone may be reasonable; for larger defects, mesh often provides more durable reinforcement. The surgeon explains the planned mesh position, expected benefits, and possible mesh-related concerns in the context of the individual repair.
Who is a candidate and what happens during surgery?
A surgeon considers repair when an umbilical hernia causes pain, enlarges, limits activity, cannot be reduced, or has features that make complications more concerning. Repair may also be chosen by people with few symptoms who want to prevent future enlargement or avoid the uncertainty of monitoring. Elective surgery is generally safer and more predictable than emergency surgery for a trapped hernia.
Which doctor is best for umbilical hernia? A board-certified general surgeon with experience in abdominal wall and hernia repair is usually the appropriate specialist. Complex, large, recurrent, or incisional hernias may benefit from assessment by a surgeon with particular expertise in complex abdominal wall reconstruction.
Before surgery, the team reviews medications, allergies, medical history, and factors that can affect healing. Smoking cessation, diabetes management, nutrition support, and weight management where appropriate can reduce risks. The clinician may request blood tests or imaging if the diagnosis is uncertain, the hernia is large, or another abdominal condition needs assessment.
On the day of surgery, the person receives anesthesia, the skin is cleaned, and the surgeon makes the planned incision or small keyhole openings. The hernia contents are carefully returned to the abdomen, the weakened opening is closed and, when indicated, reinforced with mesh. The incisions are then closed and covered. Many uncomplicated repairs are performed as day surgery, though some people need overnight observation.
Anesthesia, benefits, risks, and recovery timeline
Which anesthesia is better for umbilical hernia surgery? General anesthesia is usually required for laparoscopic and robotic repair. Some small open repairs may be possible with local anesthesia and sedation, regional anesthesia, or general anesthesia. No option is universally better; the anesthesiologist and surgeon select the approach based on the operation, medical history, comfort, and safety needs.
Is umbilical hernia surgery safe? Planned repair is commonly performed and is generally safe when an appropriate surgical approach and anesthesia plan are used. Nevertheless, every operation has potential risks, including bruising, bleeding, wound infection, fluid collection, ongoing pain or numbness, injury to nearby structures, anesthesia reactions, blood clots, and recurrence. Mesh-related complications are uncommon but can include infection, discomfort, or the need for further treatment.
Recovery varies with the repair type, hernia size, and individual health. Walking is usually encouraged soon after surgery, while soreness and fatigue are common for the first several days. Desk-based work may be possible within days to a couple of weeks for some people, whereas heavy lifting, strenuous exercise, and physically demanding work often need to wait several weeks or until the surgeon confirms that healing is adequate.
Is umbilical hernia surgery a major surgery? Most small, planned repairs are not considered major abdominal operations and are often completed as outpatient procedures. However, a large, recurrent, incarcerated, or emergency hernia repair can be more extensive and may involve a longer hospital stay and recovery. Following the surgeon’s activity, wound-care, and follow-up instructions supports safe healing.
Is it worth fixing an umbilical hernia?
Is it worth fixing an umbilical hernia? Repair may be worthwhile when the hernia is painful, growing, affects daily life, is difficult to push back, or creates concern about future complications. Elective repair can relieve symptoms and restore the strength of the abdominal wall, although it cannot guarantee that a hernia will never recur.
For a small, painless hernia, watchful waiting may be a reasonable choice for selected adults after a clinical assessment. This means monitoring symptoms and discussing changes promptly rather than ignoring the hernia. The advantages of avoiding or delaying surgery should be weighed against the chance of enlargement, discomfort, or needing unplanned treatment later.
During shared decision-making, the surgeon should explain the expected benefit of repair, the likelihood of recurrence, whether mesh is recommended, the recovery restrictions, and the alternatives. A person should feel comfortable asking why one technique is being suggested and whether another approach is reasonable for their situation.
Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals assess and treat umbilical hernias for international patients, with the repair plan based on clinical evaluation and individual needs. Details about hernia surgery options can support an informed conversation with a qualified surgeon.
When to seek medical care
Arrange a non-urgent medical appointment for a new bulge at the belly button, persistent tenderness, a hernia that is increasing in size, or symptoms that interfere with work, exercise, or daily activities. A clinical examination is often enough to diagnose an umbilical hernia, although imaging may occasionally be helpful.
Seek urgent medical care if the bulge becomes suddenly painful, firm, discolored, or cannot be pushed back when it previously could. Urgent assessment is also important for nausea or vomiting, fever, increasing abdominal swelling, inability to pass stool or gas, or severe, worsening abdominal pain. These symptoms may indicate a trapped or obstructed hernia and should not be managed at home.
Until reviewed, people should avoid forcefully trying to push in a painful hernia and should not delay assessment because symptoms temporarily ease. Prompt evaluation allows clinicians to identify complications early and discuss the safest next steps.
Frequently asked questions
01What is the best surgery for a small umbilical hernia?
For a small primary umbilical hernia, open repair through an incision near the belly button is often a suitable option. The defect may be closed with stitches alone or reinforced with mesh, depending on its size and the person’s recurrence risk. A general surgeon can recommend the most appropriate technique after examination.
02Is laparoscopic umbilical hernia surgery better than open surgery?
Laparoscopic surgery is not always better, but it can be useful for larger, recurrent, or more complex hernias. Open repair is often effective for smaller hernias and may involve one incision rather than several small ones. The choice should reflect the hernia characteristics, prior surgery, health factors, and surgeon expertise.
03How long does recovery take after umbilical hernia surgery?
Many people can walk on the day of surgery and resume light activity within a few days, depending on pain control and the procedure performed. Return to desk work may take days to a couple of weeks, while heavy lifting and strenuous exercise are commonly restricted for longer. The operating surgeon provides the most appropriate timeline for the individual repair.
04Do all adult umbilical hernias need surgery?
No. A small, painless hernia that can be reduced may sometimes be monitored with medical advice. Surgery is more commonly recommended when symptoms develop, the hernia grows, it becomes difficult to reduce, or there is concern about complications. Adults should have an individualized discussion with a surgeon rather than assuming observation is suitable.
05Can an umbilical hernia come back after surgery?
Yes, recurrence is possible after any hernia repair. The chance is influenced by the size and type of hernia, repair technique, use of mesh when appropriate, wound healing, smoking, weight, chronic cough, constipation, and other conditions that increase abdominal pressure. Following recovery guidance and addressing modifiable risk factors may help reduce recurrence risk.
06What symptoms mean an umbilical hernia is an emergency?
Urgent symptoms include sudden severe or worsening pain, a hard or tender bulge that cannot be pushed back, skin color changes over the hernia, vomiting, fever, abdominal distension, or inability to pass stool or gas. These signs can suggest that tissue is trapped in the hernia. Immediate medical assessment is important.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Persistent digestive symptoms? Get evaluated in Turkey
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


