Vocal Feminization Surgery: Risks, Benefits, and Recovery
Vocal feminization surgery is a group of procedures designed to raise speaking pitch by changing the length, tension, or vibrating surface of the vocal folds. It can support gender affirmation for suitable patients, but voice therapy remains important because communication patterns beyond pitch also shape how a voice is perceived.
Overview: what vocal feminization surgery can do
Vocal feminization surgery, also called voice feminization surgery, is gender-affirming surgery that aims to increase vocal pitch. It is most often considered by transgender women and some nonbinary people whose voice remains lower than desired despite hormone treatment or voice therapy. For many people, having a voice that feels more aligned with their identity can improve comfort and confidence in everyday communication.
Pitch is determined largely by how quickly the vocal folds vibrate. Longer, thicker, or less tense vocal folds generally produce lower sounds, while shorter or tighter folds vibrate faster and produce higher sounds. Surgery changes one or more of these physical features. However, a voice is not perceived through pitch alone: resonance, intonation, loudness, word choice, and nonverbal communication also contribute.
For this reason, surgery is not a substitute for voice therapy, and it does not create one single “female” voice. The goal is an individual voice that is healthy, sustainable, and more consistent with the person’s preferences. A specialist team can help a patient understand what changes are realistic before deciding whether a procedure is appropriate.
How the procedure works
The most widely performed approach is Wendler glottoplasty. During this endoscopic procedure, the surgeon works through the mouth using a laryngoscope rather than making an incision on the outside of the neck. A portion of the front of the vocal folds is joined together, shortening the part of the folds that can vibrate. This typically increases the fundamental speaking pitch after healing.
Other surgical approaches may be considered in selected circumstances. Cricothyroid approximation increases tension on the vocal folds by adjusting structures in the larynx through a small neck incision. Procedures that reduce the mass of the vocal folds, such as laser-based techniques, may also be discussed. Each technique has different expected pitch changes, recovery requirements, and possible effects on vocal range and voice quality.
Most procedures are performed under general anesthesia. The choice of operation should be based on laryngeal examination findings, the patient’s baseline pitch and vocal demands, prior treatments, and the surgeon’s experience. A preoperative discussion should include the possibility that the final pitch and voice quality may differ from expectations.
Who may be a candidate

Potential candidates are adults who experience distress or practical difficulty because their voice does not align with their gender expression or personal goals. Many specialists recommend a trial of gender-affirming voice therapy first, when accessible. Therapy can safely help change pitch, resonance, intonation, and communication habits, and it may provide sufficient benefit without surgery for some people.
Before surgery, a laryngologist or ear, nose, and throat specialist usually performs a detailed voice assessment. This may include listening to speech, measuring pitch range, reviewing vocal demands at work or home, and examining the vocal folds with flexible laryngoscopy or videostroboscopy. These tests help identify inflammation, nodules, weakness, scarring, reflux-related changes, or other conditions that should be addressed first.
Good candidates are able to follow postoperative voice-rest instructions and attend follow-up and voice therapy appointments. Smoking or vaping, uncontrolled reflux, frequent shouting, and untreated chronic cough can interfere with healing. A clinician may recommend stopping nicotine use and managing these factors before an operation. Individual mental health support can also be valuable when it is desired by the patient, particularly while making a significant and personal treatment decision.
What happens before, during, and after surgery
Preparation begins with consultation, voice recordings, laryngeal examination, and a discussion of goals. The surgical team reviews medical conditions, medications, allergies, previous neck or airway surgery, and anesthesia considerations. Patients receive individual instructions about eating and drinking before anesthesia, medication adjustments, nicotine avoidance, and arranging transportation and support after the procedure.
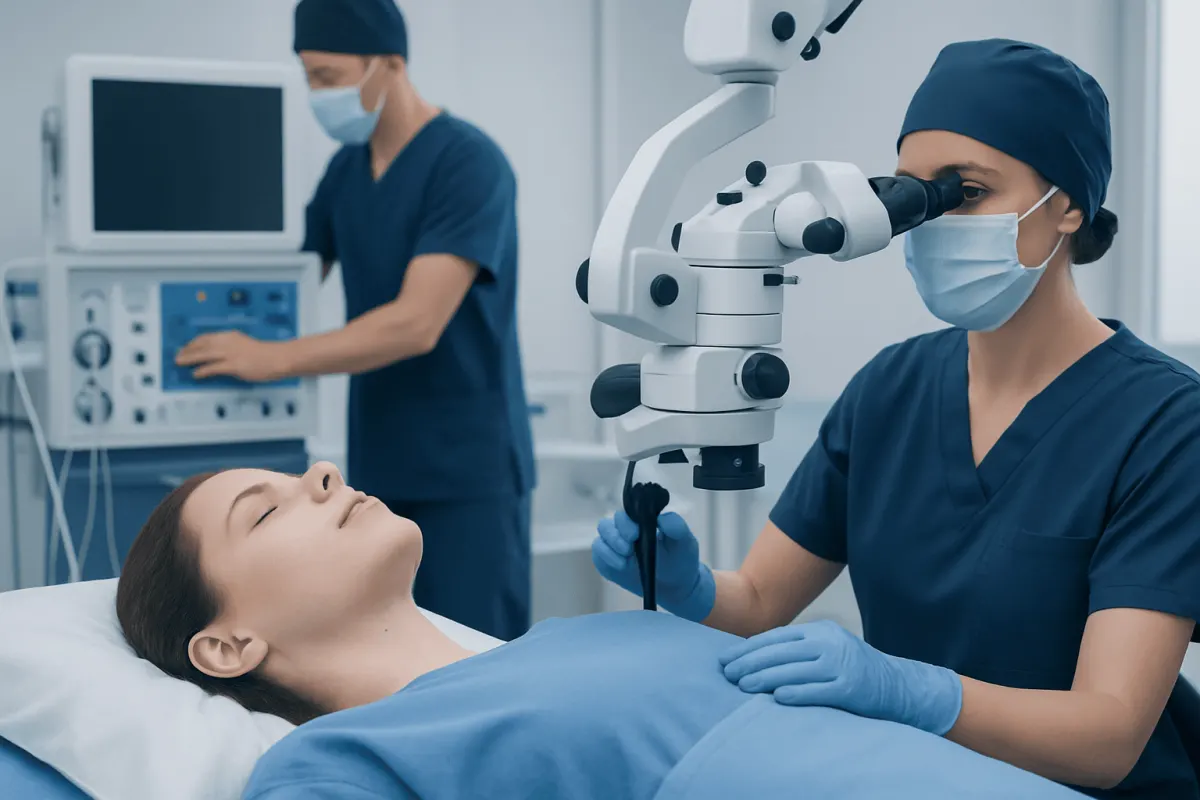
For endoscopic glottoplasty, the patient is asleep under general anesthesia. A laryngoscope is placed through the mouth to give the surgeon a view of the vocal folds. The surgeon prepares the front portion of the folds and joins the surfaces with sutures, with or without other methods used to support healing. No external neck scar is expected with this approach. The exact steps vary according to the technique and the patient’s anatomy.
After surgery, patients are monitored as they wake from anesthesia and may often return home the same day, depending on their health and the procedure performed. Mild throat discomfort, temporary hoarseness, coughing, and fatigue can occur. The clinical team provides specific instructions on pain relief, diet, activity, voice use, and emergency symptoms. Follow-up examinations allow the surgeon to check that healing is progressing as expected.
Recovery timeline and voice rehabilitation
Recovery requires patience because the vocal folds need time to heal before they can tolerate regular vibration. Complete voice rest is commonly prescribed for an initial period, often around one to two weeks, although the exact duration depends on the surgical technique and surgeon’s protocol. During this time, patients should not speak, whisper, sing, cough forcefully if avoidable, or clear the throat repeatedly. Whispering is not a safe alternative because it can still strain healing tissue.
After the first review, the care team may allow a gradual return to brief, gentle voice use. Voice therapy usually begins or resumes when the surgeon considers it safe. A speech-language therapist teaches efficient voice production, helps prevent strain, and supports changes in resonance, intonation, and speech habits. Hydration, reflux management when needed, avoiding smoke exposure, and limiting loud talking are important during this stage.
In the first weeks, the voice may sound weak, breathy, rough, unstable, or higher than expected. These changes do not necessarily predict the long-term result. Many people notice progressive improvement over several months as swelling decreases and coordinated voice use returns. Heavy voice use, singing, public speaking, and strenuous activities should be resumed only on the schedule advised by the treating clinician.
- First 1–2 weeks: prescribed voice rest and close attention to healing instructions.
- Following weeks: carefully graded voice use and follow-up laryngeal assessment.
- Following months: ongoing voice therapy and gradual stabilization of pitch, stamina, and quality.
Potential benefits, limitations, and risks
The main potential benefit of vocal feminization surgery is a higher habitual speaking pitch. Some patients feel less pressure to consciously maintain a higher voice and may experience greater ease in social, professional, or telephone conversations. Surgery can also reduce dysphoria related to voice for individuals who have not achieved their desired change through therapy alone.
Results are individual and cannot be guaranteed. Surgery does not directly alter all aspects of gendered voice perception, such as resonance or speaking patterns. It may also reduce access to lower notes, limit vocal range, or change singing ability. People who rely on a broad vocal range or high-intensity voice use for work should discuss these implications carefully with both a surgeon and voice therapist.
All surgery carries risks related to anesthesia, infection, bleeding, and healing. Procedure-specific concerns may include prolonged hoarseness, breathiness, vocal fatigue, stiffness or scarring, a rough voice quality, loss of volume, difficulty controlling pitch, and separation of the newly formed web after glottoplasty. Rarely, airway narrowing, breathing difficulty, swallowing concerns, or the need for revision treatment may occur. Choosing an experienced laryngeal surgeon and following voice-rest guidance can help reduce avoidable risks, but cannot remove them completely.
When to seek medical care
A person considering vocal feminization surgery should seek assessment from a qualified laryngologist or ENT specialist and a speech-language therapist with voice expertise. A professional evaluation is especially important before surgery if there is persistent hoarseness, pain when speaking, loss of voice, frequent throat clearing, breathing noise, difficulty swallowing, or a history of vocal fold problems.
After surgery, patients should contact their surgical team promptly for worsening throat pain, fever, significant bleeding, inability to swallow fluids, persistent vomiting, or a marked decline in voice after an initial improvement. Urgent medical care is needed for shortness of breath, noisy breathing, chest pain, swelling that affects breathing, or any symptom that feels severe or rapidly worsening.
Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals assess and treat voice conditions and provide coordinated care for international patients. A consultation can clarify whether voice therapy, surgery, or a combination of approaches is most suitable for a person’s health, goals, and daily vocal needs.
Frequently asked questions
01Does vocal feminization surgery permanently raise the voice?
The structural changes made during surgery are intended to produce a lasting increase in vocal pitch. However, the long-term outcome depends on healing, vocal habits, and postoperative rehabilitation. The voice may continue to mature and stabilize for several months after the operation.
02Can estrogen raise the voice after puberty?
Estrogen therapy generally does not substantially raise vocal pitch once testosterone-related laryngeal changes have occurred after puberty. This differs from testosterone therapy, which can lower pitch by thickening the vocal folds. Voice therapy and, for selected patients, surgery may be considered for pitch-related goals.
03Is voice therapy needed after vocal feminization surgery?
Voice therapy is commonly recommended before and after surgery. It supports safe vocal technique and addresses communication features that surgery does not directly change, including resonance, intonation, and speech patterns. It can also help a patient adapt to the healing voice without overstraining it.
04How long must a person avoid speaking after glottoplasty?
The required period of voice rest varies by surgeon and procedure, but complete voice rest is often advised for approximately one to two weeks. The patient should follow the individualized instructions provided by the surgical team. Speaking too early or too forcefully may affect healing.
05Will vocal feminization surgery affect singing?
It can affect singing, particularly access to lower notes, vocal range, power, and flexibility. The extent of change differs among individuals and procedures. Professional singers and people who sing regularly should discuss their needs in detail during preoperative assessment.
06Can vocal feminization surgery be reversed?
Reversal may be difficult and is not always possible because surgery intentionally changes vocal fold structure. Revision surgery can sometimes be considered for complications or an unsatisfactory result, but it carries additional uncertainty and risk. This is why careful assessment and informed consent are essential before treatment.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.