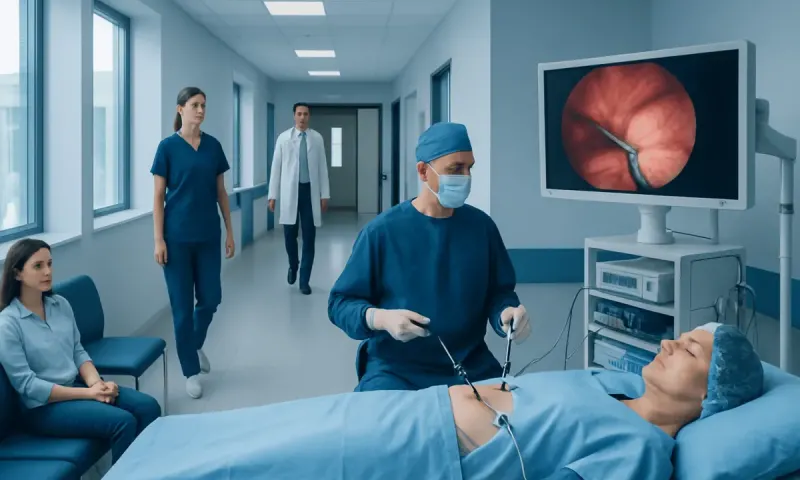
EGD Is an Upper Endoscopy, Not Open Surgery

You searched for “surgery EGD” and the word “surgery” probably worried you. Here’s the reassuring part: an EGD, short for esophagogastroduodenoscopy and often called an upper endoscopy, isn’t open surgery at all. A gastroenterologist uses a thin, flexible camera to look inside your upper digestive tract.
It can help pin down what’s behind your symptoms, take tissue samples, and in some cases treat bleeding or remove small growths — all without a single incision.
Surgery EGD: what it is and how it works
Surgery EGD is a commonly used search term for esophagogastroduodenoscopy, or EGD. Despite the word “surgery,” an EGD is usually a minimally invasive endoscopic procedure rather than an operation involving incisions. A gastroenterologist passes a narrow, flexible tube with a light and camera through the mouth to view the lining of the esophagus, stomach and duodenum, the first portion of the small intestine.
The procedure helps clinicians investigate swallowing difficulties, persistent upper abdominal discomfort, nausea, vomiting, unexplained anemia, gastrointestinal bleeding or abnormal imaging findings. It may also be used to monitor conditions such as inflammation, ulcers, Barrett’s esophagus or celiac disease. An EGD can sometimes provide treatment during the same session, including controlling bleeding, widening a narrowed area, removing certain small polyps or retrieving an object.
The endoscope sends images to a monitor, allowing close examination of the digestive tract lining. Small instruments can pass through the scope when necessary, so the doctor may take biopsies. A biopsy is a tiny tissue sample that is examined in a laboratory; it does not necessarily mean cancer is suspected.
Who may need an EGD and how to prepare
A doctor may recommend an EGD when symptoms continue, recur, affect eating or quality of life, or suggest a condition that needs direct assessment. It can also clarify the cause of upper gastrointestinal bleeding, such as black stools or vomiting blood, and may be used urgently in some hospital situations. The decision is based on symptoms, medical history, examination findings and other test results.
Before the procedure, the clinical team reviews medications, allergies, previous reactions to sedation, heart or lung conditions, pregnancy and bleeding risk. People taking blood thinners, diabetes medicines, weight-loss medicines or certain supplements may need individualized instructions. They should not stop prescribed medication on their own; the doctor who arranges the EGD will advise whether any changes are appropriate.
To make the examination safe and accurate, the stomach needs to be empty. Patients are typically asked not to eat for a specified period beforehand and may be given instructions about clear liquids. Exact fasting times vary, so the endoscopy unit’s instructions take priority. Arranging for a responsible adult to take the patient home is important if sedation will be used.
- Bring an up-to-date list of medicines and allergies.
- Tell the team about loose teeth, dentures, sleep apnea, or prior sedation problems.
- Follow fasting instructions exactly and ask in advance about essential morning medicines.
- Plan to avoid driving, alcohol and important decisions until the following day after sedation.
What happens during the EGD procedure?

At the endoscopy unit, staff confirm the patient’s information, consent, preparation and medical history. An intravenous line may be placed for sedation medicines, and monitoring equipment checks breathing, oxygen level, heart rate and blood pressure. A local throat spray may be used in some cases. Many people receive conscious or deep sedation, while the exact approach depends on their health, the planned procedure and local practice.
The patient usually lies on the left side and wears a mouth guard to protect the teeth and endoscope. Once comfortable and sedated if appropriate, the doctor carefully advances the scope through the mouth and into the upper digestive tract. A little air or carbon dioxide is puffed in to open up the area for a clearer view. That’s what leaves you feeling briefly bloated afterwards.
The examination itself often takes less than 30 minutes, though this varies if biopsies or treatment are needed. Biopsies are generally painless because the digestive tract lining does not sense tissue sampling in the same way as skin. If the doctor finds an ulcer, narrowing, bleeding point or other change, they may perform suitable endoscopic treatment or arrange further testing and specialist care.
An upper endoscopy works best when it’s planned properly, with assessment beforehand and follow-up afterwards. The point isn’t just to get pictures. It’s to read those pictures alongside your symptoms, blood tests and scans, and then decide what comes next.
What is recovery like after EGD?
Recovery after an EGD is usually brief. Patients rest in a recovery area while the effects of sedation lessen, often for around one to two hours. They may feel sleepy, less focused or unsteady for the remainder of the day. A mildly sore throat, hoarseness, gas or abdominal fullness can occur and generally improves within a day or two.
Once swallowing is safe and the clinical team agrees, patients can usually begin with sips of water and then return to food as advised. If a treatment was performed, such as dilation, removal of a lesion or control of bleeding, diet and activity instructions may be more specific. Follow the discharge plan you were given, not general advice you read somewhere.
How many days bed rest after endoscopy? Bed rest is not usually needed after a routine EGD. Most people can walk, use the bathroom and move around at home the same day, but should rest and avoid strenuous activity until they feel fully alert. Sedation—not the endoscopy itself—is the main reason to keep the day low-key.
What is recovery like after EGD? Most patients feel close to normal by the next day. However, fatigue can last longer in some people, especially after deeper sedation or a therapeutic procedure. Anyone with ongoing symptoms, complex health needs or a procedure-related intervention should ask their care team what recovery timeline applies to them.
Do you get endoscopy results immediately?
Do you get endoscopy results immediately? The doctor may share preliminary visual findings after the patient is awake enough to understand the discussion. For example, they may explain whether they saw inflammation, an ulcer, a narrowing or no obvious abnormality. It is helpful for the accompanying adult to listen as well, since sedation can affect memory for a short time.
Not all results are available on the day. If biopsies were taken, the samples go to a pathology laboratory for detailed examination. Results commonly take several days and sometimes longer, depending on the testing needed. The care team will explain how and when results will be communicated and whether a follow-up appointment is recommended.
An apparently normal EGD can still be useful because it rules out certain visible causes of symptoms. Conversely, a visible finding may need confirmation by biopsy or may lead to additional blood tests, imaging, medication changes or specialist review. The final interpretation should therefore combine the procedure report, pathology results and the patient’s overall clinical picture.
Benefits, risks and what not to do after an EGD
The main benefit of EGD is direct visualization of the upper digestive tract, with the ability to take biopsies and sometimes treat a problem during the same procedure. It can help avoid more invasive testing in selected situations and can lead to timely care for conditions such as ulcers, bleeding or narrowing. Like all procedures, however, it has limitations and potential risks.
Common short-lived effects include throat irritation, bloating and drowsiness after sedation. Less common but potentially serious complications include a reaction to sedative medicines, bleeding after a biopsy or treatment, aspiration, infection, or a tear (perforation) in the digestive tract. The likelihood depends on the person’s health and on whether a therapeutic intervention is performed; the clinician discusses relevant risks before consent.
What not to do after an EGD? After sedation, patients should not drive, operate machinery, drink alcohol, sign legal documents, make major decisions or stay alone if their discharge instructions say supervision is needed. They should avoid strenuous exercise for the rest of the day unless their clinician advises otherwise. Following any special diet, medication and activity instructions is particularly important after dilation, polyp removal or bleeding treatment.
If you’re unsure about a symptom or an instruction, call your care team — that’s what they’re there for. Your written procedure report and discharge sheet will remind you what was done and what happens next.
When to seek medical care
Urgent medical assessment is needed after an EGD for severe or worsening chest pain, severe abdominal pain, difficulty breathing, persistent vomiting, vomiting blood, black stools, fever, fainting, or a swollen and painful abdomen. These symptoms are uncommon, but they can indicate a complication that should not be managed at home.
A person should also contact the endoscopy team if a sore throat, bloating or nausea is not improving as expected, or if they cannot keep fluids down. Individuals who had a therapeutic procedure should use the specific warning signs and contact numbers included in their discharge information.
For non-urgent concerns such as recurrent upper abdominal symptoms, swallowing problems, ongoing reflux symptoms or questions about biopsy results, an appointment with a qualified clinician is appropriate. Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals can assess digestive symptoms and provide endoscopic care for international patients when indicated.
Frequently asked questions
01Is surgery EGD painful?
An EGD is generally not painful, particularly when sedation is used. Some people notice brief throat discomfort afterward or temporary bloating from the air used during the examination. The care team monitors comfort throughout the procedure.
02How long does a surgery EGD take?
A routine diagnostic EGD often takes less than 30 minutes. The overall visit is longer because it includes registration, preparation, sedation, recovery and discussion of discharge instructions. Treatments performed through the endoscope may extend the procedure time.
03Can you eat after an EGD?
Many people can drink fluids and eat after their swallowing has returned to normal and the clinical team has approved it. Starting with light food may feel more comfortable after sedation. Some procedures require special dietary guidance, so patients should follow their individual instructions.
04Why are biopsies taken during an EGD?
Biopsies can help identify inflammation, infection, celiac disease, precancerous changes or other microscopic conditions that may not be clear from appearance alone. Taking a biopsy is common and does not automatically mean a serious condition is suspected. Results are reviewed by a pathology laboratory.
05Can I return to work the day after an EGD?
Most people can return to usual work and activities the next day after an uncomplicated EGD. The day of the procedure should be reserved for recovery because sedatives can impair judgment and coordination. A longer break may be needed after certain treatments or if the person has ongoing symptoms.
06What should I do if I have a fever after an EGD?
A fever after EGD should be reported promptly to the endoscopy team or a healthcare professional, especially if it occurs with pain, vomiting, weakness or breathing symptoms. While serious complications are uncommon, timely assessment is important. Emergency care is appropriate for severe symptoms or rapid deterioration.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Persistent digestive symptoms? Get evaluated in Turkey
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.