

Otitis Media: Ear Infection Symptoms and Treatment in Children

Otitis media is an infection or inflammation of the middle ear, most often seen in babies and young children after a cold or upper respiratory infection. With proper assessment, pain relief, and selective use of antibiotics when needed, most children recover well.
Overview
Otitis media means inflammation or infection in the middle ear, the small air-filled space behind the eardrum. It is one of the most common reasons children visit a doctor, especially during the first years of life. The condition often develops after a cold, flu, or other upper respiratory infection, when fluid builds up behind the eardrum and germs can grow.
There are different forms of otitis media. Acute otitis media usually comes on suddenly and may cause ear pain, fever, and a bulging or inflamed eardrum. Otitis media with effusion means fluid remains in the middle ear without clear signs of active infection; it may cause muffled hearing but not always pain or fever. Recurrent otitis media refers to repeated episodes over time.
Although ear infections can be uncomfortable for children and worrying for parents, most improve with appropriate care. The main goals are to relieve pain, identify children who need antibiotics, monitor hearing when fluid persists, and prevent complications. A qualified healthcare professional can help determine the safest treatment plan for each child.
Symptoms in Children
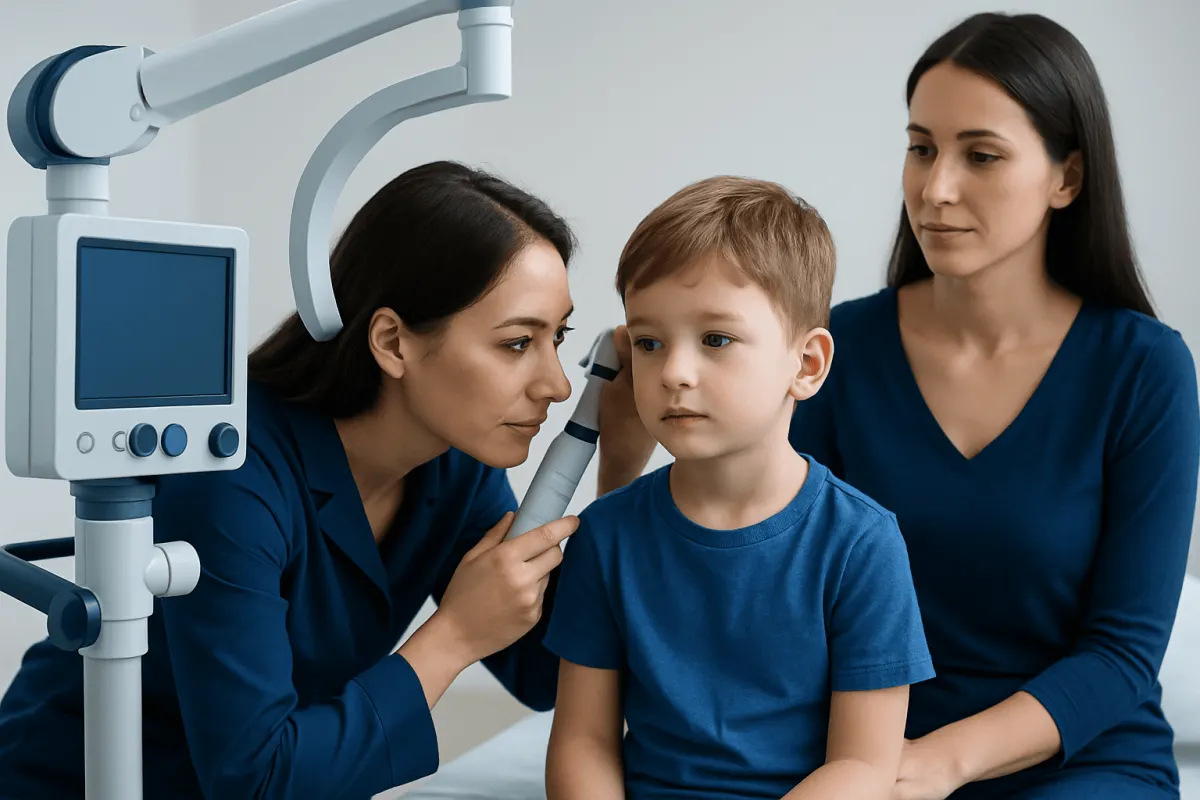
The most common symptom of acute otitis media is ear pain. Older children may say that the ear hurts, feels full, or sounds blocked. Younger children and babies may not be able to explain the pain, so they may cry more than usual, pull or rub the ear, have trouble sleeping, or become more irritable during feeding or lying down.
Other possible symptoms include fever, reduced appetite, headache, balance problems, and temporary hearing difficulty. Some children may have fluid draining from the ear, especially if pressure causes a small opening in the eardrum. Drainage can reduce pain because pressure is released, but it still needs medical assessment.
Symptoms can vary from mild to more noticeable. A child with otitis media with effusion may seem well overall but may ask for sounds to be repeated, turn the volume up, or have delayed speech clarity if fluid persists. Because temporary hearing changes can affect learning and communication, persistent or recurrent symptoms should be discussed with a doctor.
Causes and Risk Factors

Otitis media often begins when the eustachian tube, which connects the middle ear to the back of the nose, becomes swollen or blocked. This tube normally helps drain fluid and equalize pressure. In children, it is shorter, narrower, and more horizontal than in adults, making blockage more likely during colds, allergies, or nasal congestion.
Viruses commonly trigger the initial inflammation, and bacteria can sometimes grow in trapped middle ear fluid. Common respiratory germs can spread easily in childcare settings, schools, and households. Not every child with a cold develops an ear infection, but repeated respiratory infections increase the chance of fluid buildup.
Several factors may raise a child’s risk of otitis media:
- Age, especially between infancy and early school years
- Attendance at group childcare or frequent exposure to respiratory infections
- Exposure to tobacco smoke or indoor air irritants
- Family history of recurrent ear infections
- Allergies or chronic nasal congestion
- Feeding while lying flat in infancy
- Cleft palate or other conditions that affect eustachian tube function
Risk factors do not mean a child or parent has done anything wrong. They simply help doctors understand why infections may occur and what prevention steps may be useful.
Diagnosis
A doctor diagnoses otitis media by asking about symptoms and examining the ear with an otoscope. The doctor looks for signs such as redness, swelling, fluid behind the eardrum, reduced movement of the eardrum, or a bulging eardrum. The child’s age, fever, pain level, and general appearance also guide the diagnosis.
Sometimes a pneumatic otoscope or tympanometry is used to assess how well the eardrum moves. Reduced movement may suggest fluid in the middle ear. These tests are usually quick and noninvasive, although a young child may need reassurance and gentle positioning during the examination.
Hearing tests are not necessary for every single acute ear infection. However, they may be recommended when fluid lasts for several weeks, infections are recurrent, speech or learning concerns are present, or a child has risk factors for hearing problems. Imaging tests are rarely needed unless complications or unusual findings are suspected.
Treatment Options
Treatment depends on the child’s age, symptoms, examination findings, medical history, and whether one or both ears are affected. Pain control is an important first step because ear pain can be significant even when the infection is mild. Doctors may recommend age-appropriate pain relievers such as acetaminophen or ibuprofen, used according to professional guidance and product instructions. Aspirin should not be given to children unless specifically directed by a doctor.
Antibiotics are helpful for some children with acute bacterial otitis media, but they are not required for every case. Many mild infections improve on their own, especially when symptoms are not severe and the child can be closely monitored. A doctor may recommend observation for a short period, sometimes called watchful waiting, with clear instructions on when to start antibiotics or return for reassessment.
When antibiotics are prescribed, it is important to use them exactly as directed and complete the course unless the doctor advises otherwise. Parents should contact the healthcare provider if symptoms worsen, if fever or pain does not improve as expected, or if side effects occur. Over-the-counter cold medicines, decongestants, and antihistamines are not routinely recommended for treating otitis media in young children unless a doctor identifies another reason to use them.
Children with frequent infections, persistent middle ear fluid, or hearing concerns may be referred to an ear, nose, and throat specialist. In selected cases, tympanostomy tubes, also called ear tubes, may be recommended to help ventilate the middle ear and reduce fluid buildup. The decision is individualized and considers the child’s infection pattern, hearing, speech development, and overall health.
Prevention and Self-care
Not all ear infections can be prevented, but several steps can reduce risk. Good hand hygiene, avoiding close contact with people who are ill when possible, and teaching children to cover coughs can reduce respiratory infections that may lead to otitis media. Keeping children away from tobacco smoke is also important because smoke can irritate the airways and affect eustachian tube function.
Vaccination helps protect against infections that may contribute to ear disease. Parents should keep children up to date with routine immunizations, including pneumococcal and influenza vaccines as recommended by their healthcare provider. Breastfeeding, when possible, may also support infant immune protection.
For infants, feeding in a more upright position may help reduce fluid movement toward the middle ear. If a child uses a pacifier, parents can ask the pediatrician whether limiting use after infancy is appropriate. For children with allergies or chronic nasal symptoms, managing those conditions with medical guidance may reduce congestion and improve comfort.
At home, parents can support recovery by encouraging fluids, rest, and a calm environment. Warm compresses placed gently near the affected ear may soothe some children, but nothing should be inserted into the ear canal unless a doctor instructs it. Ear drops should be used only if recommended, especially when drainage or a possible eardrum opening is present.
When to See a Doctor
A child should be assessed by a doctor if ear pain is significant, fever is present, symptoms last more than a day, or the child is younger than 6 months. Medical advice is also needed if there is fluid, pus, or blood draining from the ear, if hearing seems reduced, or if infections keep coming back. Babies who are unusually fussy, feeding poorly, or difficult to comfort should be evaluated promptly.
Urgent care is recommended if a child develops swelling or redness behind the ear, the ear appears pushed forward, severe headache, stiff neck, persistent vomiting, confusion, unusual drowsiness, or weakness of the face. These signs are uncommon but require timely medical assessment. Parents should also seek help if a child’s condition worsens despite treatment or if they are concerned about the child’s breathing, hydration, or alertness.
For families seeking care away from home, it can be helpful to choose a center with pediatric, ENT, audiology, and imaging services when needed. Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals diagnose and treat ear infections and related conditions for international patients. Families should always follow the advice of the clinician who examines the child and understands the full medical history.
Frequently asked questions
01Is otitis media contagious?
Otitis media itself is not usually described as contagious, but the colds and respiratory infections that often lead to it can spread from person to person. Good hand hygiene, covering coughs, and keeping children home when they are unwell can help reduce transmission.
02Does every child with an ear infection need antibiotics?
No. Some mild ear infections improve without antibiotics, especially when the child is otherwise well and can be monitored closely. A doctor decides based on age, symptom severity, examination findings, and medical history.
03How long does ear pain from otitis media last?
Ear pain often improves within a few days with appropriate pain relief and monitoring, but the exact timing varies. Fluid behind the eardrum can remain for several weeks after the infection improves, and this may cause temporary muffled hearing.
04Can otitis media affect hearing?
Yes, middle ear fluid can temporarily reduce hearing by making it harder for sound to move through the eardrum and middle ear. Hearing usually returns as the fluid clears, but persistent fluid or recurrent infections should be evaluated.
05What are ear tubes and when are they considered?
Ear tubes are tiny tubes placed in the eardrum by an ENT specialist to help air enter the middle ear and fluid drain more easily. They may be considered for children with frequent infections, persistent fluid, hearing problems, or speech and learning concerns related to middle ear disease.
06Can parents use ear drops for a child’s ear infection?
Ear drops should be used only when recommended by a healthcare professional. This is especially important if there is drainage from the ear or a possible eardrum opening, because some drops may not be suitable in that situation.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


