

How the Types of Muscular Dystrophy Differ and Progress

Have you noticed a child falling more often than their friends, or found stairs harder to climb than they used to be? Muscle weakness that slowly gets worse is what brings many families to ask about muscular dystrophy. It is not one disease. It is a group of inherited conditions that gradually weaken muscles over time.
There is no universal cure — we should be honest about that. But modern diagnosis, rehabilitation, medicines, and supportive care can help many people maintain mobility, breathing, heart health, and quality of life.
What muscular dystrophy means
Muscular dystrophy is a group of inherited disorders that make muscles weaker over time because the proteins needed to keep muscle cells strong do not work properly. In many forms, the problem is present from birth at the genetic level, even if symptoms are not noticed until childhood, adolescence, or adulthood.
This term does not describe one single illness. Instead, it includes several types, such as Duchenne, Becker, limb-girdle, facioscapulohumeral, myotonic, congenital, and Emery-Dreifuss muscular dystrophy. Each type has its own typical pattern of muscle involvement, age of onset, and rate of progression.
Many people assume muscular dystrophy only affects the muscles you walk with. Not so. Some forms also involve the heart, breathing muscles, swallowing muscles, or joints — which is why you will often see a whole team of specialists involved rather than just one doctor.
And no, it is not true that nothing can be done. Muscular dystrophy is usually a lifelong genetic condition, but supportive treatment genuinely helps. Rehabilitation, respiratory monitoring, cardiac care, medications in selected cases, and mobility support all help people stay healthier and more independent for longer.
Types and how they differ
The different types of muscular dystrophy are mainly separated by the gene involved, the age symptoms begin, and which muscles are most affected. Duchenne muscular dystrophy often begins in early childhood and tends to progress more quickly, while Becker muscular dystrophy is usually milder and may appear later. Facioscapulohumeral muscular dystrophy commonly affects the face, shoulders, and upper arms, and myotonic dystrophy may cause both weakness and difficulty relaxing muscles after use.
Limb-girdle muscular dystrophy mainly affects the shoulders and hips, making climbing stairs, lifting the arms, or standing from a chair more difficult. Congenital muscular dystrophy is usually recognized in infancy or early childhood. Some forms are linked with spine curvature, joint contractures, or developmental concerns.
Symptoms overlap, so we cannot always tell the exact type just by looking. Neuron Disease May Run in Families" class="ahp-ilk">Genetic testing is now the key step — it confirms the diagnosis and helps us estimate possible heart, lung, or mobility risks over time.
People sometimes confuse muscular dystrophy with other nerve or muscle disorders. Some conditions can cause similar weakness but have different causes and treatments, so specialists may also consider other neuromuscular diseases during the evaluation.
Symptoms patients and families may notice
Symptoms depend on the type of muscular dystrophy and the person’s age. In children, early signs may include delayed walking, frequent falls, trouble running, walking on the toes, enlarged calf muscles, or using the hands to push up from the floor when standing. In teenagers or adults, the first changes may be shoulder weakness, facial weakness, difficulty climbing stairs, or increasing fatigue with physical activity.
Weakness is usually symmetrical in many forms, but not always. Some people first notice that they cannot raise their arms well, carry objects comfortably, or keep up with peers during exercise. Others develop muscle cramps, stiffness, or a waddling gait. In myotonic dystrophy, difficulty relaxing the hand after gripping can be a distinctive clue.
As the condition progresses, contractures may develop, meaning joints become tight and harder to move. Scoliosis, swallowing difficulty, breathing problems during sleep, or heart rhythm abnormalities may occur in certain forms. Keep an eye on these complications — they may need treatment even when the muscle weakness itself seems stable.
This condition touches more than muscles — emotional well-being, school, work, and family life can all feel the strain. Fatigue, reduced endurance, and loss of mobility often change routines gradually, so coming back for regular follow-up helps us spot needs early and support your day-to-day function.
Causes and risk factors
Muscular dystrophy is caused by inherited changes in genes that are important for muscle structure and repair. Depending on the type, the altered gene may be passed down in an X-linked, autosomal dominant, or autosomal recessive pattern. In some families, a person is the first known affected relative because the gene change occurred spontaneously.
The main risk factor is family history, but absence of a known family history does not rule it out. Some parents may carry a gene change without symptoms, while some forms can remain unrecognized for generations if symptoms are mild.
These conditions are not caused by exercise, infection, or ordinary wear and tear. Healthy lifestyle habits remain important for overall health, but they do not prevent a person from inheriting muscular dystrophy. Because the underlying cause is genetic, counseling may be recommended for families who want to understand inheritance, testing options, or future pregnancy planning.
Doctors may also evaluate related body systems because the same genetic problem can affect more than skeletal muscle. For example, some forms increase the risk of heart muscle disease or abnormal rhythms, which is why ongoing surveillance matters even when symptoms seem mainly orthopedic or mobility-related.
How diagnosis is confirmed
Diagnosis begins with a careful medical history and neurological examination. The doctor looks at the pattern of weakness, age of onset, walking and balance, joint flexibility, reflexes, and whether other family members have had similar symptoms. This clinical picture helps guide which tests are most useful.
Blood tests may show elevated creatine kinase, a marker that can rise when muscle fibers are damaged. Genetic testing is often the most important confirmatory step because it can identify the specific gene change responsible. In some cases, doctors may use electromyography, muscle MRI, or a muscle biopsy if the diagnosis remains unclear after initial testing.
Because some forms affect breathing or the heart, additional tests may include pulmonary function tests, sleep evaluation, electrocardiography, and echocardiography. These tests are not just for advanced disease. They give us a baseline and let us catch complications early.
Children and adults with progressive weakness may be assessed by neurology, rehabilitation medicine, cardiology, pulmonology, orthopedics, and genetics. When symptoms overlap with inherited nerve and muscle problems, structured evaluation in neurology care helps determine the exact diagnosis and the most appropriate follow-up plan.
Treatment options and long-term management
Treatment for muscular dystrophy is individualized and aims to preserve function, reduce complications, and support independence. There is no single treatment that suits every type, so the care plan depends on the genetic diagnosis, current symptoms, mobility, breathing, heart findings, and age. Needs change over time, so we reassess regularly.
Physical therapy and rehabilitation are central parts of care. Stretching, posture support, gentle strengthening within safe limits, and mobility training can help maintain range of motion and delay contractures. Depending on the situation, braces, standing devices, wheelchairs, or adaptive equipment may make daily life easier. Many patients benefit from coordinated physical therapy and rehabilitation to support movement, comfort, and participation in school or work.
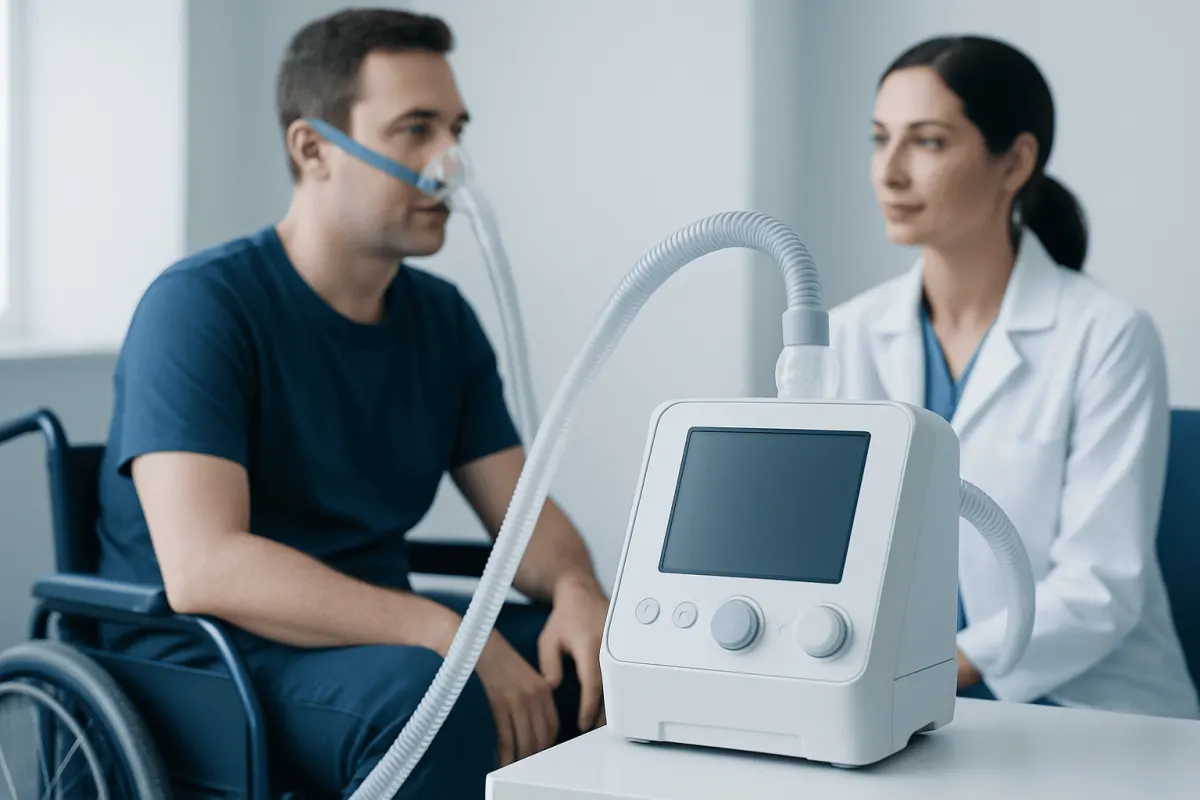
Medicines may be used in selected forms to slow progression, manage inflammation, support heart function, or treat symptoms such as pain and muscle stiffness. If breathing muscles are affected, cough support, breathing exercises, sleep monitoring, or noninvasive ventilation may be recommended. Swallowing assessment and nutritional support can also be important.
Orthopedic care may be needed for scoliosis, foot deformities, or contractures, and some patients require interventions to protect the spine or improve positioning. In advanced or selected situations, specialist input from orthopedics and traumatology and cardiology or pulmonary teams becomes part of routine care. Near the end of a long-term care pathway, some international patients seek evaluation at centers such as Acıbadem Health Point, where multidisciplinary specialists in JCI-accredited hospitals assess neuromuscular conditions and coordinate treatment planning.
Living well with muscular dystrophy
Self-care does not replace medical treatment, but it can improve comfort, safety, and daily function. A balanced diet, adequate hydration, regular follow-up, vaccinations as advised, and planned activity within personal limits all support overall health. Avoiding long periods of immobility can help reduce stiffness, although strenuous unsupervised exercise may not be appropriate for everyone.
Home and school adaptations are often helpful. Examples include handrails, accessible seating, lightweight tools, mobility aids, and scheduled rest breaks. These practical changes can reduce fatigue and lower the risk of falls while preserving independence.
Emotional support matters as much as physical care. Living with a chronic progressive condition can affect self-image, family roles, education, and work. Counseling, patient advocacy groups, and rehabilitation teams can help individuals and caregivers adapt over time.
Regular checkups are especially important when symptoms seem stable, because heart and breathing changes may begin quietly. If recommended by the care team, follow-up with cardiology care or respiratory specialists can help detect complications early and guide supportive treatment.
When to seek medical care
Medical review is important if a child has delayed motor milestones, frequent falls, toe walking, difficulty getting up from the floor, or unusual trouble keeping up with peers physically. Adults should seek assessment for steadily worsening muscle weakness, difficulty climbing stairs, repeated tripping, or unexplained loss of muscle bulk.
Prompt medical attention is also needed if muscular dystrophy is already diagnosed and new symptoms appear, such as shortness of breath, morning headaches, poor sleep, chest pain, palpitations, fainting, choking, or rapid decline in walking ability. These may suggest complications involving breathing, swallowing, or the heart.
Families with a known history of muscular dystrophy may benefit from early consultation even before symptoms are obvious. Genetic counseling can help clarify inheritance patterns, testing choices, and monitoring needs for relatives.
Many conditions can mimic muscular dystrophy, so if weakness persists, see a qualified doctor rather than relying on what you read online. Early diagnosis will not change the genetic cause — but it usually opens the door sooner to the monitoring, rehabilitation, and supportive therapies that protect your long-term health.
Frequently asked questions
01Is muscular dystrophy curable?
Muscular dystrophy is generally a lifelong genetic condition, so there is not one universal cure for all types. However, many treatments can help slow complications, maintain function, and support breathing, heart health, and mobility.
02What is usually the first sign of muscular dystrophy?
The first sign depends on the type and the person’s age. In children, common early clues include delayed walking, frequent falls, or difficulty running and climbing stairs. In adults, gradual shoulder, facial, or hip weakness may be noticed first.
03Does muscular dystrophy always get worse?
Most forms are progressive, meaning weakness tends to increase over time, but the speed and pattern vary widely. Some types progress slowly over many years, while others cause earlier and more noticeable disability.
04Can adults develop muscular dystrophy?
Yes. Although some types begin in childhood, others may first appear in adolescence or adulthood. Adult-onset forms can be milder at first and may be overlooked until weakness affects work, exercise, or daily tasks.
05How is muscular dystrophy diagnosed?
Doctors diagnose muscular dystrophy using a combination of medical history, physical examination, blood tests, and genetic testing. Additional tests such as heart evaluation, breathing tests, muscle imaging, or biopsy may be used when needed.
06Is exercise safe for someone with muscular dystrophy?
Activity is often helpful, but it should be individualized. Gentle, supervised exercise and stretching may support flexibility and daily function, while overly intense or unsupervised exercise can sometimes strain weakened muscles. A rehabilitation specialist can advise on a safe plan.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Joint and spine care in Turkey — expert assessment & treatment
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


