

Leg Ulcers Heal Best When the Underlying Cause Is Found
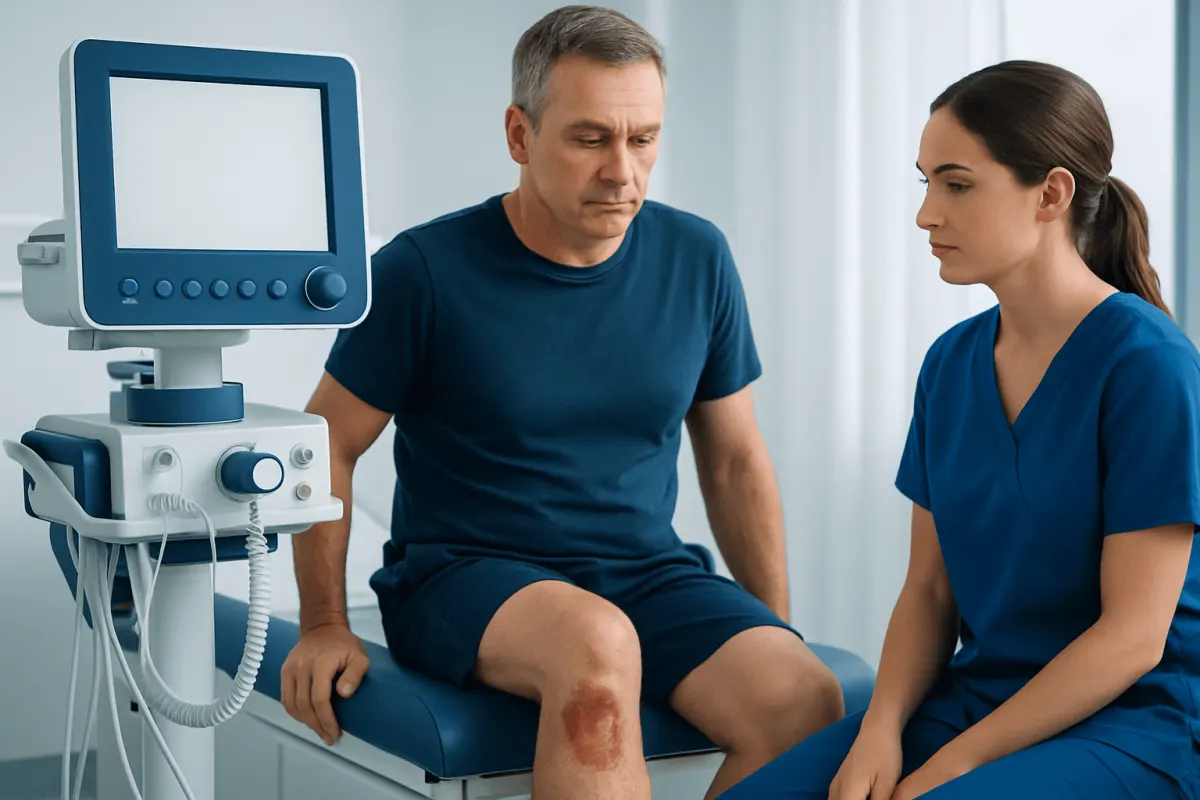
You knocked your ankle weeks ago, or maybe you didn’t knock it at all — and there’s still an open patch of skin that won’t close. That’s what we mean by a leg ulcer: an open wound on the lower leg or foot that doesn’t heal the way it should.
Most leg ulcers come back to a circulation problem, particularly in the veins. Getting them looked at early helps us find the cause, prevent complications and get healing moving.
Leg ulcers: what they are and why the cause matters
Leg ulcers are breaks in the skin that persist for weeks or fail to heal as expected. They most often occur between the knee and ankle, particularly around the inner ankle, although ulcers related to reduced arterial blood flow may affect the toes, feet or outer ankle. They may begin after a minor knock, scratch, swelling-related skin damage or no clearly remembered injury.
What you see on the surface is only part of the story. For a wound to close, you need enough blood flow, healthy veins, swelling kept under control, decent nutrition and protection from repeated pressure or knocks. That is why finding the cause matters just as much as picking the right dressing. With a plan built around you and regular follow-up, many ulcers heal — and are less likely to come back.
Leg ulcers are sometimes described as chronic wounds because they need ongoing care. They are not usually contagious. However, an open wound can become infected, and persistent ulcers should be assessed by a qualified clinician rather than treated with home remedies alone.
How different types of leg ulcers can look and feel
Venous leg ulcers are the most common type. They occur when leg veins have difficulty returning blood to the heart, allowing pressure and fluid to build up in the lower leg. These ulcers commonly develop near the inner ankle and may be shallow, irregularly shaped and moist. The surrounding skin can be swollen, itchy, brownish, hardened or affected by varicose veins.
Arterial leg ulcers result from reduced blood supply through the arteries, often due to Deep Vein Thrombosis: How to Tell the Difference" class="ahp-ilk">peripheral artery disease. They may occur on the toes, foot, heel or outer ankle and can look well-defined, deep or “punched out.” They may be painful, particularly at rest or at night, and the foot may feel cool, appear pale or bluish, or have reduced hair growth.
Other wounds may be related to diabetes, nerve damage, pressure, inflammatory skin disease, blood disorders, infection, cancer or injury. A person can also have both vein and artery disease. So looking at a wound is not enough to tell what kind it is, and compression or any other treatment should wait until your circulation has been checked.
Causes and factors that increase risk

Chronic venous insufficiency is a leading cause of leg ulcers. It may develop after deep vein thrombosis, longstanding varicose veins, obesity, limited mobility, pregnancy or increasing age. Persistent leg swelling and previous venous ulcers raise the likelihood of another ulcer developing.
Risk factors for arterial ulcers include smoking, diabetes, high blood pressure, high cholesterol, kidney disease and a history of cardiovascular disease. Diabetes can also delay healing by affecting blood vessels, sensation and immune function. Reduced sensation may mean that small injuries or pressure points are not noticed promptly.
Some factors do not directly cause an ulcer but can make healing slower. These include poor nutrition, anemia, dehydration, certain medicines, repeated trauma, poorly fitting footwear and difficulty reaching wound-care appointments. When we build a plan, we look at your general health, how well you get about and what help you have at home.
Assessment and diagnosis: looking beyond the wound
A clinician will ask when the wound began, whether it is painful, how it has changed and whether there is leg swelling, prior clotting, diabetes or circulation disease. They will examine the ulcer, surrounding skin, pulses, temperature, sensation and signs of infection. Measuring and photographing the wound over time may help monitor healing objectively.
A key test is the ankle-brachial index, which compares blood pressure measured at the ankle with that in the arm. It helps assess arterial blood flow and guides whether compression treatment is appropriate. Some people need toe-pressure testing, Doppler ultrasound of the veins or arteries, or imaging to look for blocked or leaking vessels.
Blood tests may be used to assess conditions that affect healing, such as diabetes, anemia, inflammation or kidney disease. A wound swab is not routinely needed for every ulcer, because bacteria can be present without causing infection. It is more useful when clinical signs suggest infection or when a wound is not progressing as expected. In selected persistent or unusual ulcers, a biopsy may be recommended to exclude inflammatory or malignant causes.
Treatment options: supporting healing and treating circulation
Effective leg ulcer care combines wound management with treatment of the underlying cause. A healthcare professional may clean the wound and remove non-viable tissue when appropriate, a process called debridement. Dressings are selected according to the amount of drainage, wound depth, surrounding skin condition and comfort; no single dressing is best for every ulcer.
For venous leg ulcers, compression bandages or stockings are commonly used to reduce swelling and improve venous return, provided arterial circulation is adequate. Elevating the legs when resting, walking regularly if able, and calf-muscle activity can also support circulation. Once an ulcer heals, ongoing compression is often advised to reduce recurrence.
Arterial ulcers require assessment by a vascular specialist because restoring blood flow may be necessary. Depending on the findings, treatment can include medication for cardiovascular risk reduction and procedures such as angioplasty, stenting or bypass surgery. Compression must be used cautiously or avoided in significant arterial disease. Diabetes-related wounds need pressure relief, glucose management, foot protection and specialist care.
Antibiotics are used when there is a clinical bacterial infection, not simply because an ulcer is open or has an odor. Pain should be assessed and treated, and care plans should account for sleep, mobility and emotional wellbeing. Acıbadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals diagnose and treat leg ulcers for international patients when coordinated wound and vascular care is needed.
Everyday care, prevention and common myths
People with a leg ulcer should follow their clinician’s plan for dressings, bathing and compression. Dressings should be kept clean and changed as advised. Please don’t put antiseptics, herbal preparations or unprescribed creams into the wound itself — they can irritate the tissue or work against the dressing you’ve been given.
Good skin care can lower the risk of injury. Moisturizing intact dry skin, checking the legs and feet daily, wearing well-fitting shoes and protecting the lower legs from knocks can help. For people with venous disease, maintaining a healthy weight where possible, avoiding long periods of sitting or standing, staying active within individual ability and wearing prescribed compression garments may be beneficial.
A common myth is that every leg ulcer needs compression. In fact, compression can be highly helpful for venous ulcers but may be harmful if severe arterial disease is present. Another myth is that a wound should be left open to “air out.” Modern wound care often uses suitable dressings to maintain a protected healing environment. The safest route is treatment aimed at your particular cause, guided by a clinician.
When to seek medical care
Any open wound on the leg that is not clearly healing within about two weeks should be reviewed by a healthcare professional. Earlier assessment is appropriate for people with diabetes, known artery disease, previous blood clots, reduced sensation, immune suppression or a history of leg ulcers. A new ulcer should not be self-managed with compression products unless circulation has been assessed.
Prompt medical attention is needed if pain suddenly increases, redness or swelling spreads, the wound produces pus, there is a fever or the person feels generally unwell. Urgent assessment is also important if the foot becomes cold, pale, blue or numb; if skin turns black; or if there is severe pain at rest. These symptoms can signal significant infection or impaired blood flow.
Even after healing, follow-up matters because leg ulcers can recur. A clinician can advise on long-term compression, vascular management, skin care, footwear and control of conditions such as diabetes or high blood pressure. Reporting early skin breakdown or renewed swelling often allows treatment before a larger ulcer develops.
Frequently asked questions
01Can leg ulcers heal on their own?
Small wounds may heal, but a leg ulcer that persists usually needs assessment because an underlying circulation or health problem may be preventing healing. Treating the cause, protecting the wound and monitoring progress offer the best chance of healing and reducing recurrence.
02Are leg ulcers always caused by varicose veins?
No. Vein problems are a common cause, but reduced arterial blood flow, diabetes, pressure, injury and inflammatory conditions can also cause leg ulcers. Some people have more than one contributing condition.
03Is a leg ulcer infected if it smells or leaks fluid?
Drainage and odor can occur in chronic wounds without a true infection. Infection is more likely when there is increasing redness, warmth, swelling, pain, pus, fever or a sudden decline in the wound. A clinician should assess these changes.
04Can compression stockings heal all leg ulcers?
Compression is an important treatment for many venous leg ulcers because it reduces swelling and supports blood return through the veins. It is not suitable for everyone, particularly people with significantly reduced arterial circulation, so testing is needed first.
05What foods help leg ulcers heal?
Adequate calories, protein, fluids, vitamins and minerals support normal wound healing. A balanced diet is generally recommended, while people with poor appetite, weight loss, diabetes or kidney disease may benefit from individualized nutritional advice from a healthcare professional.
06How long do leg ulcers take to heal?
Healing time varies widely according to the ulcer’s cause, size, depth, blood flow, infection status and whether swelling can be controlled. Some heal in weeks, while others require months of consistent treatment and follow-up. A wound that is not improving should be reassessed.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Persistent digestive symptoms? Get evaluated in Turkey
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


