Fuchs Dystrophy Treatment: How It Works, Results and What to Expect
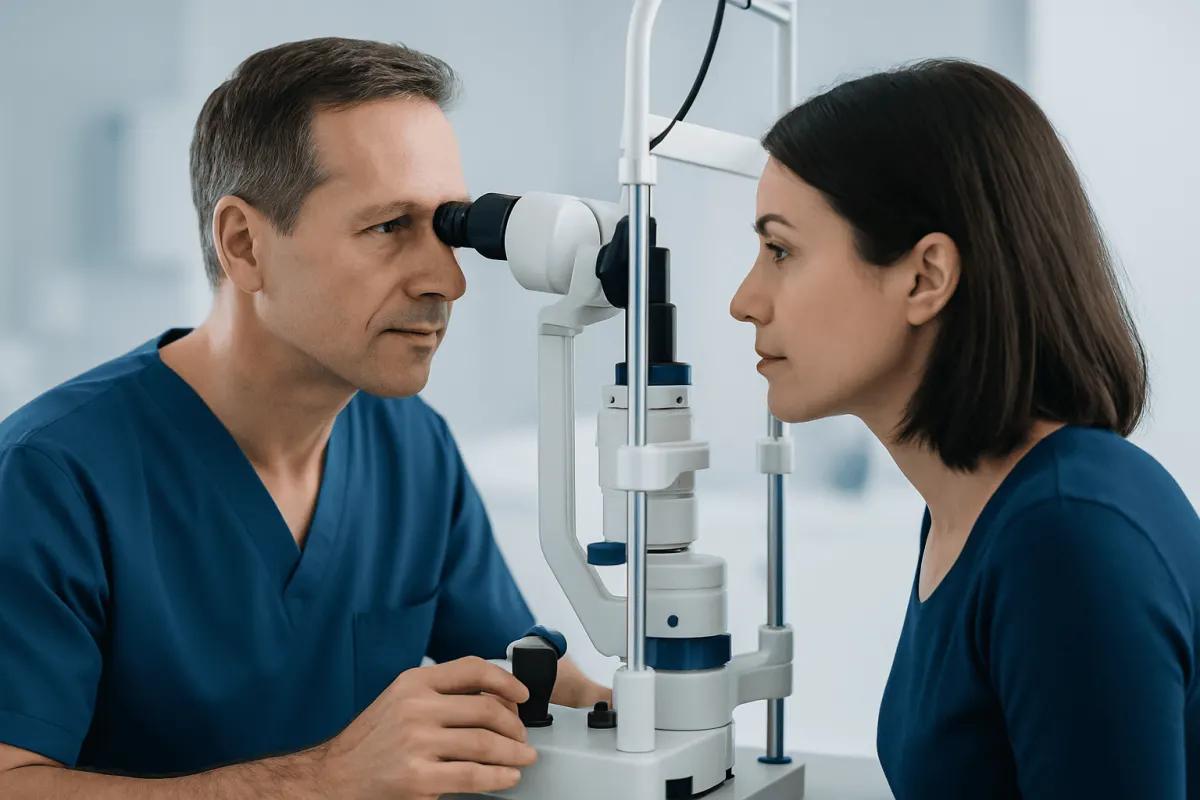
Fuchs dystrophy treatment is tailored to the amount of corneal swelling, vision change and effect on daily life. Early symptoms may be managed with monitoring and measures that reduce swelling, while advanced disease may benefit from endothelial corneal transplantation to replace the damaged inner cell layer.
Fuchs Dystrophy Treatment: How It Works
Fuchs dystrophy treatment aims to manage corneal swelling and improve vision when the disease affects everyday activities. In its early stages, an ophthalmologist may recommend regular monitoring, treatment for surface discomfort if present, and practical steps to lessen morning blur. When the cornea can no longer stay clear because too many endothelial cells have been lost, surgery may be the most effective option.
Fuchs endothelial corneal dystrophy is usually an inherited, slowly progressive condition affecting the endothelium, a thin layer of cells on the inside of the cornea. These cells pump fluid out of the cornea. As their function declines, fluid builds up, causing the cornea to swell and vision to become hazy, especially after waking. More information about the condition is available in Fuchs dystrophy overview.
Modern treatment often focuses on replacing only the unhealthy endothelial layer rather than the entire cornea. This approach is called endothelial keratoplasty. The two main procedures are Descemet membrane endothelial keratoplasty (DMEK), which uses an extremely thin donor tissue layer, and Descemet stripping automated endothelial keratoplasty (DSAEK), which uses a slightly thicker donor graft.
Symptoms, Progression and Treatment Decisions
Early Fuchs dystrophy may cause no noticeable symptoms. As corneal swelling increases, people may experience blurry or cloudy vision that is worse in the morning and improves later in the day. Glare, halos around lights, reduced contrast, difficulty reading, and changing glasses prescriptions can also occur. In later stages, persistent swelling may cause discomfort or painful surface blisters.
Treatment decisions are not based on visual acuity alone. The ophthalmologist will consider the pattern of symptoms, corneal thickness, endothelial cell health, corneal imaging findings, cataract status, and the person’s visual needs. For example, a person who drives at night or performs detailed visual work may be significantly affected by glare even if a standard eye-chart result seems relatively good.
Some people with mild disease do not need an operation for many years. Others develop symptoms that make surgery appropriate sooner. A cornea specialist can explain whether observation, symptom management, cataract surgery planning, or endothelial keratoplasty is the most suitable next step.
How long does it take for Fuchs to progress?
Fuchs dystrophy usually progresses gradually over years or decades, but the pace varies considerably between individuals and even between the two eyes. Some people remain mildly affected throughout life, while others develop meaningful corneal swelling earlier. Regular examinations are the most reliable way to monitor changes and guide treatment timing.
Does Fuchs always get worse?
Fuchs dystrophy is generally progressive because endothelial cells do not regenerate effectively. However, progression can be very slow, and not everyone develops severe symptoms or requires a corneal transplant. Vision may also fluctuate from day to day, particularly in earlier stages, so a worsening morning blur does not necessarily mean rapid permanent change.
Who May Be a Candidate for Treatment or Surgery?

People may be candidates for endothelial keratoplasty when corneal edema causes persistent blurred vision, glare, reduced quality of life, or painful corneal surface changes. Surgery may also be considered when corneal swelling makes cataract surgery less predictable or when a cataract and Fuchs dystrophy are both contributing to visual problems.
Before recommending surgery, the ophthalmologist reviews overall eye health. This includes the retina, optic nerve, eye pressure, tear film, lens clarity, and previous eye operations. Conditions such as glaucoma, retinal disease, significant dry eye, or prior complex eye surgery may influence which procedure is recommended and the expected visual outcome.
Cataracts and Fuchs dystrophy often coexist because both become more common with age. Depending on the cornea and lens findings, a specialist may advise cataract surgery first, endothelial keratoplasty first, or a combined procedure. The best sequence is individualized and should balance visual needs, surgical safety, and the likelihood of corneal recovery.
What Happens During Endothelial Keratoplasty?
Endothelial keratoplasty is usually performed as an outpatient procedure under local anesthesia with sedation or, in selected situations, general anesthesia. The surgeon makes very small corneal incisions and removes the diseased Descemet membrane and endothelium. A prepared donor endothelial graft is then placed inside the front chamber of the eye.
An air or gas bubble is used to gently press the graft against the back surface of the cornea while it adheres. In DMEK, the graft contains the donor Descemet membrane and endothelial cells only. In DSAEK, it includes a thin layer of supporting corneal tissue as well. The choice depends on the individual eye and the surgeon’s assessment.
After surgery, patients are usually asked to lie flat on their back for a specified period so the bubble can support graft attachment. Follow-up visits are arranged soon after surgery to check graft position, eye pressure, and early healing. For a fuller explanation of the procedure, see corneal transplant treatment.
In selected cases, another procedure called Descemet stripping only (DSO) may be considered. It removes a small central area of abnormal tissue without placing a donor graft, relying on healthy peripheral endothelial cells to migrate inward. It is appropriate only for carefully selected eyes and is not a replacement for endothelial keratoplasty in most advanced cases.
Recovery Timeline, Benefits and Risks
Recovery after endothelial keratoplasty is gradual. Vision may be blurred in the first days or weeks because of the healing cornea, the air or gas bubble, and temporary changes in the eye’s focusing system. With DMEK, many people notice meaningful improvement over weeks, although final visual recovery can take several months. Recovery may be slower if there is long-standing corneal swelling, cataract surgery at the same time, or another eye condition.
The primary benefit is restoration of a clearer cornea and better quality of vision when swelling from Fuchs dystrophy is the main cause of impairment. Many people experience less haze and glare after successful healing. A transplant cannot correct vision problems caused by unrelated conditions, such as macular degeneration, advanced glaucoma, or substantial refractive error, so expectations should be discussed before surgery.
Possible risks include graft detachment, which may require an additional air or gas injection; raised eye pressure; infection; bleeding; continued corneal swelling; and graft rejection or failure. Rejection is uncommon with modern endothelial procedures but can occur months or years later. New redness, pain, light sensitivity, or a sudden decline in vision should be assessed urgently.
Prescription eye drops are used after surgery to reduce inflammation and help prevent rejection. The ophthalmologist will advise when normal activities can resume and may recommend avoiding eye rubbing, swimming, heavy lifting, or certain sports during early healing. Attending all follow-up appointments is an important part of protecting the graft and vision.
How successful is a corneal transplant for Fuchs?
Endothelial keratoplasty is an established and generally effective treatment for visually significant Fuchs dystrophy. In an appropriately selected eye, it can clear corneal swelling and substantially improve vision. Individual results depend on graft health, surgical healing, adherence to follow-up, and whether other eye diseases limit vision.
How to Slow Down Fuchs Dystrophy and Protect Eye Comfort
There is currently no proven treatment that stops or reverses the inherited endothelial cell loss of Fuchs dystrophy. Regular care with an ophthalmologist is the most important way to identify changes early and choose treatment at the right time. Avoiding eye injury, using prescribed drops correctly, and managing related eye conditions can support overall eye health.
For mild morning blur, some people find that drying the eye surface with warm air from a hair dryer held at arm’s length and on a low, comfortable setting may temporarily reduce symptoms. This should only be used if a clinician recommends it, and the eye should never be exposed to hot air or held close to the dryer. Hypertonic saline drops or ointment may also be prescribed to reduce corneal surface swelling in some cases.
People should not use over-the-counter eye drops as a substitute for assessment when vision is changing. Contact lens use, new medications, and plans for cataract surgery should be discussed with the ophthalmologist, because corneal endothelial health may affect these decisions. General health measures, including not smoking and controlling diabetes where relevant, support eye health but do not cure Fuchs dystrophy.
How do you slow down Fuchs dystrophy?
Fuchs dystrophy cannot currently be reliably slowed with diet, supplements, or home remedies. The practical goal is to monitor the cornea, manage symptoms safely, and avoid unnecessary stress to the eye. A cornea specialist can advise on personalized follow-up and whether medical measures or surgery are appropriate.
When to Seek Medical Care
An eye examination should be arranged for persistent morning blur, increasing glare, halos, reduced night-driving confidence, or vision that no longer improves as the day goes on. People with a parent, sibling, or child diagnosed with Fuchs dystrophy may also wish to discuss screening during routine eye care, particularly if they have visual symptoms.
Urgent assessment is important for sudden vision loss, marked redness, severe pain, new light sensitivity, or discharge from the eye. These symptoms are not specific to Fuchs dystrophy and can signal another condition that needs prompt treatment. After a corneal transplant, they may also be warning signs of infection, pressure changes, or graft rejection.
Acıbadem Health Point’s multidisciplinary eye specialists and JCI-accredited hospitals assess and treat corneal conditions for international patients, including individualized planning for endothelial corneal transplantation. A qualified ophthalmologist can explain the likely benefits, limitations, and recovery expectations for each person’s eyes.
Frequently asked questions
01What is the best treatment for Fuchs dystrophy?
The best treatment depends on the stage of disease and how much corneal swelling affects vision. Mild symptoms may be monitored or managed with clinician-recommended measures, while persistent visual impairment from edema may be treated with endothelial keratoplasty. A cornea specialist can determine the most appropriate option after examining both the cornea and the rest of the eye.
02Can eye drops cure Fuchs dystrophy?
Eye drops cannot cure Fuchs dystrophy or replace lost endothelial cells. In some people, hypertonic saline drops or ointment may temporarily reduce corneal swelling and improve comfort or morning blur. They should be used only as advised by an eye-care professional.
03Is DMEK better than DSAEK for Fuchs dystrophy?
DMEK often offers faster visual recovery and excellent visual quality because the transplanted tissue is very thin. However, DSAEK may be preferred in certain eyes, including some with previous surgery or anatomical factors that make DMEK less suitable. The procedure choice should be individualized.
04Can cataract surgery make Fuchs dystrophy worse?
Cataract surgery can place additional stress on corneal endothelial cells, so it requires careful planning in people with Fuchs dystrophy. Some patients do well with cataract surgery alone, while others may need a combined or staged endothelial transplant. Preoperative corneal testing helps guide the decision.
05What are the signs of corneal transplant rejection?
Possible signs include increasing redness, pain, sensitivity to light, and worsening or hazy vision. These symptoms need prompt ophthalmology assessment because early treatment can be important. Not all changes mean rejection, but they should never be ignored after a transplant.
06Can Fuchs dystrophy affect only one eye?
Fuchs dystrophy usually affects both eyes, although one eye may become symptomatic earlier or progress more quickly. Differences between the eyes are common and do not necessarily indicate a separate disorder. Each eye is assessed and treated according to its own condition.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Explore treatments in Turkey — costs, top hospitals & a free quote
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.