

Dix-Hallpike Maneuver: Uses and Procedure
Key Takeaways
- The Dix Hallpike maneuver helps confirm whether brief, position-triggered vertigo is caused by BPPV.
- The test is performed in a clinical setting and may briefly bring on dizziness or eye movements called nystagmus.
- A positive result often supports treatment with repositioning maneuvers rather than long-term medication.
- Not all dizziness is BPPV, so a medical evaluation is important if symptoms are severe, new, or unusual.
- People traveling for care can usually return home soon after evaluation, with follow-up planned if symptoms persist.
The Dix Hallpike maneuver is a bedside test used to help diagnose benign paroxysmal positional vertigo (BPPV), a common cause of brief spinning sensations triggered by head movement. It is usually performed by an ENT specialist or other trained clinician and can guide the next steps in treatment.
Overview
The Dix Hallpike maneuver is a simple, hands-on exam used to help identify benign paroxysmal positional vertigo, better known as BPPV. BPPV is one of the most common reasons people feel a sudden spinning sensation when they lie back, roll over in bed, look up, or bend down.
During the test, a clinician moves the head and upper body into a position that may trigger symptoms if loose inner-ear crystals are present. The response helps the clinician decide whether the dizziness pattern fits BPPV or whether another cause should be investigated.
Because the test is tied closely to the way inner-ear balance works, it is often part of an ENT or neurology assessment. For international patients planning care away from home, it is typically an outpatient evaluation, with answers often available during the same visit.
Symptoms the Test Is Used To Evaluate

The Dix Hallpike maneuver is not used for every kind of dizziness. It is mainly used when a person describes brief episodes of vertigo that are brought on by changes in head position rather than by standing up slowly or by general fatigue.
People with BPPV often describe the sensation as the room spinning, tilting, or moving for a short time. The symptoms may be intense but usually settle within a minute or so, although a feeling of imbalance can linger longer afterward.
- Spinning sensation when lying back or turning in bed
- Dizziness when looking upward or bending over
- Short episodes of nausea related to movement
- Eye movements noticed by the clinician during the test
If dizziness is accompanied by hearing loss, fainting, chest pain, severe headache, weakness, or trouble speaking, the cause may be something other than BPPV and needs prompt medical attention.
Causes & Risk Factors

BPPV usually happens when tiny calcium carbonate crystals inside the inner ear move into a place where they do not belong. Once displaced, they can interfere with the normal balance signals sent from the inner ear to the brain.
In many people, no clear trigger is identified. In others, BPPV may follow a head injury, an inner-ear disorder, prolonged bed rest, or sometimes appear after a viral illness. Age can also play a role, as BPPV becomes more common later in adulthood.
The Dix Hallpike maneuver helps distinguish this specific pattern from other causes of dizziness. That distinction matters because treatment is often mechanical, meaning it focuses on moving the crystals back into a more stable position rather than relying on medication alone.
Diagnosis
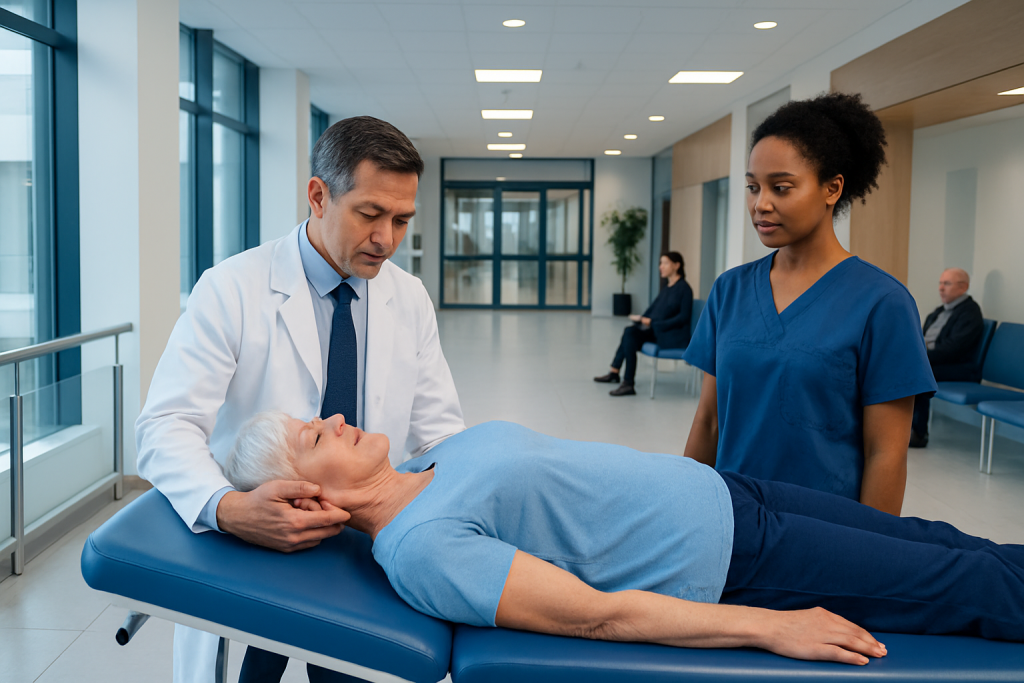
During the Dix Hallpike maneuver, the clinician asks the person to sit on an exam table, turns the head to one side, and quickly lays the person back so the head hangs slightly off the edge. This position is intended to provoke BPPV symptoms if the affected ear is involved.
The clinician watches for nystagmus, which are involuntary eye movements that can help confirm an inner-ear cause of vertigo. The person may also feel brief spinning, nausea, or unsteadiness, and the clinician notes how long the symptoms last and which side triggers them.
Before the test, a specialist may review the medical history and ask about hearing changes, neurologic symptoms, recent injuries, medications, and prior episodes of dizziness. If the pattern is not typical, additional tests such as hearing evaluation, balance testing, or imaging may be considered.
Treatment Options
If the Dix Hallpike maneuver points to BPPV, the next step is often a canalith repositioning procedure, such as the Epley maneuver. These guided head movements are designed to move the loose crystals out of the balance channel where they are causing symptoms.
Many people improve after one or a few treatment sessions, although some notice symptoms return later and need repeat evaluation. In some cases, a clinician may teach a home version of a repositioning exercise or recommend vestibular rehabilitation if balance remains unsettled.
Medication is not usually the main treatment for BPPV, though a clinician may sometimes suggest short-term symptom relief if nausea is significant. The most important part is matching the treatment to the cause, which is why an accurate diagnosis matters.
Prevention & Self-care
There is no guaranteed way to prevent BPPV, but a few practical habits can support recovery and reduce the chance of falls. Movements that trigger vertigo should be done slowly until symptoms are better understood, especially during the first few days after diagnosis.
People who travel for treatment should plan for a companion if possible, since dizziness can make transfers, stairs, and unfamiliar surroundings more difficult. Keeping the head slightly elevated when resting and avoiding sudden position changes may be helpful for some patients, depending on the clinician’s advice.
- Move carefully when getting out of bed or turning over
- Use support when walking if balance feels off
- Stay hydrated and eat lightly if nausea is present
- Follow the clinician’s instructions after repositioning treatment
If symptoms return after recovery, it does not necessarily mean something serious is happening, but it does mean the person should be reassessed so the cause can be confirmed again.
When to See a Doctor
Medical evaluation is important when dizziness is new, recurrent, or clearly linked to head movement. A clinician can determine whether the Dix Hallpike maneuver is appropriate and whether the symptoms fit BPPV or another condition.
Urgent assessment is especially important if dizziness comes with severe headache, fainting, chest pain, trouble walking, weakness, double vision, speech changes, or hearing loss. These features are not typical of simple BPPV and deserve prompt medical review.
For people traveling internationally, it can help to arrange follow-up before leaving the country if symptoms are not fully resolved. Acibadem Health Point’s multidisciplinary specialists and JCI-accredited hospitals diagnose and treat this condition for international patients in a coordinated outpatient setting.
Living With Vertigo After the Test
A positive Dix Hallpike result can be reassuring because it often provides a clear explanation for a distressing but treatable problem. Once BPPV is identified, many people are able to return to normal daily activities with only short-term precautions.
Recovery is often practical rather than dramatic: a repositioning treatment, a period of careful movement, and follow-up if symptoms persist or recur. Patients who received care away from home may also be given a written plan for what to do if vertigo returns after they travel back.
The most helpful next step is usually a follow-up conversation with the treating clinician, especially if the pattern changes. Dizziness has many possible causes, and a well-timed recheck helps keep the diagnosis accurate and the treatment focused.
Frequently asked questions
01What does a positive Dix Hallpike maneuver mean?
A positive result usually suggests BPPV, a problem caused by tiny inner-ear crystals moving into the wrong place. It does not diagnose every type of vertigo, so the clinician still considers the full symptom pattern and medical history.
02Is the Dix Hallpike maneuver painful?
It is not usually painful, but it can briefly cause strong dizziness or nausea. The test is done under supervision so the person can be supported and monitored throughout.
03How long does the dizziness last during the test?
If the symptoms are due to BPPV, the spinning sensation is often brief and may fade within less than a minute. Some people feel a lingering sense of imbalance afterward, especially right after the exam.
04Can this test be done if someone has neck problems?
Not always. The clinician will ask about neck, back, and vascular problems first, because the head and body must be moved into specific positions during the test.
05What happens after the Dix Hallpike maneuver if BPPV is confirmed?
The clinician will usually recommend a repositioning treatment such as the Epley maneuver. Follow-up is considered if symptoms do not improve, return often, or do not match the expected pattern.
06Do all dizzy patients need the Dix Hallpike maneuver?
No. It is mainly used when the history suggests positional vertigo, especially brief spinning triggered by head movement. Other causes of dizziness need different exams and sometimes different testing.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Persistent digestive symptoms? Get evaluated in Turkey
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.


