Calcaneal Apophysitis: Symptoms, Causes, and Treatment Options
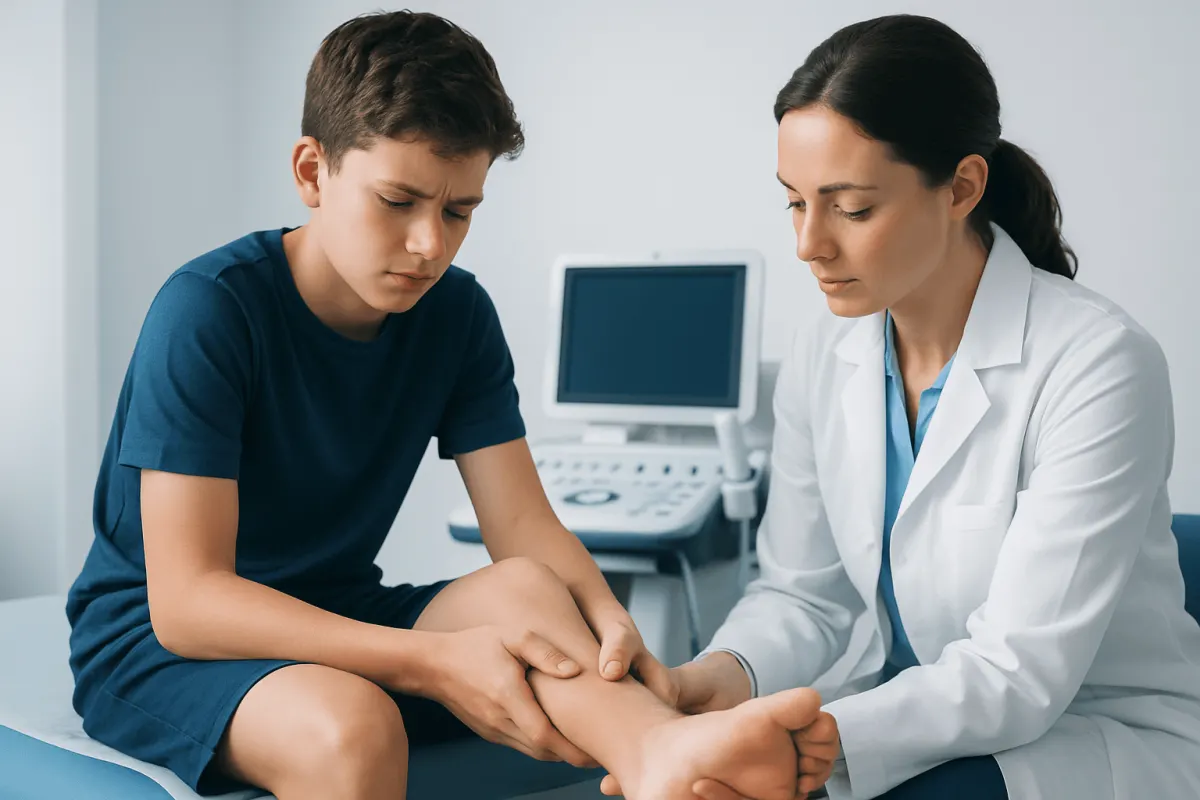
Your child limps off the pitch, rubs the back of their heel, and says it hurts — again. By the next morning it seems fine, until the next training session. This pattern is one of the most common reasons for heel pain in growing children and adolescents, especially those who run and jump a lot.
What is happening is irritation of the growth plate at the back of the heel. The reassuring part: it usually improves with activity adjustment, supportive care, and time.
Overview
Calcaneal apophysitis is one of the most common reasons for heel pain in school-age children and teenagers. It affects the growth plate in the calcaneus, or heel bone, where repeated pulling from the Achilles tendon and repeated impact from activity can cause irritation. Many people also know this condition as Sever's disease.
Despite the name, it is not an infection and it is not a long-term degenerative disease. It is better understood as an overuse condition linked to growth, activity, and mechanical stress on the developing heel. It most often appears during growth spurts, when bones, muscles, and tendons may not lengthen at the same pace.
Children who play sports that involve running, sprinting, jumping, or frequent direction changes are especially likely to develop symptoms. Soccer, basketball, gymnastics, tennis, and track are common examples. Pain may come on gradually or increase after a busy training period.
Most children get better without anything invasive. Spotting it early, easing off activity for a while, switching to supportive shoes, and stretching usually settle the symptoms enough for a child to get back to normal routines in comfort.
How Calcaneal Apophysitis Feels
The main symptom is pain at the back or bottom of the heel, usually in one or both feet. Children often describe it as soreness, tenderness, or aching that gets worse during or after sports. In many cases, the pain improves with rest and returns when activity starts again.
Some children limp, walk on their toes, or avoid putting full pressure on the heel. The heel may feel tender when squeezed at the sides, and stiffness can be more noticeable after exercise or first thing in the morning. Tight calf muscles are also common.
How much it bothers a child varies a lot. One will only mention some soreness after practice; another stops running altogether because the heel hurts too much. Left alone, the pain can start getting in the way of sports, PE lessons, and even ordinary walking.
- Heel pain during running or jumping
- Tenderness at the back or sides of the heel
- Limping or toe-walking to avoid heel pressure
- Stiffness in the calf or Achilles area
- Pain that improves with rest but returns with activity
Why It Happens and Who Is at Risk

Calcaneal apophysitis develops because the heel growth plate is still open in children and adolescents. During growth, this area is more vulnerable to stress than fully mature bone. Repetitive impact from sports and repeated traction from the Achilles tendon can irritate the growth plate, leading to pain.
A rapid growth spurt can increase the risk because bones may lengthen faster than muscles and tendons adapt. This can leave the calf muscles and Achilles tendon relatively tight, increasing the pull on the heel. High training loads, hard playing surfaces, poorly cushioned footwear, and limited recovery time may add to the problem.
Foot mechanics can also contribute. Some children have flat feet, high arches, or movement patterns that place extra force through the heel. These factors do not necessarily cause the condition by themselves, but they may make symptoms more likely during active periods.
Not every child with heel pain has calcaneal apophysitis. Other causes, such as tendon irritation, bursitis, stress injury, or another foot problem, may need to be considered. If pain is unusual or persistent, a specialist may also look for conditions such as Achilles tendon irritation or other sources of pediatric heel pain.
How Doctors Diagnose It
Diagnosis is usually based on the child’s age, symptoms, sports history, and a physical examination. A doctor will ask when the pain started, what activities make it worse, whether the pain is in one or both heels, and whether there has been a recent increase in training or growth.
During the examination, the doctor may gently press on the heel, assess walking and running patterns, and check calf flexibility and ankle movement. Tenderness around the calcaneal growth plate and tight calf muscles can support the diagnosis. In many straightforward cases, no special test is needed.
Imaging is not always necessary, but it may be recommended if symptoms are severe, one-sided, associated with swelling, follow an injury, or do not improve as expected. X-rays can help rule out fracture or other structural problems. In selected cases, advanced imaging such as MRI may be used to investigate ongoing or atypical heel pain.
We are not only confirming calcaneal apophysitis — we are also ruling out the less common causes of heel pain that would need different treatment. A careful assessment guides a safe return to sport and lowers the chance of the discomfort dragging on.
Treatment Options
Treatment usually focuses on reducing stress on the heel while the irritated growth plate settles. Most children improve with conservative care rather than surgery or invasive procedures. The exact plan depends on how severe the symptoms are and how much they interfere with walking, school, or sports.
Activity modification is often the first step. This does not always mean complete rest, but it usually means reducing running, jumping, and high-impact drills for a period of time. Children may be encouraged to continue lower-impact activities if these do not trigger pain. Ice after activity can help with discomfort, and short-term pain relief may be discussed with a doctor when appropriate.
Supportive footwear is important. Shoes with good cushioning and heel support can reduce repeated impact. Some children benefit from heel cups, heel lifts, or orthotic support to reduce strain on the Achilles tendon and improve foot mechanics. Stretching programs for the calf muscles and Achilles tendon are commonly recommended, and some children benefit from guided physical therapy and rehabilitation to improve flexibility, strength, and movement patterns.
If pain is more intense, a doctor may advise temporary sports restriction or brief immobilization in selected cases. Specialist review through orthopedics can be helpful when symptoms persist, keep returning, or affect normal walking. Surgery is not a standard treatment for calcaneal apophysitis.
Recovery, Prevention, and Self-care
Recovery time varies. Some children improve within a few weeks, while others have symptoms that come and go over several months, especially if they continue high-impact sports during a growth spurt. The condition may recur until the growth plate matures, but it usually resolves fully with time.
Returning to sport is best guided by symptoms rather than a fixed timeline. A child is generally more ready to increase activity when walking is comfortable, tenderness is reduced, calf flexibility has improved, and sport-specific movement does not trigger heel pain. Increasing activity gradually can help reduce flare-ups.
Prevention focuses on lowering repeated heel stress. Useful measures include wearing supportive sports shoes, replacing worn-out footwear, warming up properly, stretching the calves regularly, and balancing training with adequate recovery. Coaches and families can also watch for sudden increases in intensity, frequency, or duration of exercise.
- Use well-cushioned, well-fitting athletic shoes
- Stretch calf muscles and the Achilles tendon regularly
- Reduce training volume during painful flare-ups
- Avoid abrupt increases in running or jumping load
- Consider heel cups or inserts if recommended by a clinician
When to Seek Medical Care
Medical evaluation is recommended when heel pain lasts more than a short period, keeps returning, or starts to limit walking, school activities, or sports. A doctor should also assess pain that follows an injury, becomes severe quickly, or does not improve with rest and simple home care.
Urgent assessment is especially important if heel pain is accompanied by fever, significant swelling, redness, night pain, numbness, or an inability to bear weight. These features are not typical of calcaneal apophysitis and may point to a different problem that needs prompt attention.
Parents often ask whether ongoing heel pain means lasting damage. In most cases it improves without long-term problems, but seeing a doctor helps confirm the diagnosis and shape treatment around your child’s activity level and growth stage. If symptoms are persistent or unusually complex, pediatric orthopedics may be involved in care.
If you are travelling from abroad for your child’s heel pain, our specialist teams at Acıbadem Health Point work together across JCI-accredited hospitals to diagnose and treat musculoskeletal conditions in children and adolescents, with a care plan built around your child.
Frequently asked questions
01Is calcaneal apophysitis the same as Sever's disease?
Yes. Sever's disease is another name for calcaneal apophysitis, a common overuse condition affecting the heel growth plate in children and adolescents. It is not an infection and usually improves with conservative care.
02At what age does calcaneal apophysitis usually happen?
It most often occurs in active children during the years when the heel growth plate is still open. This is commonly during late childhood and early adolescence, especially around growth spurts.
03Can a child keep playing sports with calcaneal apophysitis?
That depends on symptom severity. Many children need to reduce or temporarily stop painful high-impact activities, then return gradually as pain settles. Continuing intense activity despite pain can prolong recovery.
04Do children with calcaneal apophysitis need X-rays?
Not always. Doctors often diagnose the condition through history and examination alone. Imaging may be used if symptoms are unusual, severe, one-sided, related to trauma, or not improving as expected.
05How long does calcaneal apophysitis last?
Symptoms may improve within weeks, but some children have flare-ups over several months, especially during busy sports seasons or growth spurts. The condition usually resolves as the growth plate matures.
06What helps relieve calcaneal apophysitis at home?
Common measures include resting from painful activities, icing the heel after exercise, wearing supportive shoes, and doing gentle calf stretching if advised by a clinician. Heel cups or inserts may also help reduce strain in some children.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.
Joint and spine care in Turkey — expert assessment & treatment
JCI-accredited · board-certified surgeons · reply within 24h
Add us as a Preferred Source to see more of our trusted health content across Google Search, AI Overviews and Discover.